299 zł
mysle ze to jest dobre, pokazac to wczesnie
299 zł
mysle ze to jest dobre, pokazac to wczesnie
Sprawdź w 2 kliknięciach
brakuje chyba form submit
Naciśnij ▶. Transkrypcja pojawia się na żywo, a potem powstaje notatka.
jw, nie ogramy tego tak rozsadnie z jakoscia jakie daje echo
Policz, ile czasu odzyskasz
to jest dobre
Naciśnij ▶. Transkrypcja pojawia się na żywo, a potem powstaje notatka.
processingu tego sie nie da ograc live, bedzie zbyt dlugo trwalo - moge rozwinac dlaczego potem
Echo słucha wizyty i w kilka sekund przygotowuje notatkę SOAP do zatwierdzenia. Dane zostają w UE.
tu trzeba wrzucic ze to jest urzadzenie. mamy duzo feedbacku - nie widza urzadzenia, mysla ze to kolejna NOA i "juz takie mieli"
30 dni pilota za 0 zł, zwrot urządzenia
klient placi 1799 kaucji, jezeli rezygnuje to odsyla urzadzenie i zwracamy kase
Czy nie wpakuję się w problem z RODO i tajemnicą lekarską?
Teraz jest duży nacisk na bezpieczeństwo danych, dużo osób pyta o rozwiązanie całkiem offline
formularza
Mamy tidio
„Dołącz do listy oczekujących”, „Poznaj ofertę”, mail i 6 pozycji w menu rozpraszają uwagę. Lista oczekujących odkłada kontakt zamiast go zaczynać.
To chcę kompletnie wyrzucić.
Rozważaliśmy natomiast szybki zakup na stronie: stripe -> płatność i koniec
Nowy produkt AI w medycynie bez żadnego dowodu to ryzyko, którego lekarz nie weźmie na siebie.
Mamy już kilku klientów, którzy pod nazwą, imieniem, nazwiskiem wypowiedzą się pozytywnie zarówno o Echo, jak i Halo
eLife Assessment
Franziscus et al. present an important study introducing SPEx, an elegant, broadly accessible approach to subcellular spatial proteomics that combines cell expansion, laser microdissection, and mass spectrometry to enable protein profiling within defined subcellular regions. The authors provide convincing evidence that this flexible integration of established techniques offers a robust, practical, and cost-effective strategy for compartment-resolved proteomic analysis. The method is appropriately validated across multiple subcellular compartments and complementary workflows, demonstrating its ability to recover known protein markers while identifying previously uncharacterised components. The study also provides a characterisation of the method's capabilities and limitations. Overall, SPEx is likely to be of broad interest to cell biologists seeking to map organelle composition.
Reviewer #1 (Public review):
Summary:
The authors present a novel approach to subcellular spatial proteomics by combining laser microdissection with expansion microscopy and LC-MS/MS analysis (SPEx). They implement two different workflows for LMD and LC-MS/MS quantification:
(1)The standard approach in which an area of interest is cut out by LMD, subjected to proteomics analysis and compared to the rest of the cell without the dissected ROI.
(2) The subtraction approach in which ROIs are removed and the remaining cellular material is compared to samples containing both the surrounding material and the ROI.
The authors assess the technique by applying it to subcellular targets of various size, volume and protein compositions such as the nucleus, nucleoli and Golgi. They demonstrate that SPEx can identify proteins enriched or reduced in ROIs.
Strengths:
The general, relatively easy and inexpensive nature of this approach, as well as its potential applicability to many cell types and subcellular areas of interest provides an exciting alternative to subcellular fractionation, native immunoprecipitation or genetically encoded proximity labeling constructs. Moreover, by visually selecting ROIs for subsequent analysis, subcellular context or organelle morphology can be taken into account as discussed by the authors in the discussion section.
Weaknesses:
The authors addressed our concerns and technical questions in revision.
A main limitation of the current method is that it relies on isolation of structures of interest in 2D. The authors discuss some alternative approaches that might allow future access to more 3D target isolation.
There remain several unexplored minor extensions of the technical development of the method, including comparing the proteomes of organelles that are visually distinct, and applying different anchoring procedures to try to increase protein retention.
Reviewer #2 (Public review):
Summary:
This study introduces SPEx, an approach that combines physical expansion, imaging-guided microdissection, and mass spectrometry for compartment-resolved proteomic analysis. Using the nucleus, nucleolus, and Golgi apparatus as examples, the authors demonstrate that SPEx can identify proteins enriched or depleted in defined subcellular regions.
Strengths:
A major strength of the method is its accessibility and flexibility. It combines established technologies without requiring genetic manipulation or specialized proximity-labeling strategies, while direct imaging-based selection allows regions of interest to be defined according to their spatial and morphological context. The complementary comparative strategies used in the study provide convincing support for compartment-specific protein enrichment and depletion.
An important limitation is the lack of depth resolution during microdissection, which can introduce contributions from material above or below the selected region, particularly for small structures. Appropriate comparative controls are therefore important for interpreting SPEx measurements. The current study is also primarily a proof of principle in a single cultured cell type, and its ability to capture changes across biological states or perturbations remains to be established.
Overall, the study provides convincing evidence that SPEx is a useful and flexible addition to the spatial proteomics toolbox, with particular potential for applications requiring direct image-based selection of subcellular regions.
Reviewer #3 (Public review):
Franziscus et al. describe an elegant approach for spatially specific proteome analysis. To achieve this, they expand fixed cells and subsequently use a laser to micro-dissect a region of interest, which is then analyzed by MS.
They demonstrate the effectiveness of their approach by analyzing nucleus, nucleolus and the Golgi and benchmark their hits against previous dataset for these organelles.
The manuscript is very well written and nicely guides the reader through the applied methods. The presented data is convincing and I do not see the need for additional experimental verification of the protocol. The only minor concern is the novelty of the method and the presentation. A combination of expansion, laser microdissection and proteomics has been applied in the past (PMID: 36450705, PMID: 39477916). In the manuscript one of these studies is cited, though it does not become clear that this approach is already described. However, Franziscus et al. describe the approach better and makes it more accessible to the reader, especially since the other studies described this methodology in combination with tissue expansion and not in combination with single cell expansion as it is done here. I would ask the authors to be clearer in the introduction with what others have already done and what is there contribution here. In general, I am convinced that the community will benefit from the presented protocol to analyze organelle proteomics in detail.
Comments on revised version.
I had only minor issues with the manuscript, which have now been addressed.
Author response:
The following is the authors’ response to the original reviews.
Reviewer #1 (Public review):
Summary:
The authors present a novel approach to subcellular spatial proteomics by combining laser microdissection with expansion microscopy and LC-MS/MS analysis (SPEx). They implement two different workflows for LMD and LC-MS/MS quantification:
(1)The standard approach, where an area of interest is cut out by LMD, subjected to proteomics analysis, and compared to the rest of the cell without the dissected ROI.
(2) The subtraction approach, where ROIs are removed, and the remaining cellular material is compared to samples containing both the surrounding material and the ROI.
The authors assess the technique by applying it to subcellular targets of various sizes, volumes, and protein compositions such as the nucleus, nucleoli, and Golgi. They demonstrate that SPEx can identify proteins enriched or reduced in ROIs.
Strengths:
The broad, relatively easy, and inexpensive applicability of this approach to potentially many cell types and subcellular areas of interest provides an exciting alternative to subcellular fractionation, native immunoprecipitation, or genetically encoded proximity labeling constructs. Moreover, by visually selecting ROIs for subsequent analysis, subcellular context or organelle morphology can be taken into account, as discussed by the authors in the discussion section.
Weaknesses:
While strongly supporting the sharing of this approach, we have a number of comments and questions that will improve the impact of the manuscript:
We thank the reviewer for the careful evaluation of our manuscript and the generally positive assessment.
(1) General:
(a) The manuscript would benefit from restructuring and language revision. In its current form, the writing is sometimes dense and verbose (in particular, the Results section). This makes it difficult to follow the authors' arguments.
We improved readability and clarity in the revised manuscript. We added subheadings to facilitate reading.
(b) The authors mention the possibility of selecting organelles based on morphology. This is left for the discussion, but it seems like a missed opportunity - the authors could compare individual organelles in different morphological states, e.g., connected vs. fragmented mitochondria.
The authors agree with the reviewers’ assessment that investigating proteome of organelles based on morphology or cellular state is an exciting application of SPEx. While we plan experiments along this line in the future, we think that these experiments are beyond the scope of this manuscript, which is meant to describe the method and its general usefulness.
(2) Technical:
(a) Why do the authors strive and optimize for a 10x expansion factor? Is SPEx compatible with a more standard 4x expansion, as e.g., used in the classic U-ExM approach (https://www.nature.com/articles/s41592-018-0238-1)? This could be added to the discussion.
We aimed for 10x expansion solely because our ultimate goal is to cut out very small structures. 10x expansion results in a 100x increase in area, while in U-ExM the area increase would only by 16x. Thus, this makes a huge difference for small structures such as nucleoli. We did not assess the compatibility with U-ExM. Still, we performed pilots with just 4x expansion (using TREx) in the early stages of optimization. We were able to isolate single cells and obtain similar protein coverage as with 10x expansion. We further clarified our motivation to use 10x expansion in the discussion.
(b) The U-ExM approach shows improved ultrastructural preservation when using 3%FA with 0.1% glutaraldehyde fixation (GA). Is SPEx compatible with the use of low amounts of GA for fixation?
We tried different fixation methods in the early stages of this study (where expansion was not yet close to 10x). We saw a mild negative effect of GA on the expansion factor, so we avoided it in the later experiments since it also did not seem necessary to preserve the structure of our organelles of interest. However, the use of GA would generally be compatible with SPEx, potentially at the cost of a mild negative effect on expansion factor (see Author response image 1) and proteome coverage. We discussed the use of GA in the discussion section.
Author response image 1.
Fixation methods mini-screen. Cells were fixed with the indicated reagents for 10 minutes at 37°C. After TREx expansion, the diameter of the nucleus was measured (A) and the resulting expansion factor compared to the non-expanded control was determined (B).
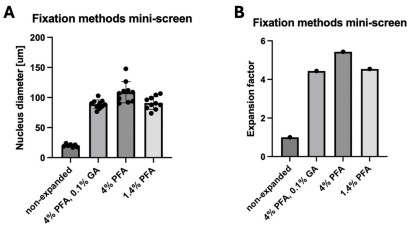
Related to the above, was the anchoring efficiency reduced only to achieve a 10x expansion factor or does this additionally affect the proteome coverage?
We solely lowered the anchoring to increase expansion factors. In earlier pilots we performed proteomic analysis on samples that were just expanded 4x using standard TREx expansion (also using the original anchoring strategy from the TREx publication, consisting of 0.2 mg/ml AcX for overnight at RT). We presented the results of this pilot in Fig S1A. We still detected over 2,000 proteins from 10 cells, a coverage, which is highly similar to what we found in the final experiments (Figure 2F), in which the anchoring was lower for 10x expansion. Based on these data, we think that anchoring (and expansion factor!) has a negligible impact on protein coverage. We clarified this point in the manuscript.
(d) Have the authors considered using alternative anchoring approaches, such as GMA (https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0291506#pone.0291506.s001), which potentially increase the amount of sample retained in the hydrogel, thus allowing for better proteome coverage? This could be added to the discussion.
We did not use alternative anchoring approaches. We modified the TREx protocol to fit our purposes and since this was sufficient, we did not explore alternatives. However, using anchoring approaches, in which higher amounts of sample could be retained in the gel might be beneficial for the proteomics coverage. We will keep this suggestion in mind for future experiments. Thank you for the suggestion!
(e) The limitation of the approach to near-2D samples should be mentioned, and alternative approaches for more 3D samples could be discussed.
The authors agree that SPEx is limited to near-2D samples at this point. We suggest that SPEx is applicable for 3D samples (e.g. in tissues) by performing cryosectioning. TREx has been shown to be compatible with sectioned tissue (Damstra et al., 2022). We discuss this point in the discussion.
(f) How are peptides that are directly anchored to the hydrogel dealt with during LC-MS/MS analysis? Are they excluded, or can they be identified during the spectral search? The latter would allow us to get a deeper structural understanding of how proteins are actually anchored into hydrogels, which so far has not been assessed.
The reviewer raises an interesting point. In general, peptides carrying the anchoring modification are analysed by LC-MS, but we did not include these specific modifications in the database search. Overall, we assumed that the labeling would be low and stochastic and hence should, if at all, only minimally affect the detection of peptides. Nevertheless, in response to the reviewers’ comment, we searched the MS data again for the crosslinking reagent linked to lysine residues. However, we could not get any confident hit for any peptide containing this modification. Since we cannot exclude that the modification precludes the identification of the corresponding peptides, we compared the number peptides generated by trypsin cleavage after arginine and lysine. As the human genome contains similar proportions of both amino acids, one would expect similar numbers for both peptide types being identified. Any modifications of lysine by the anchoring reagent, would prevent tryptic cleavage and thus reduce the number of lysine peptides. As shown in Figure S1C, the number of lysine-terminating is only slightly lower compared to arginine-terminating peptides. Notably, the proteomics results of a different fixed human tissue sample directly extracted by laser capture micro dissection without expansion showed a very similar lysine-to-arginine peptide ratio. This indicates that the large majority of lysine residues is not modified and affected by the hydrogel anchoring. We included these data into the manuscript.
An alternative approach to address this question would be to investigate if the peptide coverage of proteins detected by SPEx is enriched for peptides representing the folded core of proteins as opposed to the surface-exposed regions, which likely get more anchored into the hydrogel.
Because of the negligible amounts of modified peptides, we did not investigate this potential bias of surface-exposed versus folded-core peptides.
(g) Same question regarding peptides with NHS labeling. Can they be identified, or do they just compete for ionization and thus negatively affect coverage and dynamic range of the LC-MS/MS approach?
The reviewer raises a similar point as above for another lysine labeling used during the SPEx protocol. Again, we specifically looked for this modification by re-searching the raw MS data, but still could not identify any peptides, carrying this modification on a lysine residue. Even though we cannot exclude that this rather large modification prevents detection, considering the high number of lysine-terminating peptides in our dataset (see Figure S1 C), we would expect that also this labeling step is stochastic and affects only a minor proportion of the proteins. We discuss the potential NHS labeling in the manuscript.
(h) How are the primary and secondary antibodies affecting the proteomics analysis identified as contaminants?
We thank the reviewer for this comment. Since antibodies bind to proteins in a non-covalent manner, they will be released during the denaturing steps of the protocol. Of course, the antibodies will stay in the sample, be digested and analyzed and could, if very abundant, affect the analysis of the proteins from the samples. To check this possibility, we re-searched the MS data including the sequences of the antibodies used. To our surprise, we could not detect any peptides of these antibodies. This suggests that the concentrations of the antibodies used are much lower than those of the sample proteins and thus should not have any impact on the proteomics results. We interpret this result also as a benefit of our method compared to organellar-IP.
(i) Have the authors observed differences in proteomics coverage of only antibody vs NHS-labeling? Depending on the questions above, could pure antibody-based labeling increase proteomic coverage?
We did not perform this comparative analysis, since we always used NHS dyes. In the experiments presented in this manuscript, NHS dyes allowed easy visualization of the whole cell without the use of antibodies. This NHS staining was essential for this particular setup for sample acquisition. We cut out entire cells, cells lacking the nucleus and cells lacking the Golgi apparatus, which served as critical controls. However, other ways of detecting cell boundaries could be used to avoid NHS staining. As shown above, both, the anchor and NHS labeling are likewise sparse and stochastic. Moreover, we could not detect any impact of the antibody labeling to our results. Thus, we assume that both labeling procedures could be used.
Reviewer #1 (Recommendations for the authors):
(1) Introduce the aberration PPS-membrane.
We apologize for the omission and now explain the PPS abbreviation.
(2) Please state which cells are used already in the first section "Development of the SPEx method" as opposed to only further down in the manuscript.
We apologize for the omission, which has been fixed.
(3) In Figures 2D and E, the authors should also show the hydrated expansion factors for better comparison.
We agree that the inclusion of the hydrated expanded gels allows for better comparison. These data are now included in the manuscript.
Reviewer #2 (Public review):
Summary:
This study introduces a method that combines physical expansion of cells, imaging-guided isolation of defined regions, and protein identification to enable compartment-resolved analysis of protein composition at the subcellular scale. The authors aim to address a central limitation in existing approaches, namely the loss of spatial information during sample preparation or the indirect nature of proximity-based labeling methods. Using several cellular compartments as examples, they demonstrate that their approach can recover compartment-enriched protein sets and identify candidate proteins with previously unassigned localization.
Strengths:
A major strength of this work is the conceptual simplicity and accessibility of the approach. By combining established techniques in a modular way, the method avoids the need for genetic manipulation or specialized labeling strategies, making it broadly adaptable across experimental systems. The ability to directly select regions of interest based on imaging represents a clear advantage over indirect enrichment strategies and allows flexible targeting of both membrane-bound and non-membrane-bound compartments.
The experimental design is also a strong aspect of the study. The use of complementary comparison strategies-analyzing isolated compartments alongside matched "subtracted" controls-provides an internal framework for assessing enrichment and depletion, increasing confidence in spatial assignment. The application of the method across multiple organelles of different sizes and properties demonstrates versatility, and the reported specificity for several compartments is encouraging. In particular, the ability to profile small and biochemically challenging structures highlights a potentially important niche for the approach.
Weaknesses:
Despite these strengths, several methodological limitations constrain the interpretation of the results. The most important relates to spatial accuracy in three dimensions. While lateral resolution is improved through physical expansion, the lack of depth resolution introduces uncertainty regarding contributions from structures above and below the selected region. Although the authors argue that this does not substantially affect specificity, the current evidence is largely indirect, and a more rigorous quantification of potential contamination would strengthen this conclusion.
Quantitative interpretation also remains challenging. Because the measurements reflect total protein abundance rather than local concentration, differences in compartment size and protein density can influence enrichment values, particularly for small structures embedded within larger volumes. This issue is evident in the analysis of smaller compartments and complicates direct comparison across conditions. Additional normalization or modeling would help clarify how to interpret these measurements.
Another limitation concerns variability in the expansion process and its downstream consequences. Differences in expansion factor across samples may affect the definition of regions of interest and introduce variability in sampling, yet the impact of this variability is not fully explored. Similarly, the use of a modified chemical treatment to preserve proteins for downstream analysis is central to the workflow but is not extensively validated with respect to preservation of spatial organization.
While the identification of previously unannotated proteins is an appealing aspect of the study, validation is limited to a small number of examples, and broader support from independent datasets or literature context is lacking. In addition, the study primarily focuses on steady-state measurements in a single cell type, and therefore does not yet demonstrate the ability of the method to capture dynamic or condition-dependent changes in protein localization.
Finally, the positioning of the method relative to existing approaches could be more clearly articulated. Although qualitative comparisons are provided, a more systematic and quantitative benchmarking against alternative strategies would help readers better understand the specific advantages and trade-offs.
We thank the reviewer for the careful evaluation of the manuscript and for the constructive feedback. The reviewer raises valid points, which we addressed in the revised manuscript.
Reviewer #2 (Recommendations for the authors):
Additional experiments and analyses
(1) To strengthen confidence in the spatial specificity of the method, the authors should include experiments or analyses that directly estimate potential cross-compartment contamination. For example, using markers that are known to localize to mutually exclusive cellular regions would allow an empirical assessment of signal carryover. Alternatively, a computational or geometric model could be used to estimate how much material from adjacent regions is expected to contribute to the sampled proteome, given the loss of depth information.
We agree with the reviewer’s concern regarding spatial resolution and potential contaminations resulting from it. We had the same concerns. We have obviously no resolution in z and we detected about 700 proteins (Fig. 5F) in our all samples, likely representing proteins residing above and below of (and potentially next to) the structures we cut out. To overcome this issue, we always compare the proteome of the structure of interest with an appropriate control. We also determined that mitochondria proteins are specifically omitted from our nuclear samples. Moreover, we provide evidence that our analysis methods can be used also to determine proteins that are specifically lost from a structure. Omitting the comparative approach would clearly result in very low specificity and a high number of false positives. However, we argue that comparison to a control largely removes these unspecific contaminations and we think that this is illustrated by our excellent specificity. Nevertheless, to address these concerns further, we have determined the masses of all quantified proteins using iBAQ values. We then summed the masses of all proteins being annotated to a specific organelle and calculated the percentage to the summed masses of all quantified proteins. As expected, we found that in our excised nuclei samples, 75.5% of the protein molecules originate from the nucleus and only 24.5% of protein mass was derived from other regions. Likewise, we found 84.7% of the protein mass in the excised Golgi samples annotated with Golgi or extracellular by GO. This analysis revealed that we detect an expected amount of contaminant proteins derived from other compartments due to the lack of resolution in z, but most of protein mass excised is already organelle-specific. The additional quantification step further enhances assignment accuracy, boosting the overall specificity of our approach. In the case of the nucleoli the mass contribution from known nucleoli proteins is significantly lower (~4%), which would be expected for a structure that only covers a fraction of the cell in z-direction. In the case of such small targets comparison to a fitting control is therefore essential. We added this analysis to the revised version of the manuscript and discuss it in detail (see “SPEx is best used as a comparative approach”). We thank the reviewer for bringing this up!
(2) Given that drying results in compression along the vertical axis while largely preserving the lateral dimensions, it would be valuable to provide a quantitative analysis of how this affects spatial accuracy. This could include comparing marker distributions before and after drying or examining signal distribution across depth.
Even though we were unable to image a particular cell before and after drying (due to the physical properties of the gels and the change in size during drying), we did so for the bulk of cells. We did not observe discernible morphological alterations after drying. The investigated structures (Golgi, nucleus and nucleoli) still looked morphologically similar to expanded cells (before drying) and non-expanded cells. We cannot exclude that the drying process introduced minor distortions of the sample. We would like to point out, however, that our focus is mainly on the spatial proteomics and to a lesser extent on the perfect conservation of the ultrastructure during drying. As long as we can maintain very good spatial separation and are able to cut out individual structures, our method should work just fine.
In addition, trimming or sectioning the expanded samples along the z-axis prior to microdissection could help minimize contributions from structures above and below the region of interest, thereby improving spatial specificity.
We tried to cut expanded samples (monolayer of cells) with a microtome prior to laser dissection. This approach did unfortunately not work. Mounting a monolayer of cells for microtome cutting is non-trivial! The very thin monolayer of cells would need to be perfectly aligned with the plane where the cryo-sectioning takes place. Moreover, the different densities of the hydrogel without cells and the expanded cells in the same hydrogel appeared to be particular challenging during sectioning. Therefore, we gave up on this approach for monolayers. For a monolayer of cells, the contamination in the lateral dimension seems to be small enough so it can be eliminated by comparing the sample to appropriate controls, preventing the need for cryo-sectioning. We do think, however, that cryo-sectioning should be feasible for tissues since the combination of cryo-sectioning and TREx expansion in tissues has been described previously (Damstra et al., 2022).
(3) Because the method relies on imaging-guided spatial dissection of a three-dimensional structure, further validation of spatial precision would strengthen the manuscript. Applying z-stack trimming to reduce depth-related ambiguity and comparing results obtained with more conservative and spatially restricted cutting boundaries would help determine how sensitive the proteomic output is to segmentation strategy and provide a clearer assessment of robustness.
As pointed out above, we were unable to perform trimming in z. Therefore, the proposed analysis cannot be performed.
(4) The use of SDS-based denaturation instead of protease digestion represents a key methodological deviation from conventional expansion workflows and is central to enabling downstream proteomic analysis. The authors should provide additional validation demonstrating that this approach preserves spatial fidelity without introducing distortion or bias in protein localization.
We respectfully disagree with the reviewer. SDS denaturation was used previously in both the TREx and the U-ExM protocols (Damstra et al., 2022; Gambarotto et al., 2021). The preservation of ultrastructure has been established in both studies. Still, as pointed out by the reviewer, protease digestion is frequently used in ExM, likely because it minimizes distortion of the sample by eliminating any mechanical resistance to expansion. We omitted protease treatment to be able to perform LC-MS/MS. Protease treatment would likely reduce the amounts of peptides we would be able to detect. However, with the extended SDS denaturation, we were able to maintain excellent expansion even in the absence of protease treatment.
(5) The manuscript reports variability in expansion factors across conditions, and it would be important to more clearly establish reproducibility. The authors should quantify variability across biological replicates and discuss how differences in expansion factor influence region-of-interest selection, spatial resolution, and downstream quantitative analysis.
We were surprised that this reviewer thinks that we have variability in the expansion factors across conditions. In fact, the expansion is rather reproducible, and we only observe very minor variability in expansion factors between samples. The minor differences in expansion factor are unlikely to affect sampling because sampling happens manually and differences in the size of an organelle are accounted for by just adjusting the size of the isolated ROI. Even if we would have some discernible difference in the expansion factor between samples, this would not matter. The organelle of interest is cut out from the same cell, which will be subsequently used as control. Each sample subjected to LC-MS/MS contained at least 10 individually cut-out objects, further eliminating variability potentially introduced by minor changes in expansion levels.
(6) The authors should also address how differences in compartment size and protein density influence quantitative interpretation. Because proteomic measurements reflect total protein abundance rather than local concentration, smaller compartments may be underrepresented. Incorporating normalization strategies or simulations would help clarify how enrichment values should be interpreted across compartments.
We agree with the reviewer that comparison of structures of very different sizes might be technically difficult and that in such cases, controls should be collected in a similar size range to the actually studied compartments. We have implemented this change already in our workflow and mention this consideration in the discussion.
Regarding normalization, we employed median normalization to our proteomics data abundances which controls for different sample amounts and eventually results in a comparison of protein concentration rather than pure protein abundances. This approach eliminates any knowledge of cell or organelle size and allows a more uniform comparison. We do agree, however, with the reviewer that for differential proteomics analysis, regions of interest should be preferable of the similar size and protein amount to avoid normalization biases. We discussed this point in the revised manuscript.
(7) Validation of newly identified compartment-associated proteins should be expanded. In particular, the interpretation of proteins such as C7orf50 and SPOUT1 would benefit from deeper contextual discussion, including whether prior studies have reported alternative localizations under different cellular conditions and whether their localization may be cell-type-specific or context-dependent.
We agree that more contextual discussion of the newly localized proteins will benefit the manuscript. We added more information about the newly identified proteins to the results section.
(8) To support broader claims about the utility of the method, the authors should consider demonstrating that the approach can capture biologically meaningful, context-dependent changes in protein localization. For example, comparing different cell types or applying defined perturbations such as stress or apoptosis would help establish the ability of the method to resolve dynamic intracellular remodeling.
The authors agree with the reviewers’ assessment that studying context-dependent changes at a subcellular level is an exciting idea to explore. While we are currently planning such experiments, we think that these experiments are beyond the scope of this manuscript, which is meant to describe the method and its general usefulness.
(9) The manuscript would benefit from a more direct and quantitative comparison with existing spatial proteomics approaches. In particular, benchmarking against proximity labeling methods would help clarify relative performance in terms of specificity and false positive rates, and comparison with published datasets could provide an objective frame of reference.
We are a bit puzzled by the reviewer’s request. We already compared SPEx to a number of established spatial proteomics methods in the paper (Figure S1I-J, Figure S2F-G, Figure 5F-G) and discuss coverage and specificity. However, we expanded this comparison further to methods using Exm combined with LMD in the new manuscript (see below).
(10) In addition, the positioning of the method relative to other expansion-based spatial proteomics approaches remains insufficiently defined. The authors are encouraged to include a structured comparison, ideally in the form of a summary table, outlining key parameters such as sampling strategy, spatial resolution, proteome depth, spatial specificity, throughput, and limitations. This would help clearly delineate the unique contributions of the approach within the broader methodological landscape.
Peer reviewer’s request, we added a table (S15) on spatial proteomics methods combining expansion microscopy with manual or laser dissection and also provide information about lateral resolution, sampling strategy, proteome coverage, advantages and limitations.
Writing and presentation
(1) The presentation of expansion-related measurements would benefit from clearer organization. Currently, expansion factors from non-dried and dried samples are presented in separate figures, which may create redundancy and confusion. Reorganizing these data to directly compare pre- and post-drying conditions, or moving non-essential measurements to supplementary material, would improve clarity.
We now also show the hydrated expansion factors in Figure 2C-D for comparison.
(2) The method used for quantifying expansion should be described more explicitly. It should be clarified whether the same structures were tracked before and after expansion or whether independent samples were used, particularly for nuclei, which vary in size.
We use the nucleus because this also used by other groups in the field (Liffner et al., 2024). The tracked structures are from independent samples. Thus, we average over a number of structures and calculate the expansion factor based on the mean diameter. We made this clearer in the manuscript.
(3) Additional clarification is needed regarding the fluorescent labeling strategy. The rationale for using different dyes across experiments should be explained to distinguish whether these choices are driven by technical constraints, experimental design, or visualization preferences.
We agree with the reviewer that the manuscript will profit from a more in-depth discussion of the labeling strategy. The structure of interest was always labeled in red because in our hands more red-shifted dyes are more resistant to drying than e.g. green dyes. We added this information to the manuscript.
(4) Several figure legends and result descriptions would benefit from revision for clarity and completeness. In particular, complex panels such as intersection analyses should be more fully explained to ensure accessibility to readers.
We agree with the reviewer’s assessment. The intersection analysis and the PCA, which represent the most complex panels in the manuscript, are now more clearly described in the legends.
(5) The authors should also improve clarity in describing structural changes associated with drying. Including representative images of gels before and after drying would help illustrate the preservation of lateral dimensions and compression along the vertical axis.
We agree that this addition would improve the manuscript. We included the images as Figure S1B. The gel post-drying is outlined by black dots because the gels become very thin and near-invisible post-drying.
Minor corrections
(1) Minor issues should be addressed to improve consistency and readability. These include correcting figure cross-references, standardizing statistical notation throughout the manuscript, and resolving typographical inconsistencies.
Done.
(2) Specific figure-related issues should also be addressed, including clarifying mislabeled figure references and improving color schemes in plots where group distinctions are currently difficult to interpret.
Done.
Data and reproducibility
(1) The authors should ensure that all datasets and analysis workflows are fully accessible and sufficiently documented to enable reproducibility. This includes providing raw and processed proteomics data, as well as detailed descriptions of analysis pipelines and parameter settings.
Raw proteomics data for all experiments will be publicly available upon publication of the final version and workflows are described in a detailed manner. To improve reproducibility, we also included a step-by-step explanation of the assembly of the gelation chamber, which represents the handling-wise most challenging step of the protocol, in Figure S3D.
Reviewer #3 (Public review):
Franziscus et al. describe an elegant approach for spatially specific proteome analysis. To achieve this, they expand fixed cells and subsequently use a laser to micro-dissect a region of interest, which is then analyzed by mass spectrometry.
They demonstrate the effectiveness of their approach by analyzing the nucleus, nucleolus, and the Golgi, and benchmark their hits against previous datasets for these organelles.
The manuscript is very well written and nicely guides the reader through the applied methods. The presented data is convincing, and I do not see the need for additional experimental verification of the protocol. The only minor concern is the novelty of the method and the presentation. A combination of expansion, laser microdissection, and proteomics has been applied in the past (PMID: 36450705, PMID: 39477916). In the manuscript, one of these studies is cited, though it does not become clear that this approach is already described. However, Franziscus et al. describe the approach better and make it more accessible to the reader, especially since the other studies described this methodology in combination with tissue expansion and not in combination with single cell expansion as it is done here. I would ask the authors to be clearer in the introduction about what others have already done and what their contribution is here. In general, I am convinced that the community will benefit from the presented protocol to analyze organelle proteomics in detail.
We thank the reviewer for the careful evaluation of our manuscript and overwhelmingly positive assessment. We apologize for the omission of the mentioned citations, which are now included in the manuscript together with a direct comparison with the mentioned methods (Table S15).
References
Damstra HG, Mohar B, Eddison M, Akhmanova A, Kapitein LC, Tillberg PW. 2022. Visualizing cellular and tissue ultrastructure using Ten-fold Robust Expansion Microscopy (TREx). eLife 11:e73775. DOI: https://doi.org/10.7554/eLife.73775
Gambarotto D, Hamel V, Guichard P. 2021. Ultrastructure expansion microscopy (U-ExM). Methods in Cell Biology 161:57–81. DOI: https://doi.org/10.1016/bs.mcb.2020.05.006, PMID: 33478697
Liffner B, Silva TLA e., Vega-Rodriguez J, Absalon S. 2024. Mosquito Tissue Ultrastructure-Expansion Microscopy (MoTissU-ExM) enables ultrastructural and anatomical analysis of malaria parasites and their mosquito. BMC Methods 1:13. DOI: https://doi.org/10.1186/s44330-024-00013-4
eLife Assessment
This important study identifies and characterizes a set of amino acid states that can rescue protein function in the presence of substantially deleterious mutations. Some of these super-compensatory substitutions also confer substantial mutational robustness, with broader implications for understanding epistasis, protein evolution, and protein engineering. The evidence is compelling, supported by a creative reanalysis of a large deep-mutational-scanning dataset, experimental validation, an in-depth investigation of the evolutionary implications, and structural mechanistic analysis.
Reviewer #1 (Public review):
Summary:
The study identifies and characterizes a set of amino acid states that make the protein robust to other mutations, to the point of being able to compensate mutations that render wildtype proteins entirely non-functional. The study uses a previously published dataset and uses it to find and study such super-compensators. It then analyzes the biophysics and fitness landscape structure of what may be behind the compensation, identifying stability as an important parameter that, nevertheless, is not sufficient to explain all of the compensatory effect. These findings have important implications for our understanding of protein evolution, with these super-compensators possibly acting in a role of "permissive mutations" and open up evolutionary trajectories that may be closed without them. Perhaps the identification of such super-compensator substitutions can be incorporated into various protein design approaches.
Strengths:
The paper presents a compelling case with a rigorous analysis of the expected error rates of observation. While not unique, the current state-of-the-art in the field typically does include experimental error rate estimation like this work. The paper also does a good job in exploring the issue, including looking at plausible biophysical basis of super-compensators.
Comments on revised version.
The authors have addressed all of my concerns in the revision.
Reviewer #2 (Public review):
Summary:
This manuscript presents an interesting and conceptually valuable analysis of compensatory evolution using a large combinatorial deep-mutational-scanning dataset for yeast His3p.
Strengths:
I particularly like the identification of "super compensatory" substitutions that improve fitness across diverse genetic backgrounds and apparently reduce the sensitivity of the local fitness landscape to subsequent mutations. The work connects epistasis, protein stability, mutational robustness, and evolvability in a clear and potentially broadly relevant manner.
The authors provide several complementary lines of evidence in support of this central conclusion. In particular, the new experimental validation of S189A is an important strength because it directly demonstrates that a predicted super compensator can buffer the effects of diverse deleterious substitutions, while analyses of additional DMS datasets from other proteins and assay systems suggest that the phenomenon is not restricted to the original His3p landscape.
Comments on revised version.
The authors have satisfactorily addressed all of my previous concerns.
Reviewer #3 (Public review):
Summary:
The manuscript by Jiang and co-authors presents an analysis of experimental measurements (about 400k variants) from a deep mutational scan of HIS3 enzyme. The authors assess the ability of a genotype to be "rescued" and show that this depends on mutation sites (in particular their solvent accessibility) and mutations effects (should be mild on folding stability or binding affinity). They further identify a set of super-compensatory mutations and their results suggest that these mutations flatten the fitness landscape.
Strengths:
This finding is interesting and likely of interest to a broad community. The analysis seems sound.
Comments on revised version.
The authors have satisfactorily addressed my concern. Additional robustness experiments and case studies from ProteinGym are valuable.
Author response:
The following is the authors’ response to the original reviews.
eLife Assessment:
This important study identifies and characterizes a set of amino acid states that can rescue protein function in the presence of substantially deleterious mutations. Some of these super-compensatory substitutions also confer substantial mutational robustness, with broader implications for understanding epistasis, protein evolution, and protein engineering. The evidence is convincing, supported by a creative reanalysis of a large deep-mutational-scanning dataset, statistically rigorous treatment of anticipated error rates, experimental validation, and analyses of additional proteins, although clearer presentation and deeper investigation of the evolutionary implications and structural mechanisms would further strengthen the study.
We sincerely thank the Reviewing Editor, the Senior Editor, and the three reviewers for this assessment. The two directions identified in it are addressed directly in the present revision. The structural mechanism of super compensation is now examined with an inverse-folding model in addition to the Rosetta calculations (Reviewer #2, Comment 1); the evolutionary implications are tested on a phylogeny rather than by co-occurrence among extant species, with the remaining limitations stated explicitly (Reviewer #2, Comment 3); and the presentation is revised throughout, including the title, the terminology used for fitness landscapes, the two section titles, the numbering of equations, and the figures (Reviewer #1). We hope that these revisions strengthen the clarity and the evolutionary interpretation of the study.
Reviewer #1 (Public review):
Summary:
The study identifies and characterizes a set of amino acid states that make the protein robust to other mutations, to the point of being able to compensate mutations that render wildtype proteins entirely non-functional. The study uses a previously published dataset and uses it to find and study such super-compensators. It then analyzes the biophysics and fitness landscape structure of what may be behind the compensation, identifying stability as an important parameter that, nevertheless, is not sufficient to explain all of the compensatory effect. These findings have important implications for our understanding of protein evolution, with these super-compensators possibly acting in a role of "permissive mutations" and opening up evolutionary trajectories that may be closed without them. Perhaps the identification of such super-compensator substitutions can be incorporated into various protein design approaches.
Strengths:
The paper presents a compelling case with a rigorous analysis of the expected error rates of observation. While not unique, the current state-of-the-art in the field typically does include experimental error rate estimation like this work. The paper also does a good job in exploring the issue, including looking at plausible biophysical basis of super-compensators.
We are deeply grateful to Reviewer #1 for the constructive feedback and the careful reading of our manuscript. We are particularly encouraged by the assessment that the paper “presents a compelling case with a rigorous analysis” of the expected error rates of observation, and by the recognition that the identification of super compensatory substitutions may inform protein design approaches. The comments on the rigor of the evolutionary framing, on the presentation of the fitness-potential analysis, and on the figures were highly valuable in improving the manuscript. We have carefully considered each point and itemize the corresponding revisions below.
Weaknesses:
(1) The paper lacks rigor in talking about evolutionary-related issues of the state of the fitness landscape. As an example, the paper mentions that these super-compensators flatten the landscape. While I understand where this is coming from, I think that the fitness landscape in this context is a static entity and cannot be flattened or otherwise altered. A much more accurate description is that a sequence with a super-compensator is located in a flatter-than-expected segment of the fitness landscape, or on a flat fitness ridge. These issues are more semantic in nature, and while the manuscript would benefit from it being shown to an expert in molecular evolution or fitness landscapes, this issue does not take away from the importance of the results.
We thank the reviewer for the suggestions. The proposed title is “Super-compensatory substitutions restore protein function and confer local mutational robustness”. The replacement text distinguishes the fixed genotype-to-fitness map from comparisons among local neighborhoods within that map. “Local mutational robustness” is defined operationally as a smaller absolute measured effect of the same second-site substitution in matched backgrounds carrying the focal state. The prepared prose removes statements that a substitution “flattens,” “smooths,” or changes the landscape and instead says that a genotype occupies a locally flatter region or fitness ridge.
Reviewer #1 (Recommendations for the authors):
I think that there should be more rigor when talking about or painting a mental picture of the fitness landscape (see above). More minor comments below:
Main text
(1) Line 106: "pooled competitive growth assays" -> is it correct to call it "competitive"? By design, there should not be competition in the sense that the presence or absence of cells with genotype A should not influence the growth rate of cells with genotype B.
We thank the reviewer for the careful terminology check. We fully agree that “competitive” is misleading here, as the assay does not measure direct competition between genotypes. We have revised the term to “pooled growth assays” throughout the manuscript to more accurately reflect the experimental design.
(2) Line 125: 3,750 rescuable genotypes are identified among 31,701 lethal ones (Line 111), but in the abstract the claim is one-third of non-functional missense variants are rescuable (Line 26-27). I am not sure I understand.
We thank the reviewer for catching this inconsistency. Upon re‑checking, we realize that 3,750/31,701 is approximately 11.8% (roughly one‑tenth), not one‑third. The “one‑third” figure in the Abstract was a misstatement and has been corrected to reflect the correct proportion. All other numbers in the main text and abstract have been cross‑checked and are consistent.
(3) Line 149: add citation to His3p being a homo-24-mer.
We thank the reviewer for the suggestion. The citation has been added accordingly (Rawson et al., 2018).
(4) Lines 178-187: I understood the paragraph about the fitness potential of super compensators, but I think that it should be shown to someone who does not think of fitness potentials as much as I do and see if it makes sense to them.
Please refer to the question 2 of reviewer 3
(5) Line 188: The title (and the paragraph) could focus on buffering beneficial ones; for deleterious, it is given by definition (although strictly only for lethals).
We thank the reviewer for the suggestion. We have revised the title to “Super Compensators Buffer the Effects of Beneficial Substitutions” to clearly emphasize that our study focuses on the buffering of beneficial mutations
(6) Line 238-239: Even more strongly than previously, the title is describing a property given by definition of (super) compensators, is it not?
We thank the reviewer for this critical and insightful point. We fully agree that the original title, “Super Compensators Enhance Organisms’ Tolerance to Deleterious Mutations,” risked stating a tautological property inherent to the definition of compensators. To address this, we revised it to “Validating Super Compensators as Robust Buffers of Deleterious Substitutions”, which now emphasizes the experimental validation aspect rather than a definitional property.
(7) Line 260: Regarding the robustness of the findings in other datasets - first, I did not see any results based on these datasets (maybe that is for another publication), and it is not clear which results are being referred to. Is it the existence of super-compensatory mutations, or their prevalence or their global stabilizing effect, or all of that?
We thank the reviewer for this important query. We have now clarified in the revised manuscript that our analysis of the other datasets was intended to test whether supercompensators can be detected in other proteins, not to estimate their global stabilizing effects. The results (Fig. S7A–B) show that such high‑compensation amino acid states do exist in other systems.
(8) Figure 1A: why does it jump in the diagram from WT 2 mutations away rather than 1?
We thank the reviewer for pointing out the inconsistency in Figure 1A. We have revised the figure as suggested, and the updated version now properly shows the stepwise progression from WT through the single‑mutation intermediate to the double‑mutation state, removing the original jump.
(9) Lines 655-656: Figure 1C dark blue vs black is hard to read.
We thank the reviewer for this suggestion. We have changed the dark blue to light blue in Figure 1C to enhance readability ‘
(10) Figure 2D: given axes, it would read better if it is a square.
We thank the reviewer for raising this issue. We have revised Figure 2D to a square (1:1) aspect ratio, as suggested, to improve readability. The updated figure is now included in the revised manuscript.
(11) Lines 681-682: when the definition of compensatory ability is the sum of incoming weights - although mathematically easiest, I am not sure what the sum represents. Because these weights are products, wouldn't a product be more natural? Not sure about this myself.
We thank the reviewer for raising this important issue. The graph direction to represent transitions from the existing background state to added substitutions. Each edge records the fraction of pairs showing a fitness increase ≥ 0.5. A product of incoming weights was not adopted because zero-valued weights would force the product to zero, obscuring differences in compensatory ability across substitutions.
Supplementary
(1) Figure S8 - the figure itself is confusing; I cannot connect it with the conclusion.
We apologize for the confusion caused by Figure S8. To address this, we have revised the figure layout and significantly expanded the legend to explicitly describe: (1) the origin and processing of the data, (2) the definition of the row/column of the heatmap, and (3) a direct interpretation to the corresponding conclusion. We believe the updated version now clearly conveys the intended message. The revised figure and legend are included in the updated supplementary materials.
(2) The font is inconsistent with the rest of the document.
We thank the reviewer for this careful observation. We have revised the font in the indicated section to match the formatting used throughout the manuscript. We have also reviewed the rest of the document to ensure overall formatting consistency.
We appreciate Reviewer #1’s careful comments on the rigor of the evolutionary framing and on the presentation of the manuscript. The revisions replace the landscape-altering language with statements about local neighborhoods, correct the inconsistent proportion reported in the Abstract, revise the two section titles so that they no longer restate a definitional property, number all equations, and improve the readability of Figures 1A, 1C, 2D, and S8.
Reviewer #2 (Public review):
Summary:
This manuscript presents an interesting and conceptually valuable analysis of compensatory evolution using a large combinatorial deep-mutational-scanning dataset for yeast His3p.
I particularly like the identification of "super compensatory" substitutions that improve fitness across diverse genetic backgrounds and apparently reduce the sensitivity of the local fitness landscape to subsequent mutations. The work connects epistasis, protein stability, mutational robustness, and evolvability in a clear and potentially broadly relevant manner.
The authors provide several complementary lines of evidence in support of this central conclusion. In particular, the new experimental validation of S189A is an important strength because it directly demonstrates that a predicted super compensator can buffer the effects of diverse deleterious substitutions, while analyses of additional DMS datasets from other proteins and assay systems suggest that the phenomenon is not restricted to the original His3p landscape.
We first appreciate Reviewer #2’s positive assessment of the conceptual value of the study, and in particular the recognition that the work connects epistasis, protein stability, mutational robustness, and evolvability, and that the new experimental validation of S189A is an important strength. We are also grateful for the three specific and constructive suggestions on structure-aware modelling, on the scope of the ProteinGym analysis, and on tree-aware testing of ortholog co-occurrence. These suggestions led to the largest additions in this revision. We have carefully considered each point, and our responses and the corresponding revisions are detailed below.
Weaknesses:
(1) The structural analysis currently relies primarily on correlations with RSA, weighted contact number, conservation, and Rosetta-predicted changes in folding or binding energy. For super compensators, the mechanistic evidence is largely limited to predicted stabilization and individual examples, such as the proposed salt bridge between 110D and R112. I believe that the newly developed structure-aware deep-learning approaches could provide useful information on the mechanism of super compensators. For example, an inverse-folding model such as ESM-IF1 could score complete multi-mutant sequences conditioned on the His3p backbone and test whether adding a super compensator restores sequence-structure compatibility across backgrounds. More recent multimodal mutation-effect or stability models could similarly be used to cross-check the Rosetta results, including models that explicitly support combinatorial mutations. I would not recommend simply comparing AlphaFold confidence scores between mutants, because current structure predictors are not necessarily sensitive to subtle mutation-induced energetic or conformational changes.
Following the reviewer's suggestion, we scored complete multi-mutant His3p sequences with ESM-IF1 (esm_if1_gvp4_t16_142M_UR50) conditioned on the 6EZM backbone, comparing exact measured genotype pairs that differ only by the state of interest (up to 1,000 backgrounds per state; 7,000 pairs). Five of the seven reported super compensatory substitutions in the Table S1 increased sequence–backbone compatibility: 144N (+0.0160), 169R (+0.0115), 110D (+0.0086), 189A (+0.0021) and 93V (+0.0016), each with a bootstrap interval excluding zero. Two decreased (73A, −0.0153; 137G, −0.0080). Against score-blind matched controls the contrast favoured the reported state for those same five (exact two-sided binomial P = 0.45). All seven directions were preserved in a contacting-chain context (chains A, R and L; Cα within 8 Å). We also used these scores to cross-check the archived Rosetta energies over the 1,217 exact pairs carrying archived entries on both sides (Zenodo 17769278). Higher archived energy accompanies lower measured fitness, so concordance would appear as a negative correlation; the observed Spearman correlations are positive (ρ = +0.085 to +0.094 pooled, +0.200 to +0.211 within focal state). The two predictors therefore do not track one another. We did not compare AlphaFold confidence scores between mutants.
In a word, ESM-IF1 supports the idea that most supercompensatory substitutions can promote the folding of His3p.
(2) The manuscript states that the pipeline was applied to 217 ProteinGym datasets and concludes that super compensators are broadly distributed across proteins and assays. However, this central generalization is described in only a few sentences and is largely relegated to Figure S7. The Methods do not explain which datasets contained sufficient combinatorial mutants to calculate compensatory ability or buffering, how many genotype pairs or quadruplets were available per substitution, or how differences in assay scale and library design were handled. This point requires clarification because super compensation is inherently a background-dependent property and cannot be established from single-mutant measurements alone. ProteinGym is widely used as a substitution-effect benchmark, and many of its constituent assays primarily contain single substitutions; for example, an analysis of an earlier ProteinGym collection reported that 76 of 87 assays contained only single substitutions. It is therefore unclear how the same compensatory-interaction pipeline could be applied uniformly to all 217 datasets.
We thank the reviewer for the suggestions. We have re-performed this analysis based on the pinned PG_v1.3 manifest. The 217 DMS assays cover 186 unique proteins. To identify super-competitors, we filtered for DMS datasets containing multiple substitutions per genotype—specifically requiring at least 10 sets of quadruplet genotypes to evaluate whether a specific amino acid state can mitigate mutational effects. This strict filtering yielded four qualified DMS datasets: three assayed for in vitro protein folding stability using cDNA display proteolysis (E3 ubiquitin-protein ligase AMFR, iron-regulated surface determinant protein H, and E3 SUMO-protein ligase CBX4; Tsuboyama et al., 2023), and one assayed for fluorescence intensity via FACS (green fluorescent protein 2; Gonzalez Somermeyer et al., 2022). We have updated the Methods section to detail this selection process.
(3) The analysis of 335 His3p orthologs in Discussion is potentially very interesting, but co-occurrence between super compensators and putatively deleterious amino-acid states does not by itself demonstrate evolutionary compensation. Closely related species share substitutions through common ancestry, and both states could be associated with a particular lineage or ecological context. A tree-aware analysis would considerably strengthen this result. The authors could reconstruct ancestral states and ask whether acquisition of a super compensator tends to precede or accompany otherwise deleterious substitutions. Alternatively, they could use phylogenetically informed permutations that preserve substitution frequencies and shared ancestry.
We agree. Co-occurrence among living species is not by itself evidence of compensation, because related species inherit substitutions from a common ancestor. We have therefore redone the analysis on a phylogeny, using the phylogenetically informed permutation the reviewer suggests.
We realigned the archived orthologs with MAFFT L-INS-i and built a maximum-likelihood tree with IQ-TREE: 329 species, 225 alignment columns, the Q. YEAST model selected by BIC, with 1,000 ultrafast-bootstrap and 1,000 SH-aLRT replicates. Six rows carrying three ambiguous duplicate species labels were removed, which also corrects the earlier figure caption that stated 355 species. We then tested 28 substitution pairs against a null in which both substitutions are simulated on the tree and thresholded to their observed frequencies, so the null preserves both how common each substitution is and how the species are related.
Two pairs stand out, and both involve 189A. 189A occurs together with 204I in 112 species, where the tree-based null expects 78 — an excess of 34 species. 189A occurs with 211E in 66 species against an expectation of 43 — an excess of 23. Both excesses are significant on their own under the tree-based simulation (p = 0.021 and 0.036, from 100,000 simulations) and under a separate Pagel test of correlated evolution (p = 0.046 and 0.023). No other pair reaches significance under both tests. 189A is also the substitution we validated experimentally, so the strongest evolutionary signal and the experimental result point to the same substitution.
We note two limits. Neither pair survives correction for having tested 28 pairs. And both pairs involve common substitutions (189A is present in 177 of the 329 species), so part of their high rank may reflect the greater statistical power available for common substitutions. We therefore present these as the strongest associations in the data rather than as proof of historical compensation.
We sincerely thank Reviewer #2 for recommending a broader mechanistic and evolutionary evaluation. The added ESM-IF1 analysis, the re-performed ProteinGym dataset selection, and the tree-aware analysis of ortholog co-occurrence provide more direct evidence for the properties of super compensatory substitutions, and we have stated the remaining limitations of each analysis explicitly.
Reviewer #3 (Public review):
The manuscript by Jiang and co-authors presents an analysis of experimental measurements (about 400k variants) from a deep mutational scan of the HIS3 enzyme. The authors assess the ability of a genotype to be "rescued" and show that this depends on mutation sites (in particular their solvent accessibility) and mutation effects (should be mild on folding stability or binding affinity). They further identify a set of super-compensatory mutations, and their results suggest that these mutations flatten the fitness landscape.
This finding is interesting and likely of interest to a broad community. The analysis seems sound. However, I have a number of major concerns regarding the presentation and positioning of the work.
We sincerely thank Reviewer #3 for the careful reading of our manuscript and for the positive comments that the finding is “interesting and likely of interest to a broad community” and that the analysis “seems sound.” The concerns regarding the positioning of the work relative to Pokusaeva et al. (2019), the description of the model used to estimate fitness potentials, the structural and citation details, and the sensitivity of rescuability to the threshold choices were valuable in improving the clarity and the rigor of the manuscript. We address each point below.
(1) It would improve the manuscript to clarify the present contribution with respect to a previous study by the same authors, namely Pokusaeva et al. 2019. Did the authors apply the same protocol to generate a new library of mutants, or did they re-analyse an already published library? If the library is not new, ambiguous sentences like "Nevertheless, to our knowledge, the His3p library remains one of the largest and most comprehensive resources that contains multi-site mutants" should be reformulated.
We thank the reviewer for noting this ambiguity; we agree and will revise accordingly. The large-scale His3p landscape was reported in Pokusaeva et al. (2019), and no new version was constructed here. Instead, we provide a computational re-analysis of those measurements to quantify rescuability, broad positive effects of super compensatory substitutions, and local buffering of fitness effects, plus a newly generated targeted DMS validation library (randomizing positions 181 and 202 in WT S189 vs. 189A) that experimentally validates compensation. To clarify provenance, we will change the sentence “Nevertheless, to our knowledge, the His3p library remains one of the largest...” to “While the large-scale library was measured previously (Pokusaeva et al., 2019), the current work combines a newly generated targeted dataset with a fresh re-analysis of this public His3p library to reveal previously unappreciated rules of compensation.” This revision clearly separates prior data from our novel contributions.
(2) Pokusaeva et al. 2019 is cited for the library and also for the deep neural network. It would be beneficial to briefly describe the architecture, the inputs and outputs, and the training procedure. Was the network trained on the current library? What is the purpose of this network? It looks more like an additive linear model (except for the global sigmoid) than a deep neural network. How does it relate to global epistasis models? The sigmoid function is designed to capture plateauing effects; doesn't that introduce some circularity issue in the reasoning?
Pokusaeva et al. (2019) describes a three-layer feed-forward model that is best understood as a global-epistasis model rather than a conventional deep neural network. The input is a one-hot encoding of amino-acid states. These inputs are first mapped to a one-dimensional additive latent variable, in which the state-specific coefficients are summed to produce a genotype-level latent “fitness potential.” That latent value is then passed through a learned nonlinear output layer with 22 units to generate the predicted fitness. The model was trained on the current library.
Its purpose is to separate the intrinsic contribution of each amino-acid state from the background-dependent saturation of the His3p assay. Raw fitness values are not directly comparable across genetic backgrounds: in already low-fitness backgrounds, additional substitutions may remain phenotypically invisible, whereas in high-fitness backgrounds, mildly deleterious effects may be masked. A global-epistasis formulation addresses this by placing states on an additive latent scale and capturing assay saturation through a monotonic nonlinear link function. In this framework, each state has an estimated coefficient that is interpreted as its background-independent fitness contribution.
This coefficient is not hypothetical; it is explicitly provided in File/DeepLearningWeights/DLWeightsFI.tsv as FI_mean, one row per state. These coefficients are used downstream to quantify each state’s fitness impact, which is essential for showing that supercompensatory substitutions are not defined in a circular way by construction.
(3) Are the super-compensatory mutations observed (conserved) across evolution? Beyond the fact that they are accompanied by mildly deleterious mutations in natural sequences. Can we predict them with variant effect predictors?
We thank the reviewer for these questions. Regarding evolutionary conservation, we have not performed a systematic phylogenetic analysis, as our primary focus here was the experimental characterization of compensation within the His3p system. Nevertheless, our data show that super‑compensatory mutations are consistently stabilizing across backgrounds (Fig. 4L)—precisely the property that makes them robustly beneficial regardless of context. This suggests that these mutations may be identifiable through stability‑predicting tools (e.g., FoldX, DeepDDG), which would flag them as stabilizing. Whether this stabilization is reflected in evolutionary conservation patterns is a separate question; while we observe their co‑occurrence with mildly deleterious variants in natural sequences (as the reviewer notes), we have not systematically tested whether conservation‑based predictors (e.g., EVE, DeepSequence) can predict them.
(4) The AAindex mention should be accompanied by a citation.
We thank the reviewer for the reminder. We will add the appropriate citation for the AAindex database in the revised manuscript
(5) Equations should be numbered. WCN formula seems to contain misformatting issues.
We thank the reviewer for the reminder. We numbered all equations sequentially and correct the formatting errors in the WCN formula.
(6) A more explicit description of the structural data analysed (which PDB entry?) should be provided.
We thank the reviewer for the reminder. The PDB entry used is 6EZM.
(7) I believe the citation Van Cleve and Weissman 2015 for the ProteinGym benchmark is incorrect. Additionally, is the Rosetta citation adequate?
We thank the reviewer for pointing out these citation issues. We have double-checked the references and agree with these concerns.
Regarding the Rosetta citation, we acknowledge that there is no single “Rosetta citation”. In our work, we used the ddg_monomer function for ΔΔG_fold calculations and the flex ddG function for ΔΔG of interface binding calculations. Therefore, we cited the corresponding methodological papers: Kellogg et al. (2011) for ddg_monomer and Barlow et al. (2018) for flex ddG.
(8) How is the definition of rescueability sensitive to the threshold choice?
We thank the reviewer for raising this important issue. To systematically evaluate the robustness of our rescuability measurements, we tested three key parameters: (i) the fitness cutoff used to define unfit genotypes, (ii) the minimum number of genotypes in the superset required for an unfit genotype to be considered and (iii) the fitness cutoff used to define fit genotypes. The first two parameters collectively determine the size of the unfit genotype set, while the third controls how rescuability was calculation.
As shown in Fig. S1D of the manuscript, varying the fitness cutoffs for defining both unfit and fit genotypes has only a minor effect on the calculated rescuability, as reflected by the highly correlated rescuability values across different cutoff combinations.
Besides, the primary goal was to examine how rescuability correlates with three biochemical features of each position in His3p: relative solvent accessibility (RSA), weighted contact number (WCN), and evolutionary conservation. When we applied different fitness cutoffs to define unfit genotypes while with at least 10 genotype in the superset, the correlations between rescuability and these biochemical features remained highly consistent (see Author response image 1A-D). This demonstrates that the observed associations between rescuability and RSA, WCN, and conservation are robust to the choice of fitness cutoff used to filter the unfit genotype sets.
We next assessed the sensitivity of our results to the superset (the whole genotypes with additional substitutions) threshold. Using a fixed fitness cutoff of zero to classify unfit genotypes, we found that, although this shifted the fraction of genotypes classified as unfit, the observed correlations between rescuability and the three biochemical features were largely unchanged, even when the superset was defined by as few as a single genotype (see Author response image 1E-F).
In summary, despite variations in the parameter settings used to filter unfit genotypes for rescuability calculation, the overarching conclusion—that rescuability is consistently correlated with RSA, WCN, and conservation—remains robust and reproducible across all tested conditions.
Author response image 1.
Different rescuability calculation methods and filtering thresholds produce similar results. (A-F) Different filtering thresholds used to calculate the average rescuability for each position of the monomer of His3p give similar results. (A-B) The average rescuability for each position along His3p for unfit genotype with fitness < 0.5. The total count of genotypes containing additional substitutions is at least 10. (C-D) The average rescuability for each position along His3p for unfit genotype with fitness < 1. The total count of genotypes containing additional substitutions is at least 10. (E-F) The average rescuability for each position along His3p for unfit genotype with fitness = 0 and the total count of genotypes containing additional substitutions is at least 1.
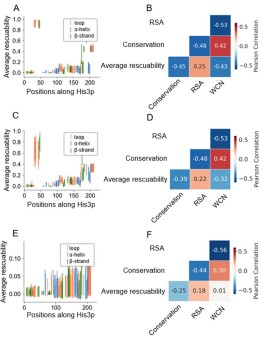
We are grateful to Reviewer #3 for the questions on data provenance, model description, structural data, citations, and threshold sensitivity. The revisions separate the previously published library from the newly generated targeted dataset, describe the global-epistasis model and its role explicitly, correct the citations, and document the robustness of rescuability across all tested filtering thresholds.
La Gen Z mobilisée dans le mouvement lycéen n'est pas pressée de connaître la fin de One Piece prévue par Oda, ni la fin de leur mouvement, ça ne l'intéresse même pas tant que ça — elle préfère perpétuer et prolonger l'aventure
Nyasha,’ I said as she walked past me, but she did not answer. I followed her to the servants’ quarters, where we sat, she smoking a cigarette held between shaking fingers and I feeling bad for her and thinking how dreadfully familiar that scene had been, with Babamukuru condemning Nyasha to whoredom, making her a victim of her femaleness, just as I had felt victimised at home in the days when Nhamo went to school and I grew my maize. The victimisation, I saw, was universal. It didn’t depend on poverty, on lack of education or on tradition. It didn’t depend on any of the
Comment: Tambu sees that every woman, rich or poor, educated or not, is a victim simply for being female. Even a "good" and respected man like Babamukuru still views women as inferior. After seeing him beat Nyasha and call her a whore, Tambu grasps that the cause is not poverty, education, or tradition alone. Men take this attitude with them wherever they go. The conflict always comes back to femaleness being seen as weaker and less valuable than maleness. This moment is powerful because it exposes the deep gender struggle in the society: even the family's supposed hero and provider still uses his power to control and punish the women around him. It makes Tambu question all she once believed about Babamukuru and about her own place as a girl.
Re write: "Yasha," I called as she passed by, but she gave no answer. I trailed her to the servants' quarters. We sat side by side in silence. With trembling fingers she smoked a cigarette while I watched, filled with deep sadness. The scene was achingly familiar. Babamukuru had just condemned Nyasha as a whore, making her a victim merely for being female just as I had felt victimised at home when Nhamo went to school and I was left to grow maize. In that moment I realised the victimisation of women was universal. It had nothing to do with poverty, education, or tradition. Men carried it with them wherever they went. Even a hero like Babamukuru did it. Nyasha may have been strong-willed and disrespectful, but the deeper problem was this: every conflict circled back to the same painful notion that femaleness was deemed weaker and inferior to maleness.
I would cut some of the long, repetitive sentences that make the original paragraph feel heavy. I also removed the parts that nearly excuse Babamukuru (“you had to admit Nyasha had no tact… she ought to have had lots of respect”) because they weaken Tambu’s realisation. I would add a clearer sense of Tambu’s emotion and make the final realisation stronger and more direct. This way the paragraph focuses more sharply on the gender struggle and feels more powerful.
Deze ethiek noemt hij de juridische vorm van ethiek: een ethiek die is gericht op voorschriften, regels en principes of waarden, die gericht zijn op het handhaven van een gemeenschap.
foucault is geen voorstander van een juridische vorm van ethiek
eLife Assessment
This valuable study links NAD⁺-dependent HSD3B6 steroidogenic activity, androgen receptor signaling, and CD38-associated inflammation to meibomian gland atrophy, suggesting a potentially targetable feedback cycle relevant to dry eye disease. The revised work provides solid evidence for this relationship, with additional measurements showing no significant differences in circulating testosterone or aldosterone and persistence of elevated Cd38 expression and reduced glandular NAD⁺ levels after castration, strengthening support for a local steroidogenic mechanism. However, the global knockout does not definitively establish a gland-specific intracrine mechanism, and the absence of tear-film and ocular-surface functional measurements limits conclusions about the consequences for dry eye disease.
Reviewer #1 (Public review):
Summary:
The authors provide a compelling story linking NAD dependent HSD3b6 gene expression in the eyelid to a viscous cycle involving decreased steroidogenesis and AR signaling, pro-inflammatory cytokine release, inflammation, CD38 activation and further NAD+ decline that induces meibomian gland atrophy leading to dry eye disease. The work follows on studies published by the authors in Nature Aging and uses a previously reported HSD3b6 knockout mouse to try and show meibomian gland atrophy, inflammation and CD38+ cell recruitment. Overall the data presented does not appear to support the authors conclusions, and the described interactions seem to be overstated, in that if HSD3b6 was critical to meibomian gland function, one might expect complete loss of the meibomian gland in knockout mice, which is not the case.
Comments on revised version:
It should be noted that while the authors indicate the CD38 is significantly up-regulated in the HSD3b6 KO mouse, the increase was not sufficient to show a significant adjusted P-value after revision of the manuscript. Bulk RNA sequencing also shows no significant change in meibum lipid gene expression for aged mice that are treated with 78c, an inhibitor of CD38, that the authors indicate increases NAD levels leading to increased meibomian gland size compared to vehicle treated mice. Unfortunately, there was no increase in meibum lipid gene expression with 78c or with 78c+NMN treatment as identified by adjusted P-value.
Reviewer #2 (Public review):
Summary:
In the manuscript entitled, "NAD boosting mediated by CD38 inhibition drives reversal of a pathological vicious cycle of intracrine activity and inflammation in eyelid meibomian gland dysfunction", the authors demonstrate strong correlations between a pro-inflammatory state, the activity of an intracrine hormone (3 beta-hydroxysteroid dehydrogenase, 3B-HSD) and the NAD co-factor. Specifically, in a 3B-HSD knockout mouse, there was an upregulation in pro-inflammatory cytokines and increased CD38+ cells (CD38 is an enzyme that depletes NAD, a necessary cofactor for 3B-HSD activity). Conversely, induction of inflammation in the eyelids resulted in reductions in 3B-HSD activity. Supplementation with 5 alpha-dihydrotestosterone (DHT) or the NAD precursor NMN, and inhibition of CD38 activity (78c), corrected the pathologies observed in both the 3B-HSD knockout mouse and the pro-inflammatory model (LPS injection into eyelids).
Strengths:
The experiments were performed with good rigor, assessing the impact of inflammation and 3B-HSD activity using multiple model systems. The endpoints represented a combination of transcriptional changes, protein quantification, enzymatic activity, and immunofluorescent microscopy. The authors use human tissue from both younger and older individuals to justify their hypotheses that increased CD38 + cells and reduced 3B-HSD quantity exist in older individuals. The data provide the foundation for assessing more global changes to the tear film and ocular surface.
Weaknesses:
The main weaknesses of the study include:
(1) An absence of information on meibomian gland health, tear film and ocular surface.
(2) Too few human subjects to validate the hypotheses.
Overall, this study demonstrates an important relationship that exists between intracrine signaling, inflammation and cofactor signaling, and represents a novel approach in therapeutic design for patients with meibomian gland dysfunction.
Comments on the revised version:
The title of the manuscript is a bit deceiving, particularly because it mentions "meibomian gland dysfunction". The authors would need to demonstrate abnormalities in lipid synthesis (quantity or quality) and ocular surface changes associated with loss of this intracrine signaling. The data presented are strong for demonstrating the role of NAD synthesis and utilization in meibomian gland homeostasis, but do not explain the role in ophthalmic diseases, such as MGD. This could possibly be applicable to forms of blepharitis or conjunctivitis as well given their findings of CD38+ cells present in the eyelids of the KO mice. Therefore, the authors should remove the claims of meibomian gland dysfunction in the title and comments in the abstract. Instead, they could use meibomian gland homeostasis for both sections.
Author response:
The following is the authors’ response to the original reviews.
Public Reviews:
Reviewer #1 (Public review):
Summary:
While the results show some loss in the eyelid meibomian glands, there is significant gland retention in HSD3b6 KO mice, as shown in Figure 2. This is supported by the lack of DEG patterns showing downregulation of Meibum lipid genes (AWAT2, Far2, Soat1, Plin2, SCD, etc.), and no decrease in Pparg expression, known to be critical for meibomian gland lipid gene expression.
Weaknesses:
It should be noted that while the authors indicate that CD38 is significantly up-regulated in the HSD3b6 KO mouse, the increase was not sufficient to show a significant adjusted P-value. Bulk RNA sequencing also shows no significant change in meibum lipid gene expression for aged mice that are treated with 78c, an inhibitor of CD38, which the authors indicate increases NAD levels, leading to increased meibomian gland size compared to vehicle-treated mice.
Unfortunately, there was no increase in meibum lipid gene expression with 78c, as identified by adjusted P-value. However, it should be noted that the supplemental file covering DEG expression was labeled as a Microarray analysis. This did not include the 78c+NMN treated mice, which the authors contend show a more impactful effect on the meibomian gland.
We thank the reviewer for the careful evaluation of our work and for the constructive comments regarding the interpretation of the transcriptomic data and the molecular basis of meibomian gland dysfunction.
First, regarding the statistical significance of Cd38 expression in the microarray analysis, we performed additional validation using gene-specific quantitative PCR in independent eyelid tarsal plate samples. These new data are now presented in Fig. 2C, and the Results section has been revised as follows:
“… To validate the upregulation of Cd38, we performed real-time PCR analysis using gene-specific primers in independent eyelid tarsal plate samples, which confirmed a significant increase in Cd38 expression in Hsd3b6<sup>−/−</sup> mice compared to Hsd3b6<sup>+/+</sup> controls. This difference was also observed in castrated mice; thus, the effect of Hsd3b6 deletion on Cd38 expression is independent of testicular testosterone (Fig. 2C).”
Second, we apologize for the error in the original supplementary DEG file, which caused confusion during the review process. We have now replaced it with a complete RNA-seq dataset that includes all expression values for aged mice treated with 78c+NMN (please see Supplementary Data 2). As shown in Fig. 4E, F, treatment with 78c+NMN significantly increased the expression of Elovl4 and Elovl7, elongases responsible for the synthesis of very long-chain fatty acids in the meibomian gland. We also re-examined representative meibum lipid-related genes (Awat2, Far2, Soat1, Plin2, and Scd1). Although none reached statistical significance individually, collective analysis of these representative lipid-related genes by two-way ANOVA with Bonferroni's post hoc test demonstrated a significant overall increase following 78c+NMN treatment in aged mice, compared with controls, supporting coordinated upregulation of the meibomian gland lipid synthesis program.
These analyses indicate that, although the individual lipid-related genes showed only modest changes, they exhibit a coordinated increase following 78c+NMN treatment in aged mice. By contrast, the same gene set showed no significant overall change in young (3-month-old) mice, consistent with the original RNA-seq results presented in Fig. 4E. To better illustrate these findings, we have summarized the expression of these representative genes in a new Supplementary Fig. S5 and revised the Results accordingly, as follows:
“…Furthermore, representative meibum lipid-related genes, including Awat2, Far2, Soat1, Plin2, and Scd1, exhibited a coordinated increase following 78c-NMN treatment (Fig. S5). While the changes in individual genes were modest and did not reach statistical significance (Fig. 4E), analysis of the gene set as a whole demonstrated a significant overall increase compared with vehicle-treated controls.”
“In contrast, the same treatment in young mice did not significantly alter gene expression profiles (Fig. 4E, young), and no coordinated increase was observed for Awat2, Far2, Soat1, Plin2, or Scd1 (Fig. S5). This result is consistent with previous studies [44,47,48] showing that 78c (or NMN) exerts minimal effects in young mice compared with aged mice across multiple physiological parameters, including glucose homeostasis, exercise tolerance, and cardiac function.”
We also would like to note that the complete RNA-seq datasets provided in Supplementary Data 2 allow readers to examine the expression profiles of additional genes of interest.
Finally, regarding the observation that meibomian glands remain partially preserved despite the presence of gland atrophy in Hsd3b6<sup>−/−</sup> mice, together with the limited significant changes in classical lipid-related genes, we agree that this is an important point for interpreting the mechanism(s) of meibomian gland dysfunction. Our previous transcriptomic analysis of FACS-purified meibomian acinar cells in Hsd3b6<sup>−/−</sup> mice (PMID: 37117756) demonstrated reduced expression of genes involved in cell proliferation/differentiation, despite relatively preserved expression of canonical Pparg-dependent lipid genes. Our findings therefore extend the current framework by suggesting that meibomian gland atrophy can occur, at least in part, independently of detectable changes in Pparg expression, supporting the idea that intracrine steroidogenesis contributes to maintaining the proliferative activity of basal acinar cells alongside the Pparg-dependent pathway. Accordingly, we have revised the Discussion to clarify the relationship between our findings and the established Pparg-centred model of meibomian gland maintenance, as follows:
“Although 78c+NMN treatment effectively restored meibomian gland size, the molecular mechanisms underlying this recovery remain incompletely understood. Treatment with 78c+NMN significantly increased the expression of Elovl4, Elovl7, and Hsd3b6. However, representative meibum lipid-related genes, including Awat2, Far2, Soat1, Plin2, and Scd1, exhibited only a modest coordinated increase following treatment. Interestingly, the expression of Pparg, a key transcriptional regulator of meibocyte differentiation and lipid synthesis [88-90], remained unchanged. These findings suggest that restoration of meibomian gland size by 78c+NMN does not require detectable changes in Pparg mRNA expression, although Pparg activity may instead be regulated at the level of protein abundance, subcellular localization, and/or post-translational modifications such as phosphorylation or SUMOylation [88,91].
Our previous transcriptomic analysis of FACS-purified meibomian gland basal acinar cells (meibomian precursor cells expressing androgen receptors) from Hsd3b6<sup>−/−</sup> mice demonstrated impaired expression of genes involved in cell proliferation and differentiation despite relatively preserved expression of lipid-related genes [6]. In contrast, a recent single-cell study showed that Pparg expression progressively increases during meibocyte differentiation, although it is already detectable in basal acinar cells [92]. These observations suggest that Hsd3b6-dependent intracrine activity primarily supports the maintenance and proliferation of basal acinar cells, whereas the canonical Pparg pathway predominantly regulates subsequent meibocyte differentiation and lipid synthesis. Together, these findings suggest that Hsd3b6 dependent intracrine activity contributes to meibomian gland homeostasis through mechanisms that complement the Pparg-associated pathway. Thus, our findings extend the current framework by indicating that meibomian gland homeostasis is maintained not only through canonical PPARγ-mediated regulation but also through intracrine steroidogenesis.
Newly added references:
(88) Jester, J.V., Potma, E., and Brown, D.J. (2016). PPARγ Regulates Mouse Meibocyte Differentiation and Lipid Synthesis. Ocul Surf 14, 484-494. 10.1016/j.jtos.2016.08.001.
(89) Kim, S.W., Xie, Y., Nguyen, P.Q., Bui, V.T., Huynh, K., Kang, J.S., Brown, D.J., and Jester, J.V. (2018). PPARγ regulates meibocyte differentiation and lipid synthesis of cultured human meibomian gland epithelial cells (hMGEC). Ocul Surf 16, 463-469. 10.1016/j.jtos.2018.07.004.
(90) Hwang, H.S., Parfitt, G.J., Brown, D.J., and Jester, J.V. (2017). Meibocyte differentiation and renewal: Insights into novel mechanisms of meibomian gland dysfunction (MGD). Exp Eye Res 163, 37-45. 10.1016/j.exer.2017.02.008.
(91) Ahmadian, M., Suh, J.M., Hah, N., Liddle, C., Atkins, A.R., Downes, M., and Evans, R.M. (2013). PPARγ signaling and metabolism: the good, the bad and the future. Nat Med 19, 557-566. 10.1038/nm.3159.
(92) Zhu, X., Xu, M., Portal, C., Lin, Y., Ferdinand, A., Peng, T., Morrisey, E.E., Dlugosz, A.A., Castellano, J.M., Lee, V., et al. (2025). Identification of Meibomian gland stem cell populations and mechanisms of aging. Nat Commun 16, 1663. 10.1038/s41467-02556907-6.
Reviewer #2 (Public review):
Summary:
In this manuscript, the authors demonstrate strong correlations between a pro-inflammatory state, the activity of an intracrine hormone (3 beta-hydroxysteroid dehydrogenase, 3B-HSD), and the NAD co-factor. Specifically, in a 3B-HSD knockout mouse, there was an upregulation in proinflammatory cytokines and increased CD38+ cells (CD38 is an enzyme that depletes NAD, a necessary cofactor for 3B-HSD activity). Conversely, induction of inflammation in the eyelids resulted in reductions in 3B-HSD activity. Supplementation with 5 alpha-dihydrotestosterone (DHT) or the NAD precursor NMN, and inhibition of CD38 activity (78c), corrected the pathologies observed in both the 3B-HSD knockout mouse and the pro-inflammatory model (LPS injection into eyelids).
Strengths:
The experiments were performed with good rigor, assessing the impact of inflammation and 3BHSD activity using multiple model systems. The endpoints represented a combination of transcriptional changes, protein quantification, enzymatic activity, and immunofluorescent microscopy. The authors use human tissue from both younger and older individuals to justify their hypotheses that increased CD38 + cells and reduced 3B-HSD quantity exist in older individuals. The data provide the foundation for assessing more global changes to the tear film and ocular surface.
Weaknesses:
The main weaknesses of the study include the following:
(1) An absence of information on meibomian gland health, tear film, and ocular surface.
(2) Too few human subjects to validate the hypotheses.
Conclusion:
Overall, this study demonstrates an important relationship that exists between intracrine signaling, inflammation, and cofactor signaling. It represents a novel approach in therapeutic design for patients with meibomian gland dysfunction.
We thank the reviewer for the careful evaluation of our work and for recognizing the novelty and potential therapeutic implications of the relationship among intracrine signaling, inflammation, and NAD metabolism in meibomian gland dysfunction. We also appreciate the reviewer’s constructive comments on the limitations of the present study and areas for improvement in the manuscript.
Regarding the lack of information on meibomian gland health, tear film, and ocular surface, we have added a limitations section to explicitly acknowledge that these functional outcomes were not directly assessed in the present study. As the reviewer kindly noted, we only focused on a key pathological hallmark of MGD, namely age-associated tissue atrophy, and based on this we explored the NAD/3β-HSD/inflammation-mediated mechanism. Thus, a limitation of the present study is the lack of assessment of the downstream consequences of MGD. This point is now explicitly discussed in the manuscript; please note that additional details are provided in our responses to Reviewer #2’s Recommendations for the authors.
Regarding the human data, we added two additional human eyelid samples, increasing the sample size of the older group from 2 to 4. Nevertheless, we agree that the sample size remains limited and have now explicitly acknowledged this limitation in Discussion as follows:
“A caveat of this study is that the number of human eyelid samples analyzed was limited. Larger human cohorts will be necessary to establish the translational relevance of the age-associated CD38 accumulation observed in human tissues.”
Taken together, we believe that these revisions have clarified the scope and limitations of our present study.
Reviewer #3 (Public review):
Summary:
The authors aimed to investigate whether disruption of intracrine steroid hormone metabolism contributes to meibomian gland dysfunction and proposed a "vicious cycle" of gland dysfunction and inflammation, using a global Had3b6 knockout mouse model. The work addresses an important aspect of MGD, but its impact may be limited unless the intracrine mechanism can be more clearly distinguished from systemic hormonal effects.
Strengths:
This study addressed an important question. The hormonal regulation of the meibomian gland has long been recognized. If clarified, the concept of local steroid metabolism influencing gland homeostasis could have implications for understanding disease mechanisms and identifying therapeutic targets.
Weaknesses:
The use of a global knockout makes it difficult to separate local intracrine effects from systemic hormonal changes, and key controls and hormone measurements are lacking. LPS-induced inflammation may not reflect the chronic nature of MGD.
We thank the reviewer for the thoughtful evaluation of our work and for highlighting the importance of distinguishing local intracrine mechanisms from systemic hormonal effects. In response, we performed several additional experiments and substantially revised the manuscript. Specifically, we measured plasma testosterone and aldosterone levels and found no significant differences between Hsd3b6<sup>−/−</sup> and Hsd3b6<sup>+/+</sup> mice. In addition, we repeated key experiments in castrated mice and observed that the effects of Hsd3b6 deletion on tarsal plate Cd38 expression and meibomian NAD levels were preserved despite the absence of testicular testosterone. These new findings provide additional support for a local intracrine mechanism in the eyelid. We also revised the Introduction and Discussion to better explain the proposed intracrine–inflammation vicious cycle and clarified the rationale and limitations of the LPS-based inflammation model, including its inability to fully recapitulate the chronic low-grade inflammation characteristic of MGD. Further details are provided in our responses to Reviewer #3’s Recommendations for the authors. We hope that these additions and revisions have strengthened the manuscript and addressed the reviewer’s concerns.
Recommendations for the authors:
Reviewer #1 (Recommendations for the authors):
Overall, the authors need to provide bulk RNA sequencing data for all treatment groups and provide some explanation of the measurements in individual mice for gland growth.
We thank the reviewer for this helpful comment. We have now replaced the original supplementary file with a complete RNA-seq dataset that includes all treatment groups (Supplementary Data 2). In addition, as described in our response to the Public Review comment above, we extensively revised our manuscript to provide explanation of gene expression profiles (particularly, representative meibum lipid-related genes) in the dataset.
Accordingly, we have expanded the Results and reconstructed the Discussion by incorporating two new discussion paragraphs. The relevant revisions are provided below for your perusal:
“… Furthermore, representative meibum lipid-related genes, including Awat2, Far2, Soat1, Plin2, and Scd1, exhibited a coordinated increase following 78c-NMN treatment (Fig. S5). While the changes in individual genes were modest and did not reach statistical significance (Fig. 4E), analysis of the gene set as a whole demonstrated a significant overall increase compared with vehicle-treated controls.”
“In contrast, the same treatment in young mice did not significantly alter gene expression profiles (Fig. 4E, young), and no coordinated increase was observed for Awat2, Far2, Soat1, Plin2, or Scd1 (Fig. S5). This result is consistent with previous studies [44,47,48] showing that 78c (or NMN) exerts minimal effects in young mice compared with aged mice across multiple physiological parameters, including glucose homeostasis, exercise tolerance, and cardiac function.”
“Although 78c+NMN treatment effectively restored meibomian gland size, the molecular mechanisms underlying this recovery remain incompletely understood. Treatment with 78c+NMN significantly increased the expression of Elovl4, Elovl7, and Hsd3b6. However, representative meibum lipid-related genes, including Awat2, Far2, Soat1, Plin2, and Scd1, exhibited only a modest coordinated increase following treatment. Interestingly, the expression of Pparg, a key transcriptional regulator of meibocyte differentiation and lipid synthesis [88-90], remained unchanged. These findings suggest that restoration of meibomian gland size by 78c+NMN does not require detectable changes in Pparg mRNA expression, although Pparg activity may instead be regulated at the level of protein abundance, subcellular localization, and/or post-translational modifications such as phosphorylation or SUMOylation [88,91].
Our previous transcriptomic analysis of FACS-purified meibomian gland basal acinar cells (meibomian precursor cells expressing androgen receptors) from Hsd3b6<sup>−/−</sup> mice demonstrated impaired expression of genes involved in cell proliferation and differentiation despite relatively preserved expression of lipid-related genes [6]. In contrast, a recent single-cell study showed that Pparg expression progressively increases during meibocyte differentiation, although it is already detectable in basal acinar cells [92]. These observations suggest that Hsd3b6-dependent intracrine activity primarily supports the maintenance and proliferation of basal acinar cells, whereas the canonical Pparg pathway predominantly regulates subsequent meibocyte differentiation and lipid synthesis. Together, these findings suggest that Hsd3b6-dependent intracrine activity contributes to meibomian gland homeostasis through mechanisms that complement the Pparg-associated pathway. Thus, our findings extend the current framework by indicating that meibomian gland homeostasis is maintained not only through canonical PPARγ-mediated regulation but also through intracrine steroidogenesis.”
Reviewer #2 (Recommendations for the authors):
The main suggestion for the study is the correlation with meibomian gland function. While the study correlates changes with 3B-HSD activity, pro-inflammatory cytokines, and NAD cofactor levels, there is little support describing the pathological changes to the meibomian glands and the impact on the tear film and ocular surface. The changes in the lipid profiles, tear film stability, aqueous tear production, ocular surface staining properties, corneal epithelial transcriptional abnormalities, and leukocyte infiltration into the corneal stroma could all be assessed. While the authors have done a thorough job of demonstrating the correlation of the three major factors listed above, the correlation with meibomian gland function is not completely assessed in the study.
We thank the reviewer for this insightful comment. We agree that functional assessments such as tear film stability, ocular surface pathology, lipid composition, and other downstream manifestations of MGD would complement the mechanistic findings reported here and provide additional insight into their physiological consequences.
However, the primary objective of the present study was to define the molecular mechanism underlying MGD, specifically the pathological interaction between meibomian gland intracrine activity and inflammation, and the role of the CD38–NAD axis in this process. Accordingly, our experiments were designed to focus on mechanistic endpoints directly related to this hypothesis, including 3β-HSD activity, NAD availability, inflammatory gene expression, and CD38 accumulation. In addition, we assessed a key pathological hallmark of MGD, namely age-associated meibomian gland atrophy and its recovery following 78c/NMN treatment.
While direct evaluation of tear film and ocular surface parameters was beyond the scope of the present mechanistic study, we agree that such analyses represent important future directions. To acknowledge this, we have added the following statement to the Discussion:
“… Firstly, while this study focused on defining the molecular and structural mechanisms underlying meibomian gland dysfunction, functional outcomes such as tear film stability, ocular surface integrity, meibum lipid composition, and other clinically relevant manifestations of disease were not directly assessed. Given the well-established link between meibomian gland dysfunction and tear film instability [57-59], future studies incorporating these functional assessments will be important to determine how the molecular and structural changes identified here contribute to ocular surface pathology and disease progression.”
The description of the vicious cycle seemed a bit out of place in the introduction. This would have been most appropriate in the conclusion/discussion in the manuscript. The general nature of the description lacked focus on the eyelids and meibomian glands, and the narrative took time to get to the interactions that would be assessed in the study.
We thank the reviewer for this insightful suggestion. We agree that the original Introduction placed excessive emphasis on the general concept of vicious cycles and that the discussion of disease-wide examples diverted attention from the specific focus of the present study on the meibomian gland.
In response, we substantially shortened and refocused the Introduction. Specifically, we removed the broad descriptions of vicious cycles in neurodegenerative, metabolic, and cardiovascular diseases. The revised Introduction now introduces the concept of a vicious cycle only briefly and moves more directly to the biological context of meibomian gland dysfunction and local intracrine steroidogenesis.
At the same time, we agree that the broader implications of this concept are better suited for the Discussion. We therefore added a brief concluding paragraph to discuss how our findings may inform the understanding of age-associated vicious-cycle processes in other diseases and may also provide a framework for considering intracrine-related pathology beyond the meibomian gland. The corresponding text has been added to the Discussion, as follows.
“Finally, although the present study focused on the eyelid meibomian gland, the concept of an intracrine–inflammation vicious cycle may have broader relevance. Self-reinforcing pathological processes are implicated in several age-associated diseases, and altered intracrine activity has been described in multiple extra gonadal and cancerous tissues [5,7,8,93,94]. Our findings may therefore provide a useful framework for understanding how local hormone metabolism contributes to the initiation and maintenance of tissue-specific pathological cycles during ageing.”
Reviewer #3 (Recommendations for the authors):
(1) Introduction:
(a) The first paragraph of the introduction defines the term "vicious cycle," but its relevance to the current study is low. It is not until line 54 that the specific tissue of interest is introduced. It is suggested that the beginning of the introduction be shortened to emphasize information that is directly relevant to the study.
We thank the reviewer for this helpful suggestion. We agree that the original opening of the Introduction was too general and that the specific focus of the study on the meibomian gland should be introduced earlier.
In response, we substantially shortened the first part of the Introduction. Specifically, we removed the broad discussion of vicious cycles across multiple disease contexts and revised the opening so that the concept of a vicious cycle is introduced only briefly. The revised Introduction now moves directly to the relevance of local intracrine steroidogenesis in the eyelid meibomian gland, thereby better emphasizing the biological context and focus of the present study.
At the same time, we recognized that some of the broader implications of the study remain important. Therefore, we incorporated these points into the Discussion, where we briefly discuss the potential relevance of intracrine–inflammation vicious cycles to other age-associated diseases and intracrine-related pathologies beyond the meibomian gland, as follows:
“Finally, although the present study focused on the eyelid meibomian gland, the concept of an intracrine–inflammation vicious cycle may have broader relevance. Self-reinforcing pathological processes are implicated in several age-associated diseases, and altered intracrine activity has been described in multiple extragonadal and cancerous tissues [5,7,8,93,94]. Our findings may therefore provide a useful framework for understanding how local hormone metabolism contributes to the initiation and maintenance of tissue-specific pathological cycles during ageing.”
(b) In the introduction, the authors should also include common types of intracrine hormones, such as DHT.
We thank the reviewer again for this valuable suggestion. In response, we revised the Introduction to include representative examples of intracrine steroid hormones, including 5α-dihydrotestosterone (DHT) and estrogens, together with a brief description of their local production and action within peripheral tissues. We believe that this addition helps clarify the concept of intracrinology for readers less familiar with the field.
“Common examples of intracrine steroid hormones include 5α-dihydrotestosterone (DHT) produced in the skin, prostate, and eyelid meibomian glands, as well as estrogens synthesized within the breast and endometrium [3-8]. These locally produced hormones act within the tissue in which they are synthesized.”
(c) The hypothesis of a "vicious cycle" in MGD is not fully explained. Specifically, how intracrine steroids drive the meibomian gland into a vicious cycle is not described. The current information only discusses a possible association between steroid hormones and meibomian gland health.
According to this important suggestion, we performed additional experiments and rewrote our introduction. Please note that plasma testosterone levels were not impaired in Hsd3b6<sup>−/−</sup> mice and their eyelid proinflammatory phenotypes (compared to wt mouse eyelid) remained preserved in castrated mice. These data are now provided, by performing additional experiments (please see our replies to your comments, below). Taking these observations into account, we have tempered our introduction.
(2) Results:
(a) One major concern is that sex hormones have long been recognized to be associated with the meibomian gland and have been extensively studied (see the TFOS guidelines). There have also been clinical trials using androgens to treat MGD. With the global knockout of Had3b6, systemic sex hormone levels could also be altered, which may result in MGD (estrogens are synthesized from androgens and would therefore also be affected).
This thoughtful concern is well received, as we were not attentive to describe systemic testosterone in Hsd3b6<sup>+/+</sup> and Hsd3b6<sup>−/−</sup> mice in our original manuscript (for which we should apologize). The corresponding plasma testosterone data are now incorporated as Fig. S1A and presented below for your perusal.
Importantly, plasma testosterone levels in Hsd3b6<sup>−/−</sup> mice were comparable with those in wt Hsd3b6<sup>+/+</sup> mice, consistent with the known compensatory role of the paralogous enzyme Hsd3b1 in the mouse testis [21], which was confirmed to be expressed in Hsd3b6<sup>−/−</sup> mice (see new Fig. S1B). This type of compensation by paralogous steroidogenic enzymes has also been reported in other knockout model, such as Hsd17b3<sup>−/−</sup> mice, in which circulating testosterone levels were preserved due to a compensatory role of Hsd17b12 in the testis (new refs [83,84]). Based on these results, we rewrote our Results and Discussion, as follows.
“plasma testosterone levels were indistinguishable between Hsd3b6<sup>−/−</sup> and Hsd3b6<sup>+/+</sup> mice (Fig. S1A), consistent with the known compensatory role of the paralogous enzyme Hsd3b1 in the mouse testis [21], which was confirmed to be expressed in Hsd3b6<sup>−/−</sup> mice (Fig. S1B). These results indicate that local steroidogenic activity in the eyelid exerts anti-inflammatory effects independent of circulating testosterone levels.”
“For the interpretation of our meibomian intracrine activity model, it is important to note that in Hsd3b6<sup>−/−</sup> mice, plasma testosterone levels were maintained at the levels comparable with those in Hsd3b6<sup>+/+</sup> mice (Fig. S1A). This appears due to a redundant expression of Hsd3b1 in the testis [6], although in the meibomian gland, Hsd3b6 is the sole enzyme (Fig. S1B) and accordingly its deletion causes the complete abolition of meibomian 3β-HSD activity [6]. The resilience of plasma testosterone levels has also been reported in a knockout mouse model deficient in Hsd17b3, a member of 17-ketosteroid reductase enzyme family required for the formation of testosterone [83], likely due to a potential compensatory role of the paralogous enzyme Hsd17b12 in the testis [84]. The Hsd3b6<sup>−/−</sup> vs. Hsd3b6<sup>+/+</sup> phenotypes in the tarsal plate Cd38 expression and meibomian NAD levels were preserved in castrated mice (Fig. 2C, F), which provide additional evidence to support that non-systemic local steroidogenic activity in the eyelid, rather than circulating testicular testosterone, underlies the phenotypes observed in Hsd3b6<sup>−/−</sup> mice.”
Newly added references:
(83) Lawrence, B.M., O'Donnell, L., Gannon, A.L., Smith, S., Curley, M.K., Darbey, A., Mackay, R., O'Shaughnessy, P.J., Smith, L.B., and Rebourcet, D. (2024). Compensatory mechanisms that maintain androgen production in mice lacking key androgen biosynthetic enzymes. FASEB J 38, e70177. 10.1096/fj.202402093R.
(84) Rebourcet, D., Mackay, R., Darbey, A., Curley, M.K., Jørgensen, A., Frederiksen, H., Mitchell, R.T., O'Shaughnessy, P.J., Nef, S., and Smith, L.B. (2020). Ablation of the canonical testosterone production pathway via knockout of the steroidogenic enzyme HSD17B3, reveals a novel mechanism of testicular testosterone production. FASEB J 34, 1037310386. 10.1096/fj.202000361R.
- For context, please note that plasma testosterone levels showed substantial inter-individual variability in both genotypes. Such variability is a well-established physiological feature of male mice, reflecting episodic testosterone secretion. Indeed, classical studies showed that variation in testosterone levels within the same mouse sampled on different occasions is comparable to that observed between individual mice, and a recent longitudinal LC–MS/MS study confirmed 10- to 100-fold fluctuations within individual adult male mice (Bartke and Dalterio, 1975, PMID: 1216260; Kettering et al., 2026, PMID: 41880754). Thus, the variability observed in our dataset is consistent with the known physiological dynamics of circulating testosterone in male mice.
(b) To support the hypothesis of intracrine regulation in MGD, the following would be essential:
- a local or targeted knockout model, and
- a global knockout with appropriate controls, such as Had3b6+/+ mice combined with gonadectomy.
Otherwise, the current study reflects the role of general steroid hormones in the meibomian gland rather than an intracrine-specific mechanism.
We repeated our experiments using castrated Hsd3b6<sup>−/−</sup> mice. As shown in new Fig. 2C, we observed a significant increase in Cd38 expression in the tarsal plate of Hsd3b6<sup>−/−</sup> mice (n = 6, castrated) as compared to Hsd3b6<sup>+/+</sup> control mice (n = 4, castrated). In addition, in Fig. 2F, we observed a significant decrease in NAD levels in the meibomian gland of Hsd3b6<sup>−/−</sup> mice (n = 3, castrated) as compared to Hsd3b6<sup>+/+</sup> control mice (n = 5, castrated). These results provide additional evidence to support that local steroidogenic activity in the eyelid, rather than circulating testicular testosterone, underlies the phenotypes observed in Hsd3b6<sup>−/−</sup> mice. Based on these results and consideration, we have modified our manuscript as follows.
“… This difference was also observed in castrated mice; thus, the effect of Hsd3b6 deletion on Cd38 expression is independent of testicular testosterone (Fig. 2C).”
“… Note that regardless of castration, Hsd3b6 deletion reduced meibomian gland NAD levels.”
“…The Hsd3b6<sup>−/−</sup> vs. Hsd3b6<sup>+/+</sup> phenotypes in the tarsal plate Cd38 expression and meibomian NAD levels were preserved in castrated mice (Fig. 2C, F), which provide additional evidence to support that non-systemic local steroidogenic activity in the eyelid, rather than circulating testicular testosterone, underlies the phenotypes observed in Hsd3b6<sup>−/−</sup> mice.”
(c) With the knockout of Had3b6, other steroid hormones may also be altered systemically, such as increased synthesis of the mineralocorticoid aldosterone. These hormonal changes could cause systemic effects such as hypertension, with unknown consequences for the meibomian gland. Please provide data on systemic steroid hormone levels to better interpret the current findings.
We thank the reviewer for raising this important point. To address the possibility that systemic mineralocorticoid alterations contribute to the observed meibomian gland phenotypes, we measured plasma aldosterone levels in Hsd3b6<sup>−/−</sup> and Hsd3b6<sup>+/+</sup> mice. These new data are now included as Fig. S6.
Importantly, plasma aldosterone levels were not significantly different between Hsd3b6<sup>−/−</sup> and Hsd3b6<sup>+/+</sup> mice (Fig. S6). This finding is consistent with the known expression pattern of steroidogenic enzymes in the adrenal zona glomerulosa, where both Hsd3b1 and Hsd3b6 are redundantly expressed and contribute to aldosterone biosynthesis (refs. 85-87). Thus, similar to the compensatory role of Hsd3b1 in maintaining systemic testosterone production in the testis, the redundant expression of Hsd3b1 in aldosterone-producing cells likely preserves systemic aldosterone levels in Hsd3b6<sup>−/−</sup> mice.
Based on these new data, we have added the plasma aldosterone measurements as Fig. S6 and revised the Discussion accordingly. These results further support our conclusion that the phenotypes observed in Hsd3b6<sup>−/−</sup> mice are unlikely to be secondary to systemic endocrine alterations and instead reflect the loss of local steroidogenic activity within the eyelid.
“…Plasma aldosterone levels were likewise preserved in Hsd3b6<sup>−/−</sup> mice (Fig. S6), consistent with the redundant expression of Hsd3b6 and Hsd3b1 in the adrenal gland zona glomerulosa cells [85-87].”
(d) What is the age of the mice that underwent microarray analysis? The Methods section only specifies "young" and "old" without providing the actual ages. Although the ages can be inferred from the figures, they should also be clearly stated in the Methods section.
We thank the reviewer for this comment. We have now clarified the age of the mice in the Methods section. All mice used for the microarray analysis were age-matched and were 9 weeks old at the time of tissue collection (please see page 35, lines 818-819).
(e) Line 148: CD11b+ cells in the eye are usually referred to as dendritic cells derived from monocytes that function as antigen-presenting cells (APCs), rather than as phagocytes.
(f) Line 149: How was it determined that the CD38+ cells are macrophages? CD38 can also be expressed by T cells, plasma cells, NK cells, and other immune cell types.
Heeding these important instructions and based on their co-labeling with the myeloid marker CD11b, we have rewritten our Results on the cell identity of CD38 cells, as follows.
“… We also found that the myeloid cell marker CD11b stained the same cells (Fig. S2), indicating an increased number of myeloid immune cells that express CD38 in the tarsal plate of Hsd3b6<sup>−/−</sup> mice (Fig. 2E, vs. Hsd3b6<sup>+/+</sup>).”
In addition, to clarify that multiple immune cell types can contribute to CD38 expression in the tarsal plate and ocular tissues, we have extensively revised our manuscript by adding a new paragraph to the Discussion as follows.
“Secondly, the cellular identity of the CD38-expressing cells observed in the tarsal plate warrants careful interpretation. In the present study, we observed co-localization of CD38 with the myeloid marker CD11b, indicating that these cells are of myeloid origin. However, CD11b<sup>+</sup> cells in ocular tissues such as in conjunctiva are often described as monocyte-derived dendritic cells functioning as antigen-presenting cells, rather than as classical phagocytic macrophages [95,96]. Therefore, our data do not allow us to further resolve the specific myeloid subpopulation (e.g., macrophages, dendritic cells, or other subsets) responsible for CD38 expression. In addition, CD38 is known to be expressed across multiple immune cell types, including T cells, plasma cells, and NK cells [97-99], suggesting that non-myeloid immune cells may also contribute to the overall CD38 signal in the tarsal plate. While previous studies in other tissues, such as in adipose tissue and liver [39,40], have attributed age-associated CD38 upregulation primarily to macrophages, our findings highlight the need for more precise cell-type–resolved analyses in ocular tissues. Future studies using lineage-specific markers or single-cell approaches will be required to define the exact cellular sources of CD38 and their respective contributions to NAD metabolism and inflammation in the eyelid.” Added references:
(94) Khandelwal, P., Blanco-Mezquita, T., Emami, P., Lee, H.S., Reyes, N.J., Mathew, R., Huang, R., and Saban, D.R. (2013). Ocular mucosal CD11b+ and CD103+ mouse dendritic cells under normal conditions and in allergic immune responses. PLoS One 8, e64193. 10.1371/journal.pone.0064193.
(95) Ahadome, S.D., Mathew, R., Reyes, N.J., Mettu, P.S., Cousins, S.W., Calder, V.L., and Saban, D.R. (2016). Classical dendritic cells mediate fibrosis directly via the retinoic acid pathway in severe eye allergy. JCI Insight 1. 10.1172/jci.insight.87012.
(96) Malavasi, F., Deaglio, S., Funaro, A., Ferrero, E., Horenstein, A.L., Ortolan, E., Vaisitti, T., and Aydin, S. (2008). Evolution and function of the ADP ribosyl cyclase/CD38 gene family in physiology and pathology. Physiol Rev 88, 841-886. 10.1152/physrev.00035.2007.
(97) Katsuyama, E., Humbel, M., Suarez-Fueyo, A., Satyam, A., Yoshida, N., Kyttaris, V.C., Tsokos, M.G., and Tsokos, G.C. (2024). CD38 in SLE CD4 T cells promotes Ca2+ flux and suppresses interleukin-2 production by enhancing the expression of GM2 on the surface membrane. Nat Commun 15, 8304. 10.1038/s41467-024-52617-7.
(98) Peralta Ramos, J.M., Castellani, G., Kviatcovsky, D., Croese, T., Tsitsou-Kampeli, A., Burgaletto, C., Abellanas, M.A., Cahalon, L., Phoebeluc Colaiuta, S., Salame, T.M., et al. (2025). Targeting CD38 immunometabolic checkpoint improves metabolic fitness and cognition in a mouse model of Alzheimer's disease. Nat Commun 16, 3736. 10.1038/s41467-025-58494-y.
(g) LPS-induced inflammation is acute and severe and may not accurately model MGD, which is typically characterized by chronic, low-grade inflammation. It is suggested to use a more relevant model, such as benzalkonium chloride exposure or a desiccating stress chamber.
We thank the reviewer for this important suggestion. We agree that benzalkonium chloride exposure and desiccating stress are widely used and well-established models for ocular surface inflammation and dry eye [30-35], and we have also tested these approaches in our experimental system. However, while these treatments reproducibly induced inflammatory responses in the cornea, conjunctiva, and meibomian orifice, we did not observe detectable inflammatory changes within the tarsal plate (i.e., the internal eyelid tissue containing the meibomian glands). To our knowledge, induction of inflammation in the tarsal plate by these approaches has not been reported in the literature. As such, in our current study, we adopted subcutaneous LPS injection into the eyelid. However, as noted by the reviewer, this approach represents an acute and relatively strong inflammatory stimulus and does not fully recapitulate the chronic low-grade inflammation characteristic of MGD. Please note that, by describing both the rationale and limitations of this approach, we have improved our manuscript as follows:
“Eye-drop instillation of inflammatory stimuli such as those by lipopolysaccharide (LPS) or benzalkonium chloride has been shown to be effective to cause inflammation in the cornea and conjunctiva [30-35]. However, we found this approach ineffective to induce inflammation in the tarsal plate (inside the eyelid tissue). Therefore, we performed subcutaneous injection of LPS to the eyelids (see Methods).”
Methods [Page 30, lines 694-701] “LPS (Sigma) was reconstituted in saline and injected subcutaneously (5 µg/eyelid) 8 h before tissue collection for qRT-PCR analysis. LPS was administered every other day for a total of three or six doses before the measurement of meibomian NAD⁺ concentration or meibomian 3β-HSD enzymatic activity, respectively. Subcutaneous microinjection was performed using an insulin syringe (Becton Dickinson, 30G). This LPS-based approach represents an acute inflammatory stimulus and does not fully recapitulate the chronic low-grade inflammation characteristic of MGD — while it provides a practical means to induce inflammation in the tarsal plate.” Added references:
(30) Lin, Z., Liu, X., Zhou, T., Wang, Y., Bai, L., He, H., and Liu, Z. (2011). A mouse dry eye model induced by topical administration of benzalkonium chloride. Mol Vis 17, 257-264.
(31) Lin, Z., He, H., Zhou, T., Liu, X., Wang, Y., Wu, H., and Liu, Z. (2013). A mouse model of limbal stem cell deficiency induced by topical medication with the preservative benzalkonium chloride. Invest Ophthalmol Vis Sci 54, 6314-6325. 10.1167/iovs.12-10725.
(32) Wu, M., Downie, L.E., Hill, L.J., and Chinnery, H.R. (2023). Topical Decorin Reduces Corneal Inflammation and Imparts Neuroprotection in a Mouse Model of Benzalkonium Chloride-induced Corneal Neuropathy. Invest Ophthalmol Vis Sci 64, 20. 10.1167/iovs.64.2.20.
(33) Wu, C.Y., Wu, M., Huang, X., Gu, B.J., Maldonado-Codina, C., Morgan, P.B., Downie, L.E., and Chinnery, H.R. (2022). Topographical Distribution and Phenotype of Resident Meibomian Gland Orifice Immune Cells (MOICs) in Mice and the Effects of Topical Benzalkonium Chloride (BAK). Int J Mol Sci 23. 10.3390/ijms23179589.
(34) Simmons, K.T., Xiao, Y., Pflugfelder, S.C., and de Paiva, C.S. (2016). Inflammatory Response to Lipopolysaccharide on the Ocular Surface in a Murine Dry Eye Model. Invest Ophthalmol Vis Sci 57, 2443-2451. 10.1167/iovs.15-18396.
(35) Corrales, R.M., Villarreal, A., Farley, W., Stern, M.E., Li, D.Q., and Pflugfelder, S.C. (2007). Strain-related cytokine profiles on the murine ocular surface in response to desiccating stress. Cornea 26, 579-584. 10.1097/ICO.0b013e318033a729.
Влияние жёсткости и длины боковых стоек
Раздел объединить с предыдущим
Точность и быстродействие гибридной модели
Название главы "Оценка точности и быстродействия гибридной модели". Теперь на той же сетке параметров что и в предыдущем разделе (жесткость 20,200, 2000; длина 0.25, 0.5, 1.0) мы пытаемся аппроксимировать невязку ядра и точной кинематики и сравниваем с точностью модели, в которой сразу аппроксимируем кинематику полиномами (таблица 3). Далее объяснить что максимальная погрешность достигается в углах, и показать результаты на траектории.
Параметры эксперимента и влияние жёсткости стоек
Перепиши раздел "4.1 Параметры эксперимента и влияние жёсткости стоек". Во первых, он должен называться "оценка погрешности аналитического ядра" т.е. внутри все про ошибку, которую дают FK_ideal и IK_ideal, а так же про "паразитное смещение" выходного звена вдоль оси X. Далее, мы считаем только в рабочем поле и не выходим за его пределы. Объясни, что расчёт ведется при помощи IK_flexia, который основан на ньютоновских итерациях вокруг FK_Flexia(который сам по себе итерационный) и далее обсуждения об итерациях и времени будут более осмыслены. Расчет мы ведем на разных жесткостях (20, 200, 2000) и длинах (0.25, 0.5, 1.0). Тут не должно быть НИЧЕГО про аппроксимацию полиномами.
22 years-old man
Case#: 22-year-old man
DiseaseAssertion: NCCM and mildly reduced LV function
FamilyInfo: Mother and brothers have also been diagnosed with NCCM
ParentalTesting: Mother had cardio magnetic resonance imaging done
CasePresentingHPOs: not reported
CaseHPOFreeText:
CaseNotHPOs: HP:0001681, HP:0001279 Angina pectoris andSyncope
CaseNotHPOFreeText: no arrhythmic events
CasePreviousTesting: electrocardiogram, transthoracic echocardiography, cardiac-magnetic resonance imaging
Genotyping Method: next generation sequencing
FunctionalAnalysis: not reported
Variant: NM_001018005.1:c.20_22del; p.Lys7del
ClinVar:181682
CAID:CA018708
gnomAD:15-63042841-CAAG-C
AdditionalInfo:
Infantile restrictive cardiomyopathy: cTnI-R170G/W impair the interplay of sarcomeric proteins and the integrity of thin filaments
PMID: 32176697
Gene: TNNI3
HGNC ID: 11947
Patients 2 and 3, monozygotic twins
Case2: Sex not stated, age 8 months at diagnosis, ethnicity not stated
DiseaseAssertion: Restrictive cardiomyopathy (RCM)
FamilyInfo: Patients 2 and 3, monozygotic twins, were diagnosed with RCM at the age of 8 and 13 months, respectively. No familial history of cardiac disorders was reported in the R170W case, parental testing confirmed that the R170W variant occurred de novo (however, no parental proof was performed)
ParentalTesting: Parental testing confirmed that the R170W variant occurred de novo (however, no parental proof was performed). Parents do not carry the variant
CasePresentingHPOs: HP:0001723, HP:0002875, HP:0005110
CaseHPOFreeText: Echocardiographic examination revealed a restrictive filling pattern and enlarged atria. Both children died at the age of 12 and 18 months, respectively, due to congestive heart failure and atrial fibrillation
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: Total genomic DNA was extracted from peripheral blood using FlexiGene DNA Kit (Qiagen) according to the manufacturer’s protocol. The TNNI3 gene was screened for mutations using dye terminator sequencing. In both cases additional target sequencing including a panel of 108 cardiomyopathy- and channelopathy-associated genes was performed using Illumina MiSeq as previously described
FunctionalAnalysis: Functional analysis performed on recombinant proteins. Both cTnI-R170G/W strongly enhanced the Ca2+-sensitivity of skinned fibres, as is typical for RCM-mutations. Both mutants strongly enhanced the affinity of troponin (cTn) to tropomyosin compared to wildtype cTn. The stability of reconstituted thin filaments was reduced as revealed by electron microscopy.
Variant: NM_000363.5:c.508C>T (p.Arg170Trp)
ClinVar: 179285
CAID: CA021778
gnomAD: chr19-55154071-G-A
AdditionalInfo: Monozygotic twin
Patient 1
Case1: Male, age 3 at diagnosis, ethnicity not stated
DiseaseAssertion: Restrictive cardiomyopathy (RCM)
FamilyInfo: Familial screening in the R170G proband documented a hypertrophic cardiomyopathy with restrictive filling pattern in patient’s father, but the family refused additional genetic testing. No other family history of cardiac disorders stated.
ParentalTesting: The family refused additional genetic testing
CasePresentingHPOs: HP:0001723, HP:0001650, HP:0001654
CaseHPOFreeText: Patient 1 showed an impaired left ventricular function and pulmonary hypertension at three years of age. Heart biopsy showed mild cardiomyocyte hypertrophy and interstitial fibrosis. He was diagnosed with RCM and died one year later of ventricular fibrillation.
CaseNotHPOs: NR
CaseNotHPOFreeText: Target sequencing including a panel of 108 cardiomyopathy- and channelopathy-associated genes revealed no additional pathogenic or likely pathogenic variants
CasePreviousTesting: Additional target sequencing including a panel of 108 cardiomyopathy- and channelopathy-associated genes was performed using Illumina MiSeq as previously described.
Genotyping Method: Total genomic DNA was extracted from peripheral blood using FlexiGene DNA Kit (Qiagen) according to the manufacturer’s protocol. The TNNI3 gene was screened for mutations using dye terminator sequencing. In both cases additional target sequencing including a panel of 108 cardiomyopathy- and channelopathy-associated genes was performed using Illumina MiSeq as previously described
FunctionalAnalysis: Functional analysis performed on recombinant proteins. Both cTnI-R170G/W strongly enhanced the Ca2+-sensitivity of skinned fibres, as is typical for RCM-mutations. Both mutants strongly enhanced the affinity of troponin (cTn) to tropomyosin compared to wildtype cTn. The stability of reconstituted thin filaments was reduced as revealed by electron microscopy.
Variant: NM_000363.5:c.508C>G (p.Arg170Gly)
ClinVar: 165517
CAID: CA021769
gnomAD: NR
AdditionalInfo: NR
44-year-old (y.o.) male proband
Case#: male; age 44
DiseaseAssertion: Hypertrophic, restrictive, and dilated cardiomyopathy
FamilyInfo: The patient’s unaffected 6-year-old daughter was tested for the variant. His brother and parents were healthy
ParentalTesting: Parents refused genetic testing
CasePresentingHPOs: HP:0001639 HP:0001723 HP:0001644
CaseHPOFreeText: Hypertrophic cardiomyopathy; restrictive left-ventricular filling pattern; diastolic dysfunction
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: 25-gene Ion AmpliSeq panel with Ion PGM semiconductor sequencing; Sanger sequencing
FunctionalAnalysis: NR
Variant: TPM1 c.292G>A (p.Glu98Lys; p.E98K; rs730881131); missense variant; heterozygous
ClinVar: 1472862
CAID: CA392720843
gnomAD: NR
Novel Mutation Glu98Lys in Cardiac Tropomyosin Alters Its Structure and Impairs Myocardial Relaxation
PMID: 37569730
Gene: TPM1
HGNC ID: 12010
Double missense mutations in cardiac myosin‐binding protein C and myopalladin genes: A case report with diffuse coronary disease, complete atrioventricular block, and progression to dilated cardiomyopathy
PMID: 31524317
Gene: MYBPC3, MYPN
HGNC ID: 7551, 23246
50‐year‐old woman
Case1: 50‐year‐old woman
DiseaseAssertion: Ankles swelling and shortness of breath.
FamilyInfo: NR
ParentalTesting: NR
CasePresentingHPOs:
CaseHPOFreeText: dilated cardiomyopathy with end‐diastolic diameter of the left ventricle (LV) of 62 mm, severely depressed left ventricle ejection fraction (LVEF), 20%, mild hypertrophic septum (13.5 mm), trabecular aspect of lateral and inferior LV wall, thrombus in the apex, and severe tricuspid regurgitation with inferior vena cava reflow
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: next‐generation sequencing
FunctionalAnalysis: NR
Variant: NM_000256.3(MYBPC3):c.2459G>A (p.Arg820Gln), NM_032578.4(MYPN):c.3335C>T (p.Pro1112Leu)
ClinVar: 8617, 31791
CAID: CA012326, CA143763
gnomAD: 11-47359085-C-T, 10-69959174-C-T
AdditionalInfo: NR
Additional value of screening for minor genes and copy number variants in hypertrophic cardiomyopathy
PMID: 28771489
Gene: MYH7, TPM1
HGNC ID: HGNC:7577, HGNC:12010
29-year-old female who died of SCD
Case#: 29 year old female; diagnosed with DCM 8 years before death; died suddenly at home on 22 February 2017; forensic autopsy case
DiseaseAssertion: Dilated cardiomyopathy (DCM) with sudden cardiac death; MYBPC3-related
FamilyInfo: Family from Central-South China with a history of SCD. Father (I:1) reportedly died of a heart attack at 37, not genetically tested. Mother (I:2) and sister (II:2) are unaffected and do not carry the variant. No other affected relatives reported.
ParentalTesting: Not performed, both parents were not genotyped for the variant; the father was deceased before the study. Maternal non-carriage confirmed by Sanger, so the variant is either paternal or de novo; phase not established.
CasePresentingHPOs: HP:0001644; HP:0001645
CaseHPOFreeText: Diagnosed with DCM 8 years before death, with no other abnormalities. Found unresponsive at home at noon and expired; no prodromal symptoms documented. Autopsy: enlarged heart with valve thickening, myocardial fibrosis, and multi-organ congestion; no other fatal injury or disease. HE staining of left ventricle showed no hypertrophy or other anomalies. Toxicological screening for ethanol, benzodiazepines, barbiturates, amphetamine, methamphetamine, ketamine, morphine, MDMA, and THC-acid was negative; serum IgE normal (27 IU/ml); eosinophils 4.7% with no mast-cell degranulation.
CaseNotHPOs: HP:0001639; HP:0001634; HP:0003124
CaseNotHPOFreeText: No cardiomyocyte hypertrophy on histology, distinguishing this from HCM. No coronary, valvular, or congenital structural disease identified. No toxicological cause of death.
CasePreviousTesting: Whole-exome sequencing on postmortem blood, retaining synonymous variants; filtering against gnomAD and CMDB; in silico prediction with MutationTaster, PolyPhen-2, and SIFT; NetGene2-2.42 used to predict splice effects. Five variants in cardiomyopathy-related genes were found; only the MYBPC3 variant was classified likely pathogenic.
Genotyping Method: WES with Sanger confirmation on ABI 3100; family members genotyped by Sanger.
FunctionalAnalysis: Minigene assay pcDNA3.1-MYBPC3 construct spanning exon 1-intron 1-exon 2, transfected into HEK293 cells: wild-type and the c.10G>A negative control both produced a ~1,500 bp full-length band and a ~300 bp spliceosome band; the c.24A>C construct produced no spliceosome band, indicating abnormal splicing with intron 1 retention and frameshift. Immunohistochemistry showed decreased MYBPC3 protein in the proband's left ventricle versus a control heart.
Variant: MYBPC3 NM_000256.3:c.24A>C (p.Pro8Pro); heterozygous synonymous variant at the penultimate base of exon 1; disrupts the splice donor site; novel
ClinVar: 164098
CAID: CA11138
gnomAD: 0.00001541
AdditionalInfo: Classified likely pathogenic with PS3, PM2, PP1, PP3; note the paper's Discussion relabels the prediction code as PP4, an internal inconsistency. The authors describe it as the first reported deleterious synonymous MYBPC3 variant, acting by intron retention and reduced protein. The same splice site is affected by the known HCM variants c.24+1G>A and c.24+3A>C. Four other variants were found and classified likely benign or VUS: LDB3 c.2131T>C (VUS), BBS2 c.422A>G, EVC2 c.2643G>C, and BBS4 c.1548_1549del.
Extended genotype–phenotype spectrum of 17α-hydroxylase/17,20-lyase deficiency: a nine-case series featuring a novel mutation, suspected TART-like lesions, and multisystem involvement
PMID: : 42824042
Gene: MYBPC3
HGNC ID: :7551
Genetic predisposition in chemotherapy‐induced cardiomyopathy in a 65‐year‐old female with metastatic breast cancer
PMID: 38616291
Gene: TNNT2
HGNC ID: 11949
A 65‐year‐old woman
Case#: female; age 65
DiseaseAssertion: chemotherapy-induced cardiomyopathy with severe left ventricular systolic dysfunction
FamilyInfo: NR
ParentalTesting: NR
CasePresentingHPOs: HP:0001644 HP:0001635 HP:0001640
CaseHPOFreeText: Dilated left ventricle; left ventricular dysfunction; cardiomegaly; bilateral pleural effusion; dyspnea
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: Previous anthracycline-associated cardiomyopathy 7 years earlier
Genotyping Method: TruSight One Expanded 6700-gene sequencing panel on an Illumina NextSeq 550
FunctionalAnalysis: NR
Variant: c.452G>A (p.Arg151Gln; rs730881101); missense variant; heterozygous
ClinVar: 181617
CAID: NR
gnomAD: NR
EO1 yes MYBPC3 5 c.553A>T Lys185Ter
Case#: E01
DiseaseAssertion: Early onset Hypertrophic Cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Early-onset hypertrophic cardiomyopathy
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Generation Sequencing
FunctionalAnalysis: Not reported
Variant: MYBPC3 c.553A>T (p.Lys185Ter)
ClinVar: 574262
CAID: Not found
gnomAD: 11-47349875-T-G
AdditionalInfo: Clinical significance: known/pathogenic. Allele coverage 202.
EO27 yes TNNT2 14 c.794A>T Lys265Ile MISSENSE
Case#: E027
DiseaseAssertion: Early onset hypertrophic cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Not reported
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Generation Sequencing
FunctionalAnalysis: Not reported
Variant: c.794A>T (Lys265Ile)
ClinVar: Not found
CAID: CA005099
gnomAD: Not found
AdditionalInfo: Clinical significance: known/uncertain significance. Allele coverage: 193.
EO30 yes TNNI3 6 c.431T>A Leu144Gln MISSENSE
Case#: E030
DiseaseAssertion: Early onset hypertrophic cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Not reported
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Generation Sequencing
FunctionalAnalysis: Not reported
Variant: c.431T>A (Leu144Gln)
ClinVar: Not found
CAID: Not found
gnomAD: Not found
AdditionalInfo: Clinical Significance: Known/pahtogenic. Allele coverage: 227.
A Next-Generation Sequencing Approach to Identify Gene Mutations in Early- and Late-Onset Hypertrophic Cardiomyopathy Patients of an Italian Cohort
PMID: 27483260
Gene: TNN13 MYBPC3 TNNT2
HGNC ID: 11947 7551 11949
EO4 MYBPC3 23 c.2309-2A>G SPLICING
Case#: E04
DiseaseAssertion: Early onset hypertrophic cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Not reported
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Gen Sequencing
FunctionalAnalysis: Not reported
Variant: c.2309-2A>G
ClinVar: Not found
CAID: Not found
gnomAD: 11-47337796-T-C
AdditionalInfo: known pathogenic. allele coverage: 186.
EO34 yes TNNT2 9 c.281G>C Arg94Thr MISSENSE
Case#: E034
DiseaseAssertion: Early onset hypertrophic cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Not reported
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Generation Sequencing
FunctionalAnalysis: Not reported
Variant: c.281G>C (Arg94Thr)
ClinVar: Not found
CAID: CA004216
gnomAD: Not found
AdditionalInfo: Clinical Significance: Known/uncertain significance. Allele coverage 196
LO8 Yes MYBPC3 16 c.1624G>C Glu542Gln MISSENSE/SPLICING known/pathogenic rs121909374 yes 353 188 TNNI3 6 c.385C>G Thr128Ser MISSENSE new/likely benign 400 204
Case#: L08
DiseaseAssertion: Late onset hypertrophic cardiomyopathy
FamilyInfo: Familiarity case reported as "yes"
ParentalTesting: Not reported
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Not reported
CaseNotHPOs: Not reported
CaseNotHPOFreeText: Not reported
CasePreviousTesting: Not reported
Genotyping Method: Next Generation Sequencing
FunctionalAnalysis: Not reported
Variant: c.1624G>C (Glu542Gln), heterozygous, pathogenic. c.385C>G (Thr128Ser) heterozygous, likely benign.
ClinVar: Not found
CAID: CA407440771 (MYBPC3 CAID not found)
gnomAD: Not found
AdditionalInfo: L08 has two variants. MYBPC3 variant missense/splicing, known pathogenic; Allele coverage 188. TNNI3 variant Missense, new/likely benign; Allele coverage 400.
The TPM1 D230N variant was present in all affected individuals in Families A
Case1: Caucasian. Sex and exact age not specified for the proband
DiseaseAssertion: Dilated cardiomyopathy (DCM)
FamilyInfo: Family A was notable for severe HF and sudden death in young children. Individuals I-2, III-10 and IV-7 died suddenly at ages 3 years, 13 months, and 5 months respectively, without prior evidence of heart disease. Two siblings, IV-5 and IV-8, presented with DCM and advanced HF at 5 months of age (LVEF 27% and 29%). Individuals III-3 and IV-1 developed end-stage HF refractory to medical therapy as teenagers. III-3 presented at age 13 with refractory HF, underwent mitral and tricuspid valve replacement for functional regurgitation and died weeks later of multisystem organ failure. IV-1 was asymptomatic when diagnosed with DCM at 7 years during family screening, but developed severe HF at age 17 and underwent transplant at 18 years of age. Individuals III-4, III-7 and III-12 developed mild exercise intolerance in their 5th decade.
ParentalTesting: NR
CasePresentingHPOs: HP:0001635, HP:0001644
CaseHPOFreeText: No family members with TPM1 D230N had evidence of cardiac conduction disease, and with one exception, none had evidence of skeletal myopathy
CaseNotHPOs: NR
CaseNotHPOFreeText: No family members with TPM1 D230N had evidence of cardiac conduction disease, and with one exception, none had evidence of skeletal myopathy.
CasePreviousTesting: No prior testing.
Genotyping Method: Genomic DNA was isolated from blood using standard methods in probands with DCM. Direct DNA sequence analysis of all coding regions and intron/exon boundaries was performed in 6 sarcomere genes.
FunctionalAnalysis: Functional analysis performed on recombinant proteins but not patient tissue. In vitro studies demonstrated major inhibitory effects on sarcomere function with reduced Ca2+-sensitivity, maximum activation, and Ca2+ affinity compared to wildtype TPM1.
Variant: NM_000366.5:c.688G>A (p.Asp230Asn)
ClinVar: NR
CAID: UnregisteredVariant
gnomAD: NR
AdditionalInfo: The paper does not explicitly identify which pedigree member is the Family A proband
Familial Dilated Cardiomyopathy caused by an Alpha-Tropomyosin Mutation: The Distinctive Natural History of Sarcomeric DCM
PMID: 20117444
Gene: TPM1
HGNC ID: 12010
The TPM1 D230N variant was present in all affected individuals in Families A and B
Case2: Caucasian. Sex and exact age not specified for the proband
DiseaseAssertion: Dilated cardiomyopathy (DCM)
FamilyInfo: Young members of this family also presented with severe HF. Individual III-1 developed failure to thrive at 10 weeks of age and echocardiography revealed severe LV dilation (LVIDD Z-score 15.6) and systolic dysfunction (LVEF 15%). Transplantation was considered, but she had substantial recovery with basic medical therapy. By age 8 years, she was asymptomatic with only mild LV systolic dysfunction (LVIDD Z-score 1.3, LVEF 46%). At age 20, II-6 underwent cardiac transplantation shortly after presenting with refractory HF symptoms and severe LV systolic dysfunction (LVEF < 20%). Individual II-7 died of HF at 12 years, prior to genetic testing. In addition to DCM, he had congenital cataracts and skeletal muscle weakness. I-1 had unexplained syncope at age 56 years. Cardiac studies revealed ventricular tachycardia and DCM (LVEF 25%) which improved with medical management. Three other adults (II-2, II-3, II-4, ages 38, 36 and 33 years, respectively) had asymptomatic LV systolic dysfunction.
ParentalTesting: NR
CasePresentingHPOs: HP:0001635, HP:0001644
CaseHPOFreeText: NR
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: No prior testing.
Genotyping Method: Genomic DNA was isolated from blood using standard methods in probands with DCM. Direct DNA sequence analysis of all coding regions and intron/exon boundaries was performed in 6 sarcomere genes.
FunctionalAnalysis: Functional analysis performed on recombinant proteins but not patient tissue. In vitro studies demonstrated major inhibitory effects on sarcomere function with reduced Ca2+-sensitivity, maximum activation, and Ca2+ affinity compared to wildtype TPM1.
Variant: NM_000366.5:c.688G>A (p.Asp230Asn)
ClinVar: NR
CAID: UnregisteredVariant
gnomAD: NR
AdditionalInfo: The paper does not explicitly identify which pedigree member is the Family B proband
1
Case#: Patient 1; 89-year-old female; identical twin (Patient 2) with mild HCM
DiseaseAssertion: Hypertrophic cardiomyopathy (HCM) associated with the pathogenic MYBPC3 nonsense variant NM_000256.3.787G>T (p.Gly263Ter). Patient 1 is an 89-year-old female with severe symptomatic obstructive HCM, previously requiring septal ablation. Her maximum reported left ventricular wall thickness was 29 mm by echocardiography in 2015.
FamilyInfo: Patient 1 belongs to a family with hereditary hypertrophic cardiomyopathy associated with the MYBPC3 p.Gly263Ter founder variant. Her monozygotic twin sister (Patient 2) carries the same pathogenic variant but has a substantially milder HCM phenotype, with a maximum left ventricular wall thickness of 13 mm and no reported symptoms at an advanced age. The twin pair belongs to the extended family that also includes Patients 3 and 4, another pair of monozygotic twins carrying the same variant. The pedigree documents additional affected relatives and a history of sudden death, although not all family members have confirmed genetic testing.
ParentalTesting: NR – The family pedigree supports familial occurrence of hypertrophic cardiomyopathy, but the specific parent from whom Patient 1 inherited the MYBPC3 p.Gly263Ter variant cannot be conclusively determined from the available genetic testing data. Her monozygotic twin sister (Patient 2) was confirmed to carry the same variant.
CasePresentingHPOs: HP:0001639 (Hypertrophic cardiomyopathy); HP:0002094 (Dyspnea); HP:0001712 (Left ventricular hypertrophy); HP:0032092 (Left ventricular outflow tract obstruction)
CaseHPOFreeText: Echocardiography documented a maximum left ventricular wall thickness of 29 mm in 2015. She previously experienced significant dyspnea, with symptoms classified as NYHA III/IV, associated with severe left ventricular outflow tract obstruction. She underwent septal ablation, which improved her clinical symptoms. At the time of the study, she remained minimally symptomatic.
CaseNotHPOs: HP:0000822 (Hypertension)
CaseNotHPOFreeText: Explicitly reported that Patient 1 did not have hypertension. No additional negative phenotypic findings were specifically documented for this patient.
CasePreviousTesting: Previous cardiac evaluations included echocardiography demonstrating severe left ventricular hypertrophy, with a maximum wall thickness of 29 mm in 2015, and clinical identification of severe left ventricular outflow tract obstruction. The patient underwent septal ablation for symptomatic obstructive hypertrophic cardiomyopathy. Electrocardiographic findings were also evaluated following the procedure. The article does not provide a detailed history of genetic testing performed before the reported familial MYBPC3 investigation.
Genotyping Method: Genetic testing of index cases was performed using targeted next-generation sequencing (NGS) with Ion Torrent technology. The earlier index cases were evaluated using a nine-gene sarcomeric panel, including MYBPC3. Familial screening for the MYBPC3 NM_000256.3.787G>T (p.Gly263Ter) variant was performed using Sanger sequencing on an ABI3130XL sequencer. Monozygosity of the twin pairs was independently confirmed using the PowerPlex 16 HS System, which analyzes 16 microsatellite markers. Article does not specify whether Patient 1's individual MYBPC3 genotype was initially established through NGS or other targeted Sanger sequencing.
FunctionalAnalysis: The MYBPC3 NM_000256.3.787G>T (p.Gly263Ter) variant is a nonsense mutation that introduces a premature termination codon. The authors classified this founder variant as pathogenic based on its predicted loss-of-function effect, absence from the population reference databases examined, and segregation among affected family members. Computational evidence supported a deleterious effect. However, no patient-specific functional assays measuring MYBPC3 RNA expression, protein abundance, or protein function were reported in this study. The molecular consequences were inferred from the variant type and existing evidence rather than directly demonstrated experimentally in Patient 1.
Variant: MYBPC3 NM_000256.3:c.787G>T p.Gly263Ter; Nonsense; Autosomal dominant; Clinical significance: Pathogenic (1 submission). Review status: 1 out of 4 stars (criteria provided, single submitter).
ClinVar: 1460339
CAID: CA380333920
gnomAD: GRCh38 variant 11-47347891-C-A. African/African American population: AC = 0; AF = 0.0000.
AdditionalInfo: Patient’s monozygotic twin sister (Patient 2) carries the same variant but exhibits a substantially milder clinical phenotype. Patient 1 had a maximum left ventricular wall thickness of 29 mm in 2015, severe left ventricular outflow tract obstruction, and symptomatic dyspnea requiring septal ablation. In contrast, Patient 2 had a maximum wall thickness of 13 mm and was asymptomatic. This illustrates variable expressivity of MYBPC3-associated hypertrophic cardiomyopathy, even among genetically identical individuals. The authors discuss environmental and epigenetic factors as possible contributors to phenotypic variability, although no specific modifying mechanism was experimentally demonstrated in these patients.
5
Case#: Patient 5; 47-year-old male; identical twin (Patient 6) with less severe hypertrophy
DiseaseAssertion: Hypertrophic cardiomyopathy (HCM)
FamilyInfo: Patient has a monozygotic twin brother (Patient 6), who is also affected by HCM. Both individuals carry the same pathogenic MYBPC3 nonsense variant, NM_000256.3.787G>T (p.Gly263Ter). However, Patient 5 demonstrates more pronounced left ventricular hypertrophy than Patient 6. Cardiac magnetic resonance imaging (CMR) revealed maximum left ventricular wall thicknesses of 28 mm and 19 mm, respectively.
ParentalTesting: NR – Parental genetic testing results were not explicitly reported for Patient 5 or his monozygotic twin brother (Patient 6)
CasePresentingHPOs: HP:0001639 (Hypertrophic cardiomyopathy); HP:0001712 (Left ventricular hypertrophy)
CaseHPOFreeText: Patient diagnosed with hypertrophic cardiomyopathy (HCM), characterized by substantial left ventricular hypertrophy. Echocardiography performed in 2022 demonstrated a maximum left ventricular wall thickness of 18 mm, while cardiac magnetic resonance imaging (CMR) showed a maximum thickness of 28 mm.
CaseNotHPOs: HP:0032092 (Left ventricular outflow tract obstruction); HP:0000822 (Hypertension)
CaseNotHPOFreeText: Patient 5 did not exhibit left ventricular outflow tract obstruction (LVOTO), even though having substantial left ventricular hypertrophy (max wall thickness of 28 mm). The study also explicitly reports that none of the six patients, including Patient 5, had hypertension.
CasePreviousTesting: Patient 5 underwent clinical cardiac evaluation, including echocardiography, cardiac magnetic resonance imaging (CMR), and electrocardiography (ECG).
Genotyping Method: Genetic analysis was performed using next-generation sequencing (NGS) with Ion Torrent technology for index patients and targeted Sanger sequencing for familial screening. The study reports that recent index cases associated with Patients 5–6 were evaluated using an expanded 195-gene NGS panel, as described in Supplementary Table S2. The pathogenic MYBPC3 variant NM_000256.3.787G>T (p.Gly263Ter) was identified in both monozygotic twins. However, the article does not explicitly specify whether Patient 5 underwent the full NGS panel or targeted familial testing. Monozygosity was independently confirmed using the PowerPlex 16 HS System.
FunctionalAnalysis: NR – No patient-specific functional assays were reported for Patient 5 (computational evidence supporting a deleterious effect, absence from the ESP, 1000 Genomes, and ExAC population databases, and segregation of the variant among affected family members).
Variant: MYBPC3 NM_000256.3:c.787G>T p.Gly263Ter; Premature termination codon; Nonsense; Autosomal dominant; Clinical significance: Pathogenic (1 submission). Review status: 1 out of 4 stars (criteria provided, single submitter).
ClinVar: 1460339
CAID: CA380333920
gnomAD: gnomAD: GRCh38 variant 11-47347891-C-A. African/African American population: AC = 0; AF = 0.0000.
AdditionalInfo: Patient’s monozygotic twin brother (Patient 6) carries the same pathogenic variant but exhibits less pronounced left ventricular hypertrophy. The authors suggest that additional environmental or epigenetic modifiers may influence disease severity, although no specific modifying mechanism was experimentally established.
63-year-old male
Case1: 63-year-old male
DiseaseAssertion: Atrial flutter(54), VT & ICD(57); CVA(58) & DCM(58); HF(59)
FamilyInfo: There are 14 affected family members (Fig 1): six living (three sisters III-1, III-4, III-6 and three nieces IV-5, IV-15, IV-16) and eight deceased individuals (I-3, II-8, II-13, III-8, III-10, IV-1, IV-4, IV-6).
ParentalTesting:
CasePresentingHPOs:
CaseHPOFreeText: atrial flutter during evaluation for non-cardiac surgery. Subsequent evaluations led to the diagnosis of SSS. At 54 years old, echocardiogram showed mild systolic dysfunction and left ventricle dilation (EF 45%, LVEDD 58 mm). Myocardial perfusion study showed exercise intolerance but no signs of ischemia. At presentation, he felt well noting mild exercise intolerance for the past year with no palpitations or chest pain; he took no medications. At age 49, he had normal systolic function and LV dilation by echocardiogram (EF 53%, LVEDD 61 mm) and a normal myocardial perfusion study.
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: Sanger sequencing
FunctionalAnalysis: NR
Variant: NM_170707.4(LMNA):c.357-2A>G
ClinVar: 652066
CAID: CA342814936
gnomAD: NR
AdditionalInfo:
Exome Sequencing Identifies a Novel LMNA Splice-Site Mutation and Multigenic Heterozygosity of Potential Modifiers in a Family with Sick Sinus Syndrome, Dilated Cardiomyopathy, and Sudden Cardiac Death
PMID: 27182706
Gene: LMNA
HGNC ID: 6636
A de novo heterozygous ACTC1 variant (NM_005159.5; c.650A>C, p.Lys217Thr) was found in Individual 2.
Case:Male, born at 39 weeks of gestation, evaluated during infancy-age 6.
DiseaseAssertion:Arthrogryposis multiplex congenita (AMC). The patient also had Shone's complex with coarctation of the aorta. Cardiomyopathy not reported.
Familyinfo:The patient was the first child of unrelated parents. No family history of arthrogryposis multiplex congenita was reported.
ParentalTesting:The ACTC1 c.650A>C (p.Lys217Thr) variant was identified as de novo. Neither parent was reported to carry the variant.
CasePresentingHPOs:HP:0002804, HP:0001762, HP:0001680, HP:0001188, HP:0000954, HP:0001845, HP:0001290, HP:0002194
CaseHPOFreeText:The patient was born at 39 weeks of gestation. At birth, he had limited range of motion in the wrists, fingers, thumbs, hips, and knees, along with bilateral clubfeet. Echocardiography revealed Shone's complex, including coarctation of the aorta, which required surgical repair. At age 1, he had clenched hands with deep single palmar creases, overlapping toes, and hypoplastic fifth toenails. He also had truncal hypotonia, mild lower extremity weakness, and delayed gross motor milestones. At age 3, moderate wrist contractures, thumb-in-palm deformities, and mild bilateral hip contractures were observed. He began walking independently at age 4. At age 5, he underwent additional heart surgery and pacemaker insertion.
CaseNotHPOs:Scoliosis: not identified on spine X-rays, cognitive difficulties: not reported
CaseNOTHPOFreeText:The patient did not have reported cognitive difficulties. Spine X-rays did not reveal scoliosis.
CasePreviousTesting:Genome sequencing was performed to identify genetic variants associated with the patient's clinical presentation. Echocardiography was used to identify Shone's complex and coarctation of the aorta.
GenotypingMethod:Genome sequencing. Plasmid sequences used for the functional experiments were verified by Sanger sequencing.
FunctionalAnalysis:In vitro functional studies were performed using MC3T3-E1 preosteoblastic cells. The p.Lys217Thr variant did not demonstrate a clear effect on ACTC1 protein expression or localization compared with wild-type ACTC1. The authors reported no apparent reduction in protein levels or impaired actin filament organization.
Variant:NM_005159.5 (ACTC1): c.650A>C; p.Lys217Thr.
ClinVar:not reported
CAID:not reported
gnomAD:not reported
AdditionalInfo:The variant was identified as de novo and classified as likely pathogenic using ACMG criteria (PS2, PM1, PM2, PP2, PP3). Although functional testing did not demonstrate a clear effect on ACTC1 protein expression or localization, the authors considered the variant likely pathogenic based on the genetic and clinical evidence.
Genome sequencing identified a heterozygous ACTC1 variant (NM_005159.5; c.325G>A, p.Glu109Lys) in Individual 1 and her mother. The variant was absent from gnomAD v2.1.1, had an AlphaMissense score of 0.99 and a REVEL score of 0.827. It was classified as likely pathogenic with ACMG criteria (PM1, PM2, PP1, PP2, PP3).
Case:Female, born at 34 weeks of gestation, 5 years old at the first detailed examination, 8 years old during a later clinical description.
DiseaseAssertion:Arthrogryposis multiplex congenita (AMC). Cardiomyopathy not reported.
Familyinfo:The patient was the first child of unrelated parents. Her mother and one maternal aunt were born with bilateral clubfeet and later developed scoliosis. The mother also had a history of cleft palate. Neither the mother nor the patient had a reported history of cardiac problems.
ParentalTesting:The patient's mother carried the same heterozygous ACTC1 c.325G>A (p.Glu109Lys) variant. The variant was therefore inherited from the mother.
CasePresentingHPOs:HP:0002804, HP:0001762, HP:0000175, HP:0000465, HP:0002650, HP:0004322, HP:0012385, HP:0001371
CaseHPOFreeText:The patient was born by cesarean section at 34 weeks of gestation. Bilateral clubfeet, cleft palate, neck webbing, and spinal deformity were noted. At age 5, she had severe scoliosis measuring 120 degrees and severe short stature. At age 8, mild camptodactyly of both hands and mild contractures of the neck, left hip, both knees, and feet were observed. She had no significant mobility or cognitive difficulties and was independent in self-care activities.
CaseNotHPOs:No reported cardiac problems, no significant cognitive difficulties, no significant mobility difficulties.
CaseNOTHPOFreeText:The patient had no reported cardiac phenotype despite carrying an ACTC1 variant. Her mother also had no history of cardiac problems.
CasePreviousTesting:Genome sequencing was performed to identify genetic variants associated with the patient's clinical presentation.
GenotypingMethod:Genome sequencing. Plasmid sequencing was also verified by Sanger sequencing for the experimental functional studies.
FunctionalAnalysis:In vitro functional studies were performed using MC3T3-E1 preosteoblastic cells. The p.Glu109Lys variant caused decreased ACTC1 protein levels and impaired actin filament assembly. Immunofluorescence and Western blotting were used to evaluate protein expression and actin filament organization.
Variant:NM_005159.5 (ACTC1): c.325G>A; p.Glu109Lys.
ClinVar:not reported
CAID:not reported
gnomAD:not found
AdditionalInfo:The variant was inherited from the patient's mother, who also had bilateral clubfeet, scoliosis, and a history of cleft palate. The authors classified the variant as likely pathogenic using ACMG criteria (PM1, PM2, PP1, PP2, PP3). The functional studies demonstrated reduced ACTC1 protein levels and impaired actin filament assembly.
proband II: 3 was a 43-year-old man
Case#: 43-year-old man family b
DiseaseAssertion: Familial dilated cardiomyopathy (FDCM)
FamilyInfo: Sister II:1 had previously been diagnosed with DCM and carried both reported variants. Brother II:2 died of sudden cardiac death.
ParentalTesting: father was negative for either varient
CasePresentingHPOs: HP:0031352, HP:0002094, HP:0002321 HP:0001644 “Dyspnea; chest tightness; dizziness; dilated cardiomyopathy
CaseHPOFreeText: Severe DCM symptoms
CaseNotHPOs: not reported
CaseNotHPOFreeText: Father I:1 and daughter III:1 were reported to have no clinical symptoms
CasePreviousTesting: Previously diagnosed with FDCM
Genotyping Method: NGS. PCR, Sanger
FunctionalAnalysis: Putative pathogenic mutations were analysed computationally using the PolyPhen-2, SIFT, and MutationTaster
Variant: MYH7 NM_000257:c.3134G>A; p.Arg1045His; heterozygous missense
ClinVar: 651054
CAID: N/A
gnomAD: 14-23422291-C-T
AdditionalInfo: two variants may have a “dose effect” and associate their combination with the proband’s severe phenotype
patient from Family A
Case#:44-year-old woman , family 1 proband
DiseaseAssertion: Familial hypertrophic cardiomyopathy
FamilyInfo: Father, sister, and brother, died of sudden cardiac death around age 40
ParentalTesting: not reported
CasePresentingHPOs: HP:0031352, HP:0002094, HP:0005144 “Dyspnea; chest tightness, increased interventricular septum thickness”
CaseHPOFreeText: Symptoms after exercise, interventricular septum thickness 14.8 mm; left atrium 32 mm.
CaseNotHPOs: not reported
CaseNotHPOFreeText:not reported
CasePreviousTesting: no previous testing was reported
Genotyping Method: NGS. PCR, Sanger
FunctionalAnalysis: Putative pathogenic mutations were analysed computationally using the PolyPhen-2, SIFT, and MutationTaster
Variant: TNNI3 NM_000363.4:c.433C>G; p.Arg145Gly heterozygous exon 7 missense
ClinVar:12419
CAID: N/A
gnomAD: 19-55154146-G-C
AdditionalInfo: reported variant and a potential HCM hotspot
Targeted Next-Generation Sequencing Reveals Hot Spots and Doubly Heterozygous Mutations in Chinese Patients with Familial Cardiomyopathy
PMID: 26199943
Gene: TNNI3
HGNC ID: HGNC:11947
a man aged 45 years
Case1: 45 year old man, Chinese Han descent
DiseaseAssertion: Symptoms of congestive heart failure for 10 years and then developed ascites
FamilyInfo: No obvious family history.
ParentalTesting: NR
CasePresentingHPOs: HP:0031295, HP:0030718, HP:0001639
CaseHPOFreeText: typical RCM phenotype with biatrial enlargement, normal LV volume and wall thickness, mildly depressed LV ejection fraction (52%), and significantly impaired LV diastolic function
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: high-throughput NGS
FunctionalAnalysis: NR
Variant: NM_000256.3(MYBPC3):c.1000G>A (p.Glu334Lys)
ClinVar: 177902
CAID: CA009667
gnomAD: 11-47367848-C-T
AdditionalInfo: NR
Novel Phenotype–Genotype Correlations of Restrictive Cardiomyopathy With Myosin-Binding Protein C (MYBPC3) Gene Mutations Tested by Next-Generation Sequencing
PMID: 26163040
Gene: MYBPC3
HGNC ID: 7551
Patient 1
Case1: 5 week old female
DiseaseAssertion: Feeding problems and cyanosis. X-thorax showed a grossly enlarged heart
FamilyInfo: Family history of both parents was positive for HCM and sudden death
ParentalTesting: Initial echocardiography revealed no abnormalities in the 32-year-old mother, who was heterozygous for c.2373dup, nor in the 31-year-old father, heterozygous for c.2827C>T. ECG in the father showed mild repolarization abnormalities (ST elevation of 0.5 mm in V1, followed by a negative T in V1–V4). Re-evaluation after 7 years revealed moderate septal hypertrophy (HCM) with an interventricular septum of 14 mm in the mother, and interventricular septal measurements at the upper limit of the normal range (12 mm) in the father.
CasePresentingHPOs: HP:0001640, HP:0001639,
CaseHPOFreeText: Severe cardiomegaly and dilatation with a total weight of 115 g (normal weight at this age, 30 g). Right ventricular thickening was noted, especially of the posterior wall. The anterior wall of the left ventricle was severely thickened and showed abnormal trabeculation and multiple intertrabecular recesses as seen in noncompaction cardiomyopathy. Secundum ASD was confirmed. No other congenital malformations were found. Microscopic examination of cardiac tissue (Figure 1a) showed myofibrillar disarray in both the ventricular septum and the left ventricular wall. Hypertrophic myocytes with a diameter of 20–30 μm (normal 12 μm) and multiple vacuoles on electron microscopy suggested glycogenosis
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: NR
FunctionalAnalysis: Microscopic postmortem examination of heart muscle from patient 1. Hypertrophic myocytes with myofibrillar disarray typical of HCM due to sarcomeric protein variations were present, albeit without a significant amount of interstitial fibrosis (hematoxylin and eosin staining, magnification × 100). (b) Electron micrograph showing a large, irregular vacuole.
Variant: NC_000011.10:g.47337730dup, NM_000256.3(MYBPC3):c.2827C>T (p.Arg943Ter)
ClinVar: 37039, 42619
CAID: CA013001, CA012139
gnomAD: 11-47356671-G-A, 11-47359280-A-AC
AdditionalInfo: NR
Patient 4
Case4: 6 week old female
DiseaseAssertion: dyspnea, hypotension, feeding difficulties, and failure to thrive
FamilyInfo: Her mother was diagnosed with postpartum HCM with diastolic dysfunction, confirmed by cardiac MRI, at age 26. Echocardiography of the father was normal; ECG showed a right bundle branch block. A paternal uncle of patient 4 had died aged 3 months of unknown cause
ParentalTesting: Both parents were heterozygous for c.2827C>T p.(Arg943*) nonsense mutation in MYBPC3
CasePresentingHPOs: HP:0001639
CaseHPOFreeText: Severe HCM with features of noncompaction, and severe diastolic and systolic left ventricular dysfunction (IVSd 11 mm, Z+10; LVPWd 10 mm, Z+10, FS 13% (LVID 17/20) and left ventricular mass 255 g/m2). A secundum ASD with a left–right shunt was also observed.
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: NR
FunctionalAnalysis: NR
Variant: NM_000256.3(MYBPC3):c.2827C>T (p.Arg943Ter)
ClinVar: 37039
CAID: CA013001
gnomAD: 11-47356671-G-A
AdditionalInfo: NR
Compound heterozygous or homozygous truncating MYBPC3 mutations cause lethal cardiomyopathy with features of noncompaction and septal defects
PMID: 25335496
Gene: MYBPC3
HGNC ID: 7551
The third proband
Case3: 7 week old female
DiseaseAssertion:
FamilyInfo: A cousin of the father presented with cardiac arrest due to HCM. He had a heterozygous pathogenic c.2373dup p.(Trp792fs) mutation in MYBPC3. We subsequently confirmed homozygosity for the c.2373dup variant in DNA isolated from stored fibroblasts from the deceased proband. Both parents of the proband were heterozygous for this truncating variant (Figure 2b). Cardiac re-evaluation showed only slightly reduced ECG voltages in the father (age 38) and borderline hypertrophy (septal thickness 11 mm) in the mother (age 41).
ParentalTesting:
CasePresentingHPOs: HP:0001640, HP:0002119
CaseHPOFreeText: Cardiomegaly was seen on chest X-ray, and echocardiography showed HCM with dilated ventricles. M-Mode measurements were unavailable. Noncompaction was not a clear feature, but could not be excluded. There was a small foramen ovale and mitral valve insufficiency
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: NR
FunctionalAnalysis: DNA isolated from stored fibroblasts from the deceased proband.
Variant: NC_000011.10:g.47337730dup
ClinVar: 42619
CAID: CA012139
gnomAD: 11-47359280-A-AC
AdditionalInfo: NR
Patient 2
Case2: 4 week old male
DiseaseAssertion: Feeding problems in the first weeks of life and dyspnea and mild hypotonia were noticed at age 4 weeks.
FamilyInfo: NR
ParentalTesting: NR
CasePresentingHPOs: HP:0001640
CaseHPOFreeText: A grossly enlarged heart was observed on the X-thorax (heart–thorax ratio 0.8%) and low oxygen saturation blood levels were found. Echocardiography revealed moderately dilated ventricles with severe diastolic and systolic dysfunction. Hypertrabeculation with flow perfused intertrabecular recesses was present in both ventricles, including the apical walls (Figure 3). An apical muscular ventricular septal defect (VSD) was visualized, although deep recessal flow complicated interpretation of the images
CaseNotHPOs: NR
CaseNotHPOFreeText: NR
CasePreviousTesting: NR
Genotyping Method: NR
FunctionalAnalysis: NR
Variant: NC_000011.10:g.47337730dup, NM_000256.3(MYBPC3):c.2827C>T (p.Arg943Ter)
ClinVar: 37039, 42619
CAID: CA013001, CA012139
gnomAD: 11-47356671-G-A, 11-47359280-A-AC
AdditionalInfo: NR
Clinical genetic testing in four highly suspected pediatric restrictive cardiomyopathy cases
PMID: 35614389
Gene: TNNI3
HGNC ID: 11947
A 4-year, 5-month-old girl had clinical symptoms
Case1: Female, four years five months
DiseaseAssertion: RCM
FamilyInfo: “ No family history of RCM or other cardiovascular diseases was reported.”
ParentalTesting: NA
CasePresentingHPOs:HP:0002094, HP:0002875,
CaseHPOFreeText: “congestive hepatomegaly” “lower extremity edema” “increased heart shadow without calcification of the pericardium” “bi-atrial enlargement without calcification of the pericardium, thickened pericardium, or endocardium” “‘eft and right atria were enlarged, the right ventricle was slightly enlarged”
CaseNotHPOs:
CaseNotHPOFreeText: “the left ventricle was normal in size, without calcification of the pericardium, thickened pericardium, or endocardium”
CasePreviousTesting: Chest X-ray, Abdominal ultrasonography, MRI, Two-dimensional echocardiography
Genotyping Method: Sanger Sequencing
FunctionalAnalysis: NA
Variant:c.508C>T p.Arg170Trp
ClinVar: 4188245
CAID:
gnomAD:
AdditionalInfo:
4-month, 21-day-old boy
Case3: Four month, 21 day old male
DiseaseAssertion: RCM
FamilyInfo: “No family history of RCM or other cardiovascular diseases was reported.”
ParentalTesting:
CasePresentingHPOs: HP:0000961
CaseHPOFreeText: “late hoarseness” “ dilation of the left and right atria”
CaseNotHPOs:
CaseNotHPOFreeText: “normal ventricular sizes, without calcification of the pericardium, thickened pericardium, or endocardium”
CasePreviousTesting: echocardiography
Genotyping Method: Sanger Sequencing
FunctionalAnalysis:
Variant: c.517C>T p.Leu173Phe
ClinVar: Not found
CAID: CA407440287
gnomAD:
AdditionalInfo: “Unfortunately, tissue velocity images were not obtained and the TTE images of this case were lost.”
A 5-year-old girl had clinical symptoms
Case2: Five year old female
DiseaseAssertion: RCM
FamilyInfo: “No family history of RCM or other cardiovascular diseases was reported.”
ParentalTesting:
CasePresentingHPOs:HP:0002875, HP:0002094
CaseHPOFreeText: “lower extremity edema” “congestive hepatomegaly” “ increased heart shadow without calcification of the pericardium” “bi-atrial enlargement without calcification of the pericardium, thickened pericardium, or endocardium”
CaseNotHPOs:
CaseNotHPOFreeText:
CasePreviousTesting: Abdominal ultrasonography, ECG, Chest X-ray, MRI, Two-dimensional echocardiography
Genotyping Method: Sanger Sequencing
FunctionalAnalysis:
Variant: NM_006757.4(TNNT3):c.575G>A (p.Gly192Asp)
ClinVar: 4633351
CAID:
gnomAD:
AdditionalInfo:
Novel Mutation Lys30Glu in the TPM1 Gene Leads to Pediatric Left Ventricular Non-Compaction and Dilated Cardiomyopathy via Impairment of Structural and Functional Properties of Cardiac Tropomyosin
PMID: 39684770
Gene: TPM1
HGNC ID: 12010
53-year-old woman presented to the cardiology clinic with intermittent short-lasting palpitations
Case 1: One proband; (53-year-old woman)
DiseaseAssertion: Hypertrophic cardiomyopathy (HCM) with fasciculoventricular bypass tract (FVBT)
FamilyInfo: Autosomal dominant family with HCM and pre-excitation. Mother has an ICD for nonischemic cardiomyopathy and progressed from HCM to DCM; sister (49) carries the variant with HCM and NSVT; younger daughter (25) carries the variant with pre-excitation but no HCM. Maternal aunt died suddenly at 42; maternal uncle had a sudden cardiac arrest at 40 with subsequent ICD.
CasePresentingHPOs: HP:0001962; HP:0001639; HP:0004756; HP:0001677; HP:0001671; HP:0004308
CaseHPOFreeText: Palpitations prompted workup. ECG showed pre-excitation; Holter documented NSVT; echo showed HCM without significant outflow obstruction; EP study demonstrated an FVBT with inducible AF; CMR showed midventricular septal thickness of 22 mm with patchy enhancement involving 25% of myocardial mass.
CaseNotHPOs: HP:0001635; HP:0001279; HP:0001645
CaseNotHPOFreeText: No heart failure reported; no syncope; alive at publication.
CasePreviousTesting: ECG (pre-excitation), Holter (NSVT), echo (HCM without significant outflow obstruction), EP study (FVBT with inducible AF), CMR (midventricular septum 22 mm, patchy enhancement 25% of mass).
GenotypingMethod: HCMNext panel (Ambry Genetics); heterozygous c.655G>C (p.Val219Leu) in MYBPC3, reported pathogenic.
FunctionalAnalysis: None performed.
Variant: MYBPC3 NM_000256.3:c.655G>C (p.Val219Leu); heterozygous missense
ClinVar: 42784
CAID: CA015670
gnomAD: 0.00002
AdditionalInfo:N/A
Her mother already had an ICD in place for nonischemic cardiomyopathy
Case1: Pedigree mother; affected carrier; HCM progressing to DCM; clinical case
DiseaseAssertion: Hypertrophic cardiomyopathy progressing to dilated cardiomyopathy, with pre-excitation; MYBPC3-related
FamilyInfo: Carries the familial MYBPC3 variant. ICD in place for nonischemic cardiomyopathy despite optimal medical therapy; never received a shock. Mother of the proband and the sister.
ParentalTesting: Not applicable, this is the transmitting generation.
CasePresentingHPOs: HP:0001639; HP:0001644; HP:0004308
CaseHPOFreeText: Serial echocardiography over 11 years documented progression from hypertrophic to dilated phenotype. ECG showed pre-excitation. ICD implanted; no appropriate or inappropriate therapy to date.
CaseNotHPOs: HP:0001279 ; HP:0001645
CaseNotHPOFreeText: No syncope reported; alive at publication.
CasePreviousTesting: Serial echocardiography; ECG; ICD interrogation.
Genotyping Method: Family screening; carrier status reported.
FunctionalAnalysis: None performed.
Variant: MYBPC3 NM_000256.3:c.655G>C (p.Val219Leu); heterozygous missense
ClinVar: 42784
CAID: CA015670
gnomAD: 0.00002
AdditionalInfo:N/A
The proband of this large family with DA1 presented with bilateral clubfoot and camptodactyly with ulnar deviation of the fingers
Case#: Proband and family; distal arthrogryposis phenotype; clinical case
DiseaseAssertion: Distal arthrogryposis (DA); MYBPC1-related
FamilyInfo: Two MYBPC1 variants segregate in the family. The paper provides the pedigree and segregation data.
ParentalTesting: Not stated
CasePresentingHPOs: HP:0002804
CaseHPOFreeText: Distal arthrogryposis phenotype in affected family members, per the paper's clinical description.
CaseNotHPOs: Not stated
CasePreviousTesting: Clinical evaluation, genetic testing for MYBPC1.
Genotyping Method: Genetic testing confirmed MYBPC1 variants; specific method in the paper.
FunctionalAnalysis: Confirm whether a functional assay was performed.
Variant: MYBPC1, two variants, specific nucleotide changes need confirmation from the paper
ClinVar:N/A
CAID:N/A
gnomAD:N/A
AdditionalInfo: N/A
MYBPC3 e.
Case#:reports one patient with this variant
DiseaseAssertion: Hypertrophic cardiomyopathy (HCM)
FamilyInfo: N/A
ParentalTesting:N/A
CasePresentingHPOs: HP:0001639 "Hypertrophic cardiomyopathy"
CaseHPOFreeText: The study cohort consisted of 23 patients diagnosed with HCM.
CaseNotHPOs: N/A
CaseNotHPOFreeText:N/A
CasePreviousTesting:N/A
Genotyping Method: Sanger sequencing
FunctionalAnalysis: none preformed
Variant: MYBPC3 c.1037G>C, p.Arg346Pro
ClinVar: No exact match, closest is MYBPC3 c.1037G>A
CAID: N/A
gnomAD:N/A
AdditionalInfo: variant is suspected to be novel and potentially pathenogenic
Finding the candidate sequence variants for diagnosis of hypertrophic cardiomyopathy in East Slovak patients
PMID: 28815794
Gene: MYBPC3
HGNC ID: HGNC:7551
Functional Validation of a Novel Homozygous TTN Splice‐Site Variant Reveals Aberrant Splicing in Hypertrophic Cardiomyopathy
PMID: 42698999
Gene: TNN
HGNC ID:11949
ACTC1 variants result in isolated and syndromic cardiac phenotypes
PMID: 40421724 Gene: ACTC1 HGNC ID: 143
A 30-year-old man
Case#: II.3, 30-year-old man from an Indian family.
DiseaseAssertion: Familial hypertrophic cardiomyopathy.
FamilyInfo: Figure 1A. His father (I.1), brother (II.1), and sister (II.2) had HCM and carried TPM1 p.Gln68Arg. His mother (I.2) had a normal echocardiogram and tested negative for the variant. The authors report autosomal dominant segregation.
ParentalTesting: Father positive for TPM1 p.Gln68Arg. Mother negative.
CasePresentingHPOs: HP:0001639, HP:0001712, HP:0005144, HP:0031656, HP:0001653, HP:0010872, HP:4000004
CaseHPOFreeText: Echo showed asymmetric septal hypertrophy and trivial mitral regurgitation. The interventricular septum measured 2.1 cm and the left ventricular posterior wall measured 1.2 cm. ECG showed a left ventricular hypertrophy strain pattern with T-wave inversions in leads II, III, aVF, and V2–V6. Cardiac MRI showed patchy STIR hyperintensity and late gadolinium enhancement in the thickened septum.
CaseNotHPOs: HP:0000822 (no history of hypertension), HP:0032092 (no left ventricular outflow tract obstruction at rest)
CaseNotHPOFreeText: Asymptomatic at presentation. Both atria and the right ventricle were normal in size and function. Left ventricular ejection fraction was 63%.
CasePreviousTesting: NR (prior genetic testing details not available in the article).
Genotyping Method: Custom targeted amplicon sequencing panel of nine sarcomeric genes on the Ion Torrent PGM. Sanger sequencing confirmed the TPM1 variant.
FunctionalAnalysis: NR (functional assay results not available in the article).
Variant: NM_001018005.2(TPM1).203A>G (p.Gln68Arg), heterozygous.
ClinVar: 1490086
CAID: NR (CAID not listed in the article).
gnomAD: No variant record found in gnomAD v4.1 for 15-63044115-A-G.
AdditionalInfo: PMID 38223010. Figure 1A identifies the proband and shows the pedigree. Figures 1B–D show cardiac imaging. Figure 1E shows Sanger sequencing. Figure 1F shows conservation of the affected residue. The authors also report computational predictions of a damaging effect.
A Novel TPM1 Mutation Causes Familial Hypertrophic Cardiomyopathy in an Indian Family: Genetic and Clinical Correlation
PMID 38223010
Gene: TPM1
HGNC ID: 12010
sudden unexpected death of a 37‐year‐old male, with inconclusive autopsy conducted 14 years ago
Case#: Single case; 37-year-old male construction worker; sudden unexplained death (SUD); found dead in bed ~1 hr after lunch, August 2005; molecular autopsy via WES in 2019 from autopsy tissue
DiseaseAssertion: Sudden unexplained death (SUD); no structural cardiac cause at autopsy; MYBPC3/TTN/ACADVL/RYR2-related per WES reevaluation
FamilyInfo: No family history or segregation data reported. The paper is a single molecular autopsy; no relatives were genotyped or phenotyped. No pedigree assessment performed.
ParentalTesting: Not performed, no family members tested.
CasePresentingHPOs: HP:0001698 (Sudden cardiac death); HP:0004756 (Ventricular tachycardia), the latter only as a speculative arrhythmic mechanism, not a documented clinical event
CaseHPOFreeText: Found dead in bed ~1 hr after lunch in August 2005. External examination showed no traumatic injury; toxicological blood screen negative. Clinical history unremarkable. Heart weighed 350 g (reference 331±57 g in men) with regular morphology and volume. Microscopy showed small foci of interstitial fibrosis, deemed not significant. No other organ showed significant abnormality. Case dismissed as SUD, reevaluated in 2019.
CaseNotHPOs: HP:0001639; HP:0001644; HP:0004308; HP:0001279
CaseNotHPOFreeText: No structural cardiac disease at autopsy, no hypertrophy, no dilation, normal heart morphology and volume. No evidence of any cardiomyopathy phenotype. No documented arrhythmia or syncope in life.
CasePreviousTesting: Autopsy (2005) with toxicology, histology. WES (2019) on DNA from FFPE left ventricular tissue; 562-gene cardiac panel (234 SCD/heart-disease genes + 328 heart-expressed genes); filtering against gnomAD (rare = MAF <0.1%); in silico prediction with DANN, MutationTaster, FATHMM, MutationAssessor, PolyPhen-2, SIFT, PROVEAN; ACMG 2015 classification; WebGestalt enrichment analysis.
Genotyping Method: WES on Illumina 500 (TruSeq library prep, xGen exome capture), SeqMule pipeline, ENLIS Genome Research annotation; variants confirmed by Sanger sequencing. Aligned to GRCh37.
FunctionalAnalysis: None performed by the authors, no functional assays in this paper. (ACADVL p.V383A residual activity ~20% is cited from a 2007 external study, not performed here.)
Variant: Four heterozygous missense variants, one per gene
ClinVar:926037
CAID: CA221696968
gnomAD: N/A
AdditionalInfo:N/A
The proband (II.2)
Case1: Male, 24 years old at diagnosis, ethnicity not stated
DiseaseAssertion: Dilated cardiomyopathy (DCM)
FamilyInfo: Three affected family members carry the D94A mutation, mother (I.2, diagnosed age 21 with peripartum cardiomyopathy), sister (II.1, diagnosed age 29), and proband (II.2, diagnosed age 24). Sanger sequencing confirmed the MYL2 variant was present in all three affected family members (I.2, II.1, and II.2).
ParentalTesting: Mother confirmed as heterozygous carrier of D94A mutation with DCM phenotype. Father not a carrier, unaffected
CasePresentingHPOs: HP:0001644, HP:0006699
CaseHPOFreeText: The proband (II.2) and his sister (II.1) were diagnosed at ages 24 and 29 after preventive cardiovascular screening revealed mild global left ventricular systolic dysfunction. Medical therapy was initiated upon evidence of decreased ejection fraction. Patients II.1 and II.2 (proband) displayed abnormal ECG findings and systolic dysfunction as manifested by reduced EF. However, the LV and septal wall thickness were within the normal range.
CaseNotHPOs: NR
CaseNotHPOFreeText: Septal wall thickness measurements were within normal range in all affected family members. LV wall thickness within normal range.
CasePreviousTesting: No prior testing.
Genotyping Method: Twenty two variants, meeting our established criteria for exome sequencing analysis, were identified in the three affected family members of the pedigree. Exome sequencing performed; variant confirmed by Sanger sequencing. Sanger sequencing confirmed the MYL2 variant was present in all three affected family members (I.2, II.1, and II.2)
FunctionalAnalysis: Functional analysis performed on recombinant proteins, not directly on patient samples. Far-UV CD spectroscopy was used to analyze the effect of the D94A mutation on the secondary structure of the RLC. The mutation was observed to induce a reduction in the α-helical content of the RLC and imposed intra-molecular rearrangements. The mutation was seen to impair the binding of RLC to the MHC (myosin heavy chain), and its incorporation into the RLC-depleted porcine myosin. The actin-activated ATPase activity of mutant-reconstituted porcine cardiac myosin was significantly higher compared to ATPase of WT
Variant: NP_000423.2:p.Asp94Ala
ClinVar: 4710041
CAID: CA386698152
gnomAD: NR
AdditionalInfo: Three affected family members carry the variant (mother I.2, sister II.1, proband II.2)
Novel Familial Dilated Cardiomyopathy Mutation in MYL2 Affects the Structure and Function of Myosin Regulatory Light Chain
PMID: 25825243
Gene: MYL2
HGNC ID: 7583
Exome sequencing data reanalysis of 200 hypertrophic cardiomyopathy patients: the HYPERGEN French cohort 5 years after the initial analysis
PMID: 39554508
Gene: TPM1
HGNC ID: 12010
Additional Information: The authors looked at exome data from 200 patients with HCM. They found no TPM1 variants in the HYPERGEN cohort.
Male
Case1: 12 year old male
DiseaseAssertion: RCM
FamilyInfo:
ParentalTesting: Sanger sequencing was deemed healthy.
CasePresentingHPOs:HP:0012378, HP:0003546, HP:0002094, HP:0002240
CaseHPOFreeText: High BNP, enlarged atrium, ST-T segment change, left ventricular restrictive filling in Table 2.
CaseNotHPOs:
CaseNotHPOFreeText:
CasePreviousTesting: Routine blood tests, tuberculin tests, TTE, ECG, chest X-ray. MRI
Genotyping Method: Sanger sequencing
FunctionalAnalysis:
Variant: CA021957
ClinVar:
CAID:
gnomAD:
AdditionalInfo:
Role of Whole-exome Sequencing in Phenotype Classification and Clinical Treatment of Pediatric Restrictive Cardiomyopathy
PMID: 29176140
Gene: TNNI3
HGNC ID: 11947
31-year-old male of European ancestry
Case#: 31 year old man of European ancestry. Patient ID NR.
DiseaseAssertion: Nonischemic dilated cardiomyopathy.
FamilyInfo: No reported family history of dilated cardiomyopathy. Both parents had normal heart exams and echocardiograms.
ParentalTesting: Both biological parents tested negative for the TPM1 variant. Sequencing coverage was 500 to 600×. The authors thought the variant likely arose de novo. They could not rule out parental germline mosaicism.
CasePresentingHPOs: HP:0001644, HP:0025169, HP:0001635, HP:0001640, HP:0002202, HP:0002875, HP:0002094, HP:0012764, HP:0034807
CaseHPOFreeText: He first felt short of breath during activity. Later he felt short of breath at rest. He also had a persistent cough and abdominal swelling. Chest CT showed an enlarged heart and fluid around both lungs. The echo showed that both ventricles were enlarged and pumped poorly. His left ventricular ejection fraction was 12%. His heart failure worsened and he needed a heart transplant.
CaseNotHPOs: HP:4000004 (no myocardial late gadolinium enhancement on cardiac MRI).
CaseNotHPOFreeText: The biopsy and exam of the removed heart did not show evidence of active myocarditis.
CasePreviousTesting: NR
Genotyping Method: The Invitae Dilated Cardiomyopathy Panel used next generation sequencing to test 41 genes.
FunctionalAnalysis: Thin filaments with T237S needed more calcium to reach the same level of activation. At low calcium the mutant filaments were less likely to be open and myosin ATPase activity was lower. Omecamtiv mecarbil restored calcium sensitivity in the lab assay. See Figures 3 through 5 and Tables 1 and 2.
Variant: NM_001018005.2(TPM1):c.710C>G (p.Thr237Ser). Heterozygous.
ClinVar: 1067773
CAID: CA392724554
gnomAD: No variant record found in gnomAD v4.1.
AdditionalInfo: PMID 36739943. Figure 1 shows the echo and biopsy results. The clinical report called the variant a VUS. The study authors considered it likely pathogenic after lab testing.
Functional assays reveal the pathogenic mechanism of a de novo tropomyosin variant identified in patient with dilated cardiomyopathy
PMID: 36739943
Gene: TPM1
HGNC ID: 12010
Selection signatures in four German warmblood horse breeds: Tracing breeding history in the modern sport horse
PMID: 31022261
Gene: TPM1
HGNC ID: HGNC ID:12010
Unveiling cellular mechanisms underlying MYZAP related dilated cardiomyopathy using patient specific hiPSC cardiomyocytes
PMID: 42014428
Gene: MYZAP (myocardium-enriched zonula occludens-1-associated protein
HGNC ID: HGNC:26561
Amish nemaline myopathy and dilated cardiomyopathy caused by a homozygous contiguous gene deletion of TNNT1 and TNNI3 in a Mennonite child
PMID: 30395933
Gene: TNNT1
HGNC ID: 11947
38-year-old man
Case1: 38 year old male
DiseaseAssertion: . Two missense variants in MYBPC3 (NM_000256.3): c.2533C>G in exon 26 (C6 domain) were identified and, classified as a variant of uncertain significance (VUS, score 2), and c.1696T>A in exon 18 (C4 domain), a VUS with a score of 5.
FamilyInfo: There was no family history of cardiomyopathy or SCD.
ParentalTesting: NR
CasePresentingHPOs: HP:0004751, HP:0006682, HP:0001712
CaseHPOFreeText: 38 year old man, suffering from contractions, and one short run of non-sustained ventricular tachycardia lasting four beats. Asymmetric septal hypertrophy with a maximum thickness of 19 mm. In addition, marked biatrial enlargement was evident, with a left atrial volume index of 79 mL/m² and right atrial area of 25 cm². Importantly, extensive diffuse late gadolinium enhancement (LGE) was detected in the basal and mid-septal and anterior segments, involving 17% of the myocardial mass
CaseNotHPOs: NR
CasePreviousTesting: genetic testing was performed using the Health in Code HCM panel, which includes the following 18 genes: ACTC1, DES, FHL1, FHOD3, GLA, LAMP2, MYBPC3, MYH7, MYL2, MYL3, PRKAG2, PTPN11, TNNC1, TNNI3, TNNT2, TPM1, TRIM63, and TTR.
Genotyping Method: Health in Code HCM panel
FunctionalAnalysis:
Variant: NM_000256.3:c.2533C>G, NM_000256.3:c.1696T>A
ClinVarID:180973, 915724
CAID:CA380324353, CA012504
gnomAD:
AdditionalInfo:NR
Genetic basis and outcome in a nationwide study of Finnish patients with hypertrophic cardiomyopathy
PMID: 30775854
Gene: MYH7
HGNC ID: HGNC:7577
ACTC1/cardiac actin (c.664G > A/p.Ala222Thr) and TTN/titin (c.33250G > A/p.Glu11084Lys).
Case:Male, 1 year old, Mexican.
DiseaseAssertion:Dilated cardiomyopathy (DCM), severe heart failure, and sudden cardiac death.
Familyinfo:The patient was born to apparently healthy parents. No family history of sudden cardiac death or cardiac-related deaths was reported. The father carried the TTN variant, which was also found in the patient's brother. The ACTC1 variant was absent in both parents and the brother, supporting a de novo origin.
ParentalTesting:Both parents were tested using Sanger sequencing. The father carried the TTN variant, while neither parent carried the ACTC1 variant. The brother also carried the TTN variant but not the ACTC1 variant.
CasePresentingHPOs:HP:0001644, HP:0001635, HP:0001640, HP:0025169
CaseHPOFreeText:The patient presented with severe left ventricular dilation and reduced cardiac function. Echocardiography showed an ejection fraction of 7%. Additional findings included pulmonary edema, pulmonary venous congestion, tachycardia, tachypnea, hypotension, diaphoresis, and a systolic heart murmur. The patient underwent pulmonary artery banding as a bridge to heart transplantation but died suddenly at home six months later while awaiting transplantation.
CaseNotHPOs:not reported
CaseNOTHPOFreeText:No specific negative phenotypes documented for the proband.
CasePreviousTesting:Clinical evaluation included electrocardiography, chest radiography, Doppler echocardiography, and genetic screening. The patient underwent next-generation sequencing of 132 genes associated with structural and electrical cardiac conditions. GenotypingMethod:Next generation sequencing using a targeted gene panel. Variants were validated through Sanger sequencing. Genomic DNA was extracted from peripheral blood lymphocytes.
FunctionalAnalysis:No direct experimental functional analysis of the patient's variants was performed. Computational protein modeling demonstrated structural and electrostatic changes associated with ACTC1 p.Ala222Thr and altered compact conformations associated with TTN p.Glu11084Lys.
Variant:ACTC1: NM_005159.5, c.664G>A, p.Ala222Thr and TTN: NM_001256850.1, c.33250G>A, p.Glu11084Lys
ClinVar:The article reports previous ClinVar entries for the TTN variant, including VUS and benign classifications. No specific ClinVar accession for the ACTC1 variant was provided.
CAID:not reported
gnomAD:not reported
AdditionalInfo:This case involved two rare genetic variants in cardiac structural genes. The ACTC1 variant was de novo, while the TTN variant was inherited from the father and was also present in the asymptomatic brother. The authors proposed that the combination of both variants may have contributed to the severe early-onset cardiomyopathy.
Novel mutation associated with non‐compaction ventricular myocardium: A case report
PMID: 40956134
Gene: MYL2
HGNC ID: 7583
The index case was an 88-year-old woman (II.5)
Case1: Female, 85 at diagnosis, ethnicity not stated
DiseaseAssertion: Hypertrophic cardiomyopathy (HCM)
FamilyInfo: An index patient’s brother (II.6) was reported with moderate HCM and another brother (II.7) with sudden cardiac death at the age of 40 years. The clinical screening led to the diagnosis of HCM in two of the index patient’s descendants, a daughter and a son. Daughter (III.4, age 59) with septal hypertrophy of 16 mm confirmed by cardiac MRI, son (III.8, age 47) with septal hypertrophy of 15 mm. Daughter (III.6, age 50) is an unaffected carrier. Five other relatives (III.1, III.5, III.6, III.7, IV.1) were healthy with normal cardiac evaluation. Pedigree shown in Figure 1.
ParentalTesting: Not preformed.
CasePresentingHPOs: HP:0001639, HP:0001279
CaseHPOFreeText: Admitted to the emergency unit with chest pain after a pre-syncopal episode at the age of 85. Electrocardiogram showed sinus rhythm, negative T waves in V1-V3 and signs of ventricular hypertrophy. Transthoracic echocardiography detected asymmetric septal hypertrophy of 25 mm with preserved ejection fraction, moderate diastolic dysfunction and mild left atrial enlargement. Twenty-four-hour Holter monitoring documented episodes of non-sustained ventricular tachycardia defined as ≥ 3 beats at a rate of ≥ 120 bpm
CaseNotHPOs: NR
CaseNotHPOFreeText: Coronary artery disease was ruled out
CasePreviousTesting: NR
Genotyping Method: The index patient’s genomic DNA was subjected to massively parallel sequencing to identify the genetic origin of the disease using a 251-gene cardiomyopathy diagnostic panel. Targeted massively parallel sequencing of the index patient’s genomic DNA was performed with an Agilent SureSelect custom library covering 251 genes. For the MYBPC3 gene: all exons including the complete sequence of introns. Sequencing performed on NovaSeq 6000 (Illumina), bioinformatics pipeline using BWA alignment and GATK variant calling, reference genome GRCh37/hg19. Sanger sequencing confirmed both variants
FunctionalAnalysis: Minigene and patient blood RNA splicing assays performed. Both the minigene and patients’ RNA splicing assays revealed that the MYBPC3 c.3331−26T>G variant promoted complete intron 30 retention in the mRNA, and also partial retention of the second half of intron 30. Normal MYBPC3 mRNA was not detected in the MUT lanes. The corresponding normal MYBPC3 fusion protein was not detected with either of the two antibodies in cells transfected with the MUT plasmid.
Variant: NM_000256.3:c.3331−26T>G
ClinVar: 1320039
CAID: CA2573146361
gnomAD: chr11-47332999-A-C
AdditionalInfo: This paper also identified two additional unrelated HCM probands carrying c.3331−26T>G in a large cohort of 9,611 HCM probands
Identification of an elusive spliceogenic MYBPC3 variant in an otherwise genotype-negative hypertrophic cardiomyopathy pedigree
PMID: 35513690
Gene: MYBPC3
HGNC ID: 7551
Natural history and clinical outcomes of patients with hypertrophic cardiomyopathy from thin filament mutations
PMID: 38773858
Gene: TPM1
HGNC ID: 12010
Additional Information: This review included patients with HCM and TPM1 variants. The results are reported by group. Table S3 shows what information each study provided. It does not link a specific TPM1 variant to an individual patient.
Genetic variants in Chinese patients with sporadic dilated cardiomyopathy: a cross-sectional study
PMID: 35284542
Gene: MYBPC3
HGNC ID: HGNC ID:7551
woman with autosomal dominant Alport syndrome (ADAS) with a family history of left ventricular noncompaction cardiomyopathy (LVNC). Exome sequencing identified a rare heterozygous variant in COL4A4, NM_000092.5: c.2510G>C (p.G837A), and a novel heterozygous variant in ACTC1, NM_005159.5: c.922T>C (p.Y308H), as causes of ADAS and LVNC, respectively.
Case:Female, 21 year old.
DiseaseAssertion:Left ventricular noncompaction cardiomyopathy (LVNC).
Familyinfo:The patient's father had hypertrophic cardiomyopathy. Her paternal grandfather and paternal uncle also reportedly had cardiac disease, although detailed clinical information was unavailable. The patient's mother had microscopic hematuria and was diagnosed with thin basement membrane nephropathy. The maternal grandmother also had a history of kidney disease.
ParentalTesting:The mother was tested and did not carry the ACTC1 c.922T>C variant. The father could not be tested because the patient had no contact with him. The authors presumed paternal inheritance of the ACTC1 variant based on the family history, but paternal inheritance was not genetically confirmed.
CasePresentingHPOs:HP:0030682, HP:0000790, HP:0001712
CaseHPOFreeText:The patient had microscopic hematuria beginning at age 6. At the same age, routine school screening identified cardiac dysfunction, and echocardiography revealed a myocardial densification defect. At age 21, echocardiography showed a noncompacted-to-compacted myocardial ratio greater than 2:1, consistent with LVNC. Electrocardiography showed sinus rhythm with ST-T wave flattening in leads V4–V6, indicative of cardiac hypertrophy. The patient remained without cardiac symptoms and had a normal ejection fraction. Her BNP level increased to 204 pg/mL. She had normal renal function, with a serum creatinine level of 0.58 mg/dL, and no proteinuria.
CaseNotHPOs:Hearing impairment: not reported, Ophthalmological abnormalities: not reported, Cardiac symptoms: not reported
CaseNOTHPOFreeText:The patient remained asymptomatic despite the cardiac findings. No hearing impairment or ophthalmological abnormalities were identified.
CasePreviousTesting:Echocardiography identified LVNC during childhood. Further cardiac evaluation included electrocardiography and follow-up BNP measurements. Renal evaluation included serum creatinine testing, urinalysis, abdominal ultrasonography, and genetic evaluation for hereditary kidney disease.
GenotypingMethod:Whole exome sequencing was performed using DNA extracted from the patient's blood sample. Sanger sequencing was used to confirm both identified variants. The mother's DNA was also analyzed to determine inheritance.
FunctionalAnalysis:No direct functional studies were performed on the ACTC1 variant. The authors used AlphaFold3 protein structure prediction to examine the effect of the amino acid substitution. The variant was located near the ATP-binding site, suggesting a possible effect on ACTC1 function and ATP binding.
Variant:NM_005159.5 (ACTC1): c.922T>C; p.(Tyr308His).
ClinVar:accession: VCV000948806.7.
CAID:not reported
gnomAD:not reported
AdditionalInfo:The patient carried two separate heterozygous variants associated with different conditions. The COL4A4 c.2510G>C (p.Gly837Ala) variant was associated with autosomal dominant Alport syndrome, while the ACTC1 c.922T>C (p.Tyr308His) variant was identified as a candidate associated with LVNC. The ACTC1 variant was classified as a variant of uncertain significance (VUS) by the authors using ACMG criteria (PM2, PP3, PP4). The authors noted that there were no functional studies confirming its effect on ACTC1 protein function.
a male patient who was found to carry a novel pathogenic missense mutation in the MYBPC3 gene (chr11:4737288835, NM_000256.3: c.194 C > T, p.T65M)
Case#: a male in the age range of 36-40
DiseaseAssertion: Dilated cardiomyopathy and generated hiPSC-CMS
FamilyInfo: not reported
ParentalTesting: not reported
CasePresentingHPOs: HP:0002875, HP:0031352 Exertional dyspnea and chest tightness
CaseHPOFreeText: nocturnal dyspnea and reduced exercise tolerance
CaseNotHPOs:
CaseNotHPOFreeText:
CasePreviousTesting: echocardiogram and electrocardiograms
Genotyping Method: peripheral blood was extracted and use to sequence the entire genome
FunctionalAnalysis: hiPSCs were looked at in this case
Variant: NM_000256.3: c.194 C > T (p.Thr65Met)
ClinVar:407324
CAID: CA047700
gnomAD: 11-47372888-G-A
AdditionalInfo:F
Layer 5: Trace evals. Evaluate the internal execution path: model calls, tool calls, handoffs, guardrails, retries, intermediate reasoning. They are the agentic equivalent of replaying the game tape: the final score matters, but the coach wants to know how the team played.
这部分 trace的eval 需要借助API 分析
EIP21–––Renal cysts, renal cell carcinoma, and CNS hemangioblastomas in family members1
PatientID: IP (Proband)
KindredID: E
Case: M, 21Y0M, Hungarian
DiseaseAssertion: VHL
FamilyInfo: Index patient was a 21-year-old man who had bilateral renal masses and renal cysts. Family history indicated a high suspicion for VHL disease, as his mother was operated for renal cell carcinoma, his uncle had spinal cord tumor, and his grandmother underwent operation for renal cell carcinoma. However, detailed clinical evaluation could not be performed in family members.
CasePresentingHPOs: HP:0005584; HP:0005562 (Renal cell carcinoma, Multiple renal cysts)
CaseHPOFreeText: Presented with bilateral highly vascularized renal masses and a large number of renal cysts. Diagnosed with VHL Type 1. Renal masses are noted as renal cell carcinoma in Table 1.
CaseNotHPOs: HP:0002666; HP:0009711; HP:0010797 (Pheochromocytoma, Retinal capillary hemangioma, Hemangioblastoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.F119Qfs*12 (c.354_355del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA915940709, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.354_355del
gnomAD: N/A
VariantEvidence: N/A
MutationType: deletion; minus_2_frameshift_variant
CivicName: F119fs (c.354_355del)
MultipleGeneVariants: N/A
MethodsGenetic testing was proposed and performed once the patient gave his/her informed consent to do so either on his/her DNA or on those or her/his affected minor child. Genetic analysis consists in the search of germ line mutation of VHL, SDHB, SDHD, SDHC (all coding exons and intron-exon junctions are investigated) or RET (only exons 10, 11, 15 and 16 are studied) by PCR-sequencing on both strands of DNA, as previously described (5). For interpretation of genetic testing, a germline mutation was considered as pathogenic if i) it had already been described in the medical literature and/or ii) it was recorded in international genetic databases such as human gene mutation database or LOVD (7). By contrast, mutation was classified as not clearly pathogenic (nucleotide variant) if the available data were not convincing (new mutation without any functional study such as those affecting the NRF-2 cis-regulatory site of SDHB promoter) or if its status was controversial in the literature (for example VHL P25L variant (8)). For patients with bilateral pheochromocytoma who were mutation negative, a search for a deletion of VHL or SDHs was carried out by multiplex PCR or/and multiplex-ligation dependent probe assay (MLPA) respectively. The laboratory participates in the proficiency testing organized by the European Molecular genetics Quality Network–DNA sequencing scheme) and to the quality assurance testing organized by the French network of molecular biology laboratories working on endocrine tumours (GTE).
ArticleReferenceSequence: Not specified – only protein change was documented by the author, nucleotide variant was found under reference sequence NM_000551.3
GenotypingMethod: Genetic analysis consists in the search of germ line mutation of VHL, SDHB, SDHD, SDHC (all coding exons and intron-exon junctions are investigated) or RET (only exons 10, 11, 15 and 16 are studied) by PCR-sequencing on both strands of DNA
SamplingMethod: Not specified
A missense germline mutation in exon 1of the VHL gene was identified in the patient (p. Asp92Gly). The patient's family members (parents and 2 daughters aged 10 and 5 yr) then underwent genetic testing. The mutation was found in the youngest daughter. Full evaluation of the positive carrier did not reveal any tumor localization.
PatientID: None (daughter)
KindredID: 1
Case: F, 5Y0M, ethnicity unknown
DiseaseAssertion: asymptomatic
FamilyInfo: The patient's family members (grandparents, mother (33Y0M; Case 1) and sister (10Y0M) underwent genetic testing. Sister and grandparents were not positive, however mother was found positive with the same mutation.
CasePresentingHPOs: None
CaseHPOFreeText: Full evaluation did not reveal any tumor localization.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.D92G (c.275A>G)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: N/A
CAID: CA351750765 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.275A%3EG
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: D92G (c.275A>G)
MultipleGeneVariants: N/A
nt 776, T to C, Leu to Pro
Fourty-four of 389 patients with VHL (between 1988-1999) screened positive for pancreatic neuroendocrine tumours (PNETs) either by pathologic analysis of tissue specimens or by characteristic radiographic appearance on CT and MRI. VHL gene germline mutations were determined by quantitative Southern blotting to detect deletions of the gene and gene rearrangements as well as complete gene sequencing. Patient 44 (39 year old male) was found to harbour the c.563T>C mutation in the VHL gene (stated as 776 T to C in the paper which used the Latif sequence as reference) resulting in a Leu to protein change at position 188. The patient presented with two pathologic pancreatic neuroendocrine tumors. ACMG evidence codes: 'PP4' since the patient presents phenotypes highly specific for a disease with a single genetic etiology.
1729Fnt 439-441 del TTC, del PheP, 26007
PatientID: 17
KindredID: 6007
Case: F, 31Y9M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CasePresentingHPOs: HP:0030405 (pancreatic endocrine tumour)
CaseHPOFreeText: She presented with 1 radiographic pancreatic neuroendocrine tumor diagnosed at age 29Y. Follow up 33M after WP surgery, currently no evidence of disease.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.F76del (c.227_229delTCT)
LegacyVariant: p.delF (c.439_441delTTC)
CaseProblemVariantFreeText: NM_000551.3:c.226_228delTTC automaps to NM_000551.3:c.227_229delTCT
ClinVarID: N/A
CAID: CA357012, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.227_229del
gnomAD: N/A
VariantEvidence: N/A
MutationType: inframe_deletion
CivicName: F76del (c.227_229del)
MultipleGeneVariants: N/A
3050Mnt 712 C to T, Arg to TrpR, 13407
PatientID: 30
KindredID: 3407
Case: M, 50Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Another member of his family (patient 31) presented with one radiologic pancreatic neuroendocrine tumor and had the same VHL gene mutation.
CasePresentingHPOs: HP:0030405 (pancreatic endocrine tumour)
CaseHPOFreeText: He presented with one radiologic pancreatic endocrine tumour.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167W (c.499C>T)
LegacyVariant: p.R167W (c.712C>T)
CaseProblemVariantFreeText: N/A
ClinVar: 2218 https://www.ncbi.nlm.nih.gov/clinvar/variation/2218/
CAID: CA020450 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.499C%3ET
gnomAD: 0.000007954 https://gnomad.broadinstitute.org/variant/3-10191506-C-T
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: R167W (c.499C>T)
MultipleGeneVariants: N/A
Germline mutations were identified in 300/469 (63%) of the families tested; 137 distinct intragenic germline mutations were detected.
Germline mutational data on VHL was gathered from various countries to assess variation in germline mutations that produce disease within different populations. Families were grouped according to three possible outcomes of disease: renal cell carcinoma without pheochromocytoma, renal cell carcinoma with pheochromocytoma, or pheochromocytoma alone. SSCP and denaturing gradient gel electrophoresis identified mutations in 300/469 (63%) of families affected with VHL. This germline familial VHL mutation (G93fs (c.277delG)) was taken from the Bristol Myers Squibb database, with an unknown number of members belonging to Family ID 16BMS. It was reported in the paper as c.490delG due to a difference in transcript reference. As reported in Table 3, this mutation is found in VHL families without pheochromocytoma, and with renal cell carcinoma.
Germline mutations were identified in 300/469 (63%) of the families tested; 137 distinct intragenic germline mutations were detected.
GroupID/ KindredID: 6CE
DiseaseAssertion: VHL
GroupSize: N/A
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: N/A
GroupAgeRange: N/A
GroupInfo: This germline familial VHL mutation was taken from the Munich, university of Freiburg and Institute of Pathology database, with an unknown number of members belonging to Family ID 6CE. Table 3 lists all ID and mutations associated with individuals possessing renal carcinoma, without pheochromocytoma.
GroupPresentingHPOs: HP:0005548 (renal cell carcinoma)
GroupHPOFreeText: Described as a VHL family with RCC, without pheochromocytoma. Other phenotypes are likely, however not detailed in this publication
GroupNotHPOs: HP:0002666 (pheochromocytoma)
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.S183* (c.548C>A)
LegacyVariant: p.S183* (c.761C>A)
CaseProblemVariantFreeText: N/A
ClinVarID: 2215 https://www.ncbi.nlm.nih.gov/clinvar/variation/2215/
CAID: N/A
gnomAD: N/A
VariantEvidence: This paper declares this variant is predicted to compromise the Elongin-binding site either by truncating the protein or by location between codons 157 and 189.
MutationType: stop_gained
CivicName: S183* (c.548C>A)
MultipleGeneVariants: N/A
Germline mutations were identified in 300/469 (63%) of the families tested; 137 distinct intragenic germline mutations were detected.
GroupID/ KindredID: 11YO
DiseaseAssertion: VHL
GroupSize: N/A
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: N/A
GroupAgeRange: N/A
GroupInfo: This germline familial VHL mutation was taken from the Department of Uroglogy, Yokohama database, with an unknown number of members belonging to Family ID 11YO. Table 3 lists all ID and mutations associated with individuals possessing renal carcinoma, without pheochromocytoma.
GroupPresentingHPOs: HP:0005548 (renal cell carcinoma)
GroupHPOFreeText: Described as a VHL family with RCC, without pheochromocytoma. Other phenotypes are likely, however not detailed in this publication
GroupNotHPOs: HP:0002666 (pheochromocytoma)
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.C162Y (c.485G>A)
LegacyVariant: p.C162Y (c.698G>A)
CaseProblemVariantFreeText: N/A
ClinVarID: 223225 https://www.ncbi.nlm.nih.gov/clinvar/variation/223225/
CAID: N/A
gnomAD: N/A
VariantEvidence: This paper declares this variant is predicted to compromise the Elongin-binding site by location between codons 157 and 189.
MutationType: missense_variant; transition
CivicName: C162Y (c.485G>A)
MultipleGeneVariants: N/A
Germline mutations were identified in 300/469 (63%) of the families tested; 137 distinct intragenic germline mutations were detected.
Germline mutational data on VHL was gathered from various countries to assess variation in germline mutations that produce disease within different populations. Families were grouped according to three possible outcomes of disease: renal cell carcinoma without pheochromocytoma, renal cell carcinoma with pheochromocytoma, or pheochromocytoma alone. SSCP and denaturing gradient gel electrophoresis identified mutations in 300/469 (63%) of families affected with VHL. This germline familial VHL mutation (E186K (c.556G>A)) was taken from the National Cancer Institute database, with an unknown number of members belonging to Family ID 3736NCI. It was reported in the paper as c.769G>A due to a difference in transcript reference. As reported in Table 3, this mutation is found in VHL families without pheochromocytoma, and with renal cell carcinoma. Later publications reference this cohort as being reported in PMIDs: 7728151 and 9829911.
Germline mutations were identified in 300/469 (63%) of the families tested; 137 distinct intragenic germline mutations were detected.
Germline mutational data on VHL was gathered from various countries to assess variation in germline mutations that produce disease within different populations. Families were grouped according to three possible outcomes of disease: renal cell carcinoma without pheochromocytoma, renal cell carcinoma with pheochromocytoma, or pheochromocytoma alone. SSCP and denaturing gradient gel electrophoresis identified mutations in 300/469 (63%) of families affected with VHL. This germline familial VHL mutation (E186del (c.558_560del)) was taken from the Cambridge, Department of Pathology database, with an unknown number of members belonging to Family ID 113CA. It was reported in the paper as c.771_773delGlu due to a difference in transcript reference. Table 5 lists all ID and mutations associated with individuals without detailed clinical information. Other phenotypes are possible, however not detailed here.
Molecular cytogenetic characterization of early and late renal cell carcinomas in Von Hippel-Lindau disease
PMID: 11284029
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
GroupID: 53
DiseaseAssertion: VHL
GroupSize: 2
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: French
GroupAgeRange: N/A
GroupInfo: 2 members of this family were found to harbor the c.407T>C germline variant of the VHL gene. Members 939 and 1460 presented with severe renal disease (RCC). Families were recruited from the French VHL Registry. Enrolment in the study required identification of the germline VHL mutation (currently 85% of the families included in the French VHL Registry) and available data regarding renal phenotype. A total of 126 families fulfilled these criteria.
GroupPresentingHPOs: HP:0005584 (Renal cell carcinoma)
GroupHPOFreeText: Severe renal disease (any solid lesion before 25 years of age, five or more solid lesions within one or two kidneys, or metastasis of renal cell carcinoma).
GroupNotHPOs: N/A
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: Paper states that this family is previously reported in PMID 12202531 and/or 9829912, where 2 and 2 individuals respectively with this mutation are reported. It is unclear if one or both of these previously reported groups are the same as the current family. One or both of these previously reported patients could correspond to family 94 in the current paper.
SupplementalData: Phenotype and genotype information can be found in Supplementary Table S1.
Variant: p.F136S (c.407T>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 496064, https://www.ncbi.nlm.nih.gov/clinvar/variation/496064/
CAID: N/A
gnomAD: 0.000003976, https://gnomad.broadinstitute.org/variant/3-10188264-T-C?dataset=gnomad_r2_1
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: F136S (c.407T>C)
MultipleGeneVariants: N/A
nt 712 C/T 167 Arg→Trp R167W Missense 5
A cohort of 141 patients with hemangioblastomas of the central nervous system was analyzed. 81 patients had germline mutations in the VHL gene, analyzed through peripheral blood by Southern blotting and SSCP analysis. This missense mutation (c.499C>T) was recorded in the paper as c.712C>T due to a difference in transcript sequence. It was found in 5 patients with hemangioblastomas of the central nervous system, one of which had primary asymptomatic tumors. Any family information or relations is unknown. No other phenotypes described.
GroupID/ KindredID: F31
Case: Sex unknown, 19Y0M, Spanish
DiseaseAssertion: assumed VHL
FamilyInfo: familial antecedents found; unknown of any additional features to index case relatives
CasePresentingHPOs: HP:0009711; HP:0009713; HP:0006880; HP:0000107; HP:0001737 (retinal capillary hemangioma, spinal hemangioblastoma, cerebellar hemangioblastoma, renal cysts, pancreatic cysts)
CaseHPOFreeText: Age of onset is 19Y0M.
CaseNotHPOs: HP:0006770;HP:0002666 (clear cell renal cell carcinoma, pheochromocytoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.D126Efs*6 (c.377_378insG)
LegacyVariant: g.5429_5430insG
CaseProblemVariantFreeText: Patient was reported with the g. (genomic) coding positions. The g.5429_5430insG variant worked out to correspond with c.377_378insG.
ClinVarID: N/A
CAID: CA2499307020 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/by_caid?caid=CA2499307020
gnomAD: N/A
VariantEvidence: N/A
MutationType: plus_1_frameshift_variant
CivicName: D126fs* (c.377_378insG)
MultipleGeneVariants: N/A
Table 1
PatientID: N/A
KindredID: 19
Case: Sex Unknown, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Family history not mentioned. Patient’s variant reported as germline.
CasePresentingHPOs: N/A
CaseHPOFreeText: Patient had VHL disease type 1 (see table 1).
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 9829911
SupplementalData: N/A
Variant: p.F76del (c.227_229del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA357012, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.227_229delTCT
gnomAD: N/A
VariantEvidence: Variant reported as c.226_228del and was mapped to c.227_229del.
MutationType: inframe_deletion
CivicName: F76del (c.227_229del)
MultipleGeneVariants: N/A
exon3-codon 170 GTC->GGC with a p.Val170Gly substitution
A 13-year-old boy was screened for a VHL mutation at 7-years-old upon identification of a missense V170G(c.509T>G) variant in the patient's father. Genetic screening of the patient also revealed that he was a carrier of same mutation as his father, but without expression of the disease at diagnosis. The father had been operated on for a bilateral pheochromocytoma at 12 years old. Upon diagnosis, annual follow ups were performed on the patient and appeared normal. At 13-years-old the patient was rushed to the hospital due to polyuria, headache, flushes, and abnormal perspiration. Abdominal ultrasonography revealed an adrenal gland tumor. His vitals were monitored and high blood pressure was treated with antihypertensive bitherapy combining an α- and β-blocker (labetalol) with a calcium antagonist (nicardipine). An MRI confirmed that the adrenal gland tumour was compatible with a pheochromocytoma. Adrenalectomy was performed, followed by slowly weaning the patient of the medications. At the last follow up 2 years after surgery, there has been no recurrence.
The cytosine replaced the 716th guanine on four patients and three carriers of virulence gene from the first family, which made the 168th serine replaced by threonine.
PatientID: III-6
KindredID: 1
Case: M, Age Unknown, Chinese
DiseaseAssertion: CNS Hemangioblastoma
FamilyInfo: The transversion mutation was found and confirmed in 4 patients (II-2, III-2, III-6, III-10, III-11) and 3 carriers (III-3, III-9, III-14). At least 5 additional members had VHL phenotypes, but had all passed away before genetic testing. Could be assumed and deduced their genetics due to pedigree showing future linear relations of this mutation all in generation III.
CasePresentingHPOs: HP:0010797 (hemangioblastoma)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.S168T (c.503G>C)
LegacyVariant: p.S168T (c.716G>C)
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351756183 https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.503G%3EC
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: S168T (c.503G>C)
MultipleGeneVariants: N/A
194C>T Ser65Leu Germline mutation
PatientID: 30
KindredID: 30
Case: Age, sex, ethnicity unknown
DiseaseAssertion: hemangioblastoma
FamilyInfo: N/A
CasePresentingHPOs: HP:0010797 (hemangioblastoma)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.S65L (c.194C>T)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: 182975 https://www.ncbi.nlm.nih.gov/clinvar/variation/182975/
CAID: N/A
gnomAD: https://gnomad.broadinstitute.org/variant/3-10183725-C-T
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: S65L (c.194C>T) AND L89P (c.266T>A)
MultipleGeneVariants: Somatic, VHL, c.266T>A (p.Leu89Pro)
Rathke's cleft cysts in twins with type 2C von Hippel-Lindau disease
PMID: 24877602
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
PatientID: None
KindredID: 9
Case: F, 22Y0M, Ethnicity unknown
DiseaseAssertion: assumed VHL
FamilyInfo: No familial/syndromic (FS) association
CasePresentingHPOs: HP:0002666; HP:0002668 (pheochromocytoma, paraganglioma)
CaseHPOFreeText: Sympathetic PGL with an onset of 11Y0M and a benign bilateral pheochromocytoma at 22Y0M
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: SDHB,SDHC, SDHD, and exons 10, 11, 13, 14, 15 and 16 of RET proto-oncogene
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167Q (c.500G>A)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVar: 2216 https://www.ncbi.nlm.nih.gov/clinvar/variation/2216/
CAID: N/A
gnomAD: 0.000003977 https://gnomad.broadinstitute.org/variant/3-10191507-G-A
VariantEvidence:N/A
MutationType: missense_variant;transition
CivicName: R167Q (c.500G>A)
MultipleGeneVariants: N/A
PatientID: None
KindredID: 8
Case: M, 15Y0M, Ethnicity unknown
DiseaseAssertion: assumed VHL
FamilyInfo: Familial/syndromic (FS) association
CasePresentingHPOs: HP:0002666; HP:0002668; HP:0009711 (Pheochromocytoma; paraganglioma; retinal capillary hemangioma)
CaseHPOFreeText: Benign sympathetic Paraganglioma at age 12Y0M and unilateral pheochromocytoma at age 15Y0M; as well as retinal angioma (age unclear)
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: SDHB,SDHC, SDHD, and exons 10, 11, 13, 14, 15 and 16 of RET proto-oncogene
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.Y98S (c.293A>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 219160 https://www.ncbi.nlm.nih.gov/clinvar/variation/219160/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: Y98S (c.293A>C)
MultipleGeneVariants: N/A
Primary Renal Paragangliomas and Renal Neoplasia Associated with Pheochromocytoma/Paraganglioma: Analysis of von Hippel–Lindau (VHL), Succinate Dehydrogenase (SDHX) and Transmembrane Protein 127 (TMEM127)
PMID: 28646318
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
the patient had an affected daughter
PatientID: None
KindredID: 3
Case: F, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Her father had this VHL mutation and presented with renal cell carcinoma.
CasePresentingHPOs: N/A
CaseHPOFreeText: She is described as affected but her phenotypes are not outlined.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: Previously published in 24301059.
SupplementalData: N/A
Variant: p.R161* (c.481C>T)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: 2217 https://www.ncbi.nlm.nih.gov/clinvar/variation/2217/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: stop_gained
CivicName: R161* (c.481C>T)
MultipleGeneVariants: N/A
M193948Yes†An affected daughter.Bilateral RCC2Yesc.481C>T p.(Arg161*)1.71.811.1 (right RCC)
PatientID: None
KindredID: 3
Case: M, 48Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: He had a daughter who has heterozygous for the mutation.
CasePresentingHPOs: HP:0005584 (Renal cell carcinoma)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: Previously published in 24301059.
SupplementalData: N/A
Variant: p.R161* (c.481C>T)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: 2217 https://www.ncbi.nlm.nih.gov/clinvar/variation/2217/
CAID: N/A
gnomAD: N/A
VariantEvidence: The patient had a mosaic mutation with a mutated allele frequency of 1.7%. The right renal cell carcinoma was analyzed and found to have a mutated allele frequency of 11.1%. Copy number events of the mutated and wild type allele are available in table S4 of the supplemental.
MutationType: stop_gained
CivicName: R161* (c.481C>T)
MultipleGeneVariants: N/A
PatientID: III-46
KindredID: 1
Case: F, Age unknown, Ethnicity Unknown
DiseaseAssertion: asymptomatic
FamilyInfo: Large multigenerational family with a history of both VHL and spinocerebellar ataxia type 2 (SCA2). Screening for clinical and genetic diagnostics were gathered as well as thorough information on non-living members. Her sister, dad and grandmother appeared to have the VHL mutation. See family pedigree (Fig. 1).
CasePresentingHPOs: None
CaseHPOFreeText: VHL found by genetic testing not clinical findings.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.E160Sfs*10 (c.477delA)
LegacyVariant: c.688delA
CaseProblemVariantFreeText: c.477del, p.Glu160Serfs10 should be used. Details: 477del same as 475delA bc that codon is AAA so doesn't matter which A gets deleted: there is an A at 475 476 477 so for HGVS we say that 477 (the latter) is deleted since that follows HGVS nomenclature. Thus use c.477del: p.Glu160Serfs10
ClinVarID: 182959 https://www.ncbi.nlm.nih.gov/clinvar/variation/182959/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: minus_1_frameshift_variant
CivicName: E160fs (c.477del)
MultipleGeneVariants: N/A
Genotype-phenotype correlations of 573 VHL patients from 200 kindreds were analyzed and confirmed that higher risk of pheochromocytoma is associated with missense mutations that result in substitution of a surface amino acid or that disrupt the structural integrity of the VHL gene product (pVHL). Age-related risks of retinal hemangoblastomas and renal cell carcinoma were higher in patients with nonsense or frameshift mutations. Southern blot and/or MLPA analysis by whole blood detected this mutation (c.606dupA) was found in a patient with hemangioblastomas of the cerebellum at 25Y old. No family info was provided.
GroupID: 21
Case: Age unknown, Sex Unknown, Ethnicity Unknown
DiseaseAssertion: asymptomatic
FamilyInfo: 1 of the 573 patients discussed in this paper were found to have this variant. This mutation was found in 1 VHL family with a single patient.
CasePresentingHPOs: Unknown
CaseHPOFreeText: N/A
CaseNotHPOs: HP:0009711; HP:0005584; HP:0002666; HP:0006880 (retinal capillary hemangioma; renal cell carcinoma; pheochromocytoma; cerebellar hemangioblastoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Supplementary Table S1.
Variant: p.T124Mfs*33 (c.371_377delCACACGA)
LegacyVariant: p.T124Mfs*33 (c.369_375delGACACAC)
CaseProblemVariantFreeText: written in paper as:c.369_375del, automaps to NM_000551.3:c.371_377del - most up to date transcript
ClinVarID: N/A
CAID: CA913189240 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.371_377delCACACGA
gnomAD: N/A
VariantEvidence: N/A
MutationType: minus_1_frameshift_variant
CivicName: G123fs (c.369_375delGACACAC)
MultipleGeneVariants: N/A
Genotype-phenotype correlations of 573 VHL patients from 200 kindreds were analyzed. Higher risk of pheochromocytoma was associated with missense mutations that result in substitution of a surface amino acid (p<=0.004) than for patients with missense mutations that disrupt the structural integrity of the VHL gene product (pVHL) or other loss of function mutations (either germline deletions or truncating mutations). This missense mutation (c.256C>T), affecting residue within the pVHL protein core, was found in a VHL patient with cerebellar hemangioblastomas diagnosed at 35Y. ACMG codes as follows: Supporting evidence of pathogenicity because missense variant in a gene that has a low rate of benign missense variation and where missense variants are a common mechanism of disease (PP2).
PatientID: 422
KindredID: 422
Case: Sex Unknown, 49Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CasePresentingHPOs: HP:0010797 (Hemangioblastoma)
CaseHPOFreeText: CNS hemangioblastoma.
CaseNotHPOs: HP:0009711; HP:0006770; HP:0002666; HP:0001732; HP:0000107 (Retinal capillary hemangioma, Clear cell renal cell carcinoma, Pheochromocytoma, Abnormality of the pancreas, Renal cyst)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 17024664
SupplementalData: Table S1, S2 and S3
Variant: p.L135Yfs*24 (c.404del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA432421852, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.404del
gnomAD: N/A
VariantEvidence: N/A
MutationType: deletion; minus_1_frameshift_variant
CivicName: L135fs (c.404del)
MultipleGeneVariants: N/A
Pheochromocytoma and multifocal functioning paraganglioma in a 9-year-old boy with von Hippel-Lindau disease
PMID: 12053037
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
Tyr156Cys
GroupID: 7
DiseaseAssertion: Neuroendocrine neoplasm (pheochromocytoma or paraganglioma)
GroupSize: 7
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: Ethnicity unknown
GroupAgeRange: N/A
GroupInfo: This mutation (p.Y156C (c.467A>G)) was found in 7 patients, 3 with a family history and/or a syndromic presentation and 4 with apparently sporadic presentation. 1 of the apparently sporadic patients was previously reported.
GroupPresentingHPOs: HP:0100634 (Neuroendocrine neoplasm)
GroupHPOFreeText: Patients with a pheochromocytoma or a functional paraganglioma were recruited from several different French clinical centers participating in several clinical research networks (Cortico et Medullosurrènale: les Tumeurs Endocrines, Paragan-Glioma Network, Groupe des Tumeurs Endocrines)
GroupNotHPOs: N/A
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: 1 of the apparently sporadic patients was previously reported.
SupplementalData: N/A
Variant: p.Y156C (c.467A>G)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: 43600 https://www.ncbi.nlm.nih.gov/clinvar/variation/43600/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant; transition
CivicName: Y156C (c.467A>G)
MultipleGeneVariants: N/A
HIGH GRADE VON HIPPEL-LINDAU SYNDROME PRESENTING WITH BILATERAL PHEOCHROMOCYTOMA IN A CHILD
PatientID: N/A (case)
KindredID: 1
Case: M, 9Y0M, Ethnicity Unknown
DiseaseAssertion: pheochromocytoma
FamilyInfo: The parents and siblings were negative for the gene mutation thus indicating that our patient has a De novo mutation.
CasePresentingHPOs: HP:0006748 (adrenal pheochromocytoma)
CaseHPOFreeText: previously healthy male presented with hypertension, increasing BMI despite decreased height and weight, last three years. His ultrasound was abdominal showing bilateral suprarenal masses. An abdominal MRI confirmed the finding of bilateral adrenal masses measuring 3 x 2.7 x 2.5 cm in the right and 3.6 x 3.5 x 2.7 cm in the left. He underwent a bilateral adrenalectomy and pathology resulted as bilateral pheochromocytoma
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.V166F (c.496G>T)
LegacyVariant: p.V166F
CaseProblemVariantFreeText: N/A
ClinVarID: 2224 https://www.ncbi.nlm.nih.gov/clinvar/variation/2224/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: N/A
MultipleGeneVariants: N/A
c.463G > C p.Val155Leu
216 patients with clinically expected VHL disease due to family history or presence of VHL typical tumours were routinely examined in an eye centre in Germany between January 2019 and January 2020, majority of which were of European descent (~95%). Since data on the genotype–phenotype correlation of the onset of Retinal Hemangioblastoma (RH) is scarce in relation to VHL disease, this study wanted to inversitage the relationship between VHL gene variants (truncating vs single amino acid substitutions) and the ocular phenotype of the disease. 42 different rare VHL gene variants in 148 patients were detected - some of whom had RH and some who did not. Although date of onset of RH, as well as data on central nervous system haemangioblastomas (CNSH), pheochromocytoma/paraganglioma (PPGL), clear cell renal cell carcinoma (ccRCC) and pancreatic neuroendocrine neoplasm (PNEN) were collected, it was not reported on a per patient basis and therefore could not be discussed per variant. There were 2 patients reported with the p.V155L (c.463G>C) mutation. Both members presented with retinal hemangiomas, while no other clinical manifestations were discussed. Additionally, no family information was provided.
Peripheral blood from unrelated patients with pheochromocytoma was tested for mutations of proto-oncogene RET, tumor suppressor gene VHL, succinate dehydrogenase subunit D (SDHD) gene, and the succinate dehydrogenase subunit B (SDHB) gene. Of 271 patients with nonsydromic pheochromocytoma and no family history of the disease, 30 mutations were found in VHL. Multiple pheochromocytomas were statistically more frequent among patients with mutations than among patients without mutations (21 of 66 vs. 5 of 205, P<0.001). The mutation F119L (c.357C>G) was detected in the patient, referred to in the paper by c.570C>G due to a difference in transcript sequence. This missense mutation was found in the VHL gene and one patient with pheochromocytoma.
c.500 G>Aap.R167Q
GroupID: 25B
DiseaseAssertion: Unknown. Patient was pulled from either the VHL-Registry or NET-Registry and recorded with the given mutation. Symptoms or manifestations are not clear.
GroupSize: 5
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: N/A
GroupAgeRange: N/A
GroupInfo: 5 patients with the given mutation were grouped as group 25(B) in this study. These patients were asymptomatic or unclear of symptoms.
GroupPresentingHPOs: N/A
GroupHPOFreeText: N/A
GroupNotHPOs: HP:0030405 (pancreatic endocrine tumor)
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167Q (c.500G>A)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2216 https://www.ncbi.nlm.nih.gov/clinvar/variation/2216/
CAID: N/A
gnomAD: 0.000003977 https://gnomad.broadinstitute.org/variant/3-10191507-G-A
VariantEvidence: N/A
MutationType: missense_variant; transition
CivicName: R167Q (c.500G>A)
MultipleGeneVariants: N/A
c.488 T>Aap.L163H
GroupID: 23A
Case: Sex, Age, Ethnicity unknown
DiseaseAssertion: VHL
FamilyInfo: None. The patient with the given mutation in this study was a VHL patient with pancreatic ICTs.
CasePresentingHPOs: HP:0030405 (pancreatic endocrine tumor)
CaseHPOFreeText: Patient has islet cell tumors (ICTs), or listed as pancreatic endocrine tumor.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.L163H (c.488T>A)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351756137 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.488T%3EA
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant; transversion
CivicName: L163H (c.488T>A)
MultipleGeneVariants: N/A
PatientID: 87
KindredID: 27
Case: F, Age Unknown, Chinese
DiseaseAssertion: VHL
FamilyInfo: The proband (patient 81) had 3 family members confirmed with the mutation: his aunt 2 (patient 85) had pancreatic cysts and/or tumors at age 50, his cousin/ the son of Aunt 2 was asymptomatic at the time of assessment, and the granddaughter of aunt 2 was also asymptomatic at the time of assessment. The proband also had 3 family members who passed away before diagnosis/ before confirming the mutation: his mother (patient 82) had a CNS hemangioblastoma at 33, his Aunt 1 (patient 83) had a CNS hemangioblastoma at 32, and his cousin/ the son of Aunt 1 (patient 84) had a CNS hemangioblastoma at 30.
CasePresentingHPOs: N/A
CaseHPOFreeText: The granddaughter of the proband's aunt 2 was asymptomatic at the time of assessment.
CaseNotHPOs: HP:0009711; HP:0010797; HP:0002666; HP:0005584; HP:0001737; HP:0001732 (Retinal capillary hemangioma, Hemangioblastoma, Pheochromocytoma, Renal cell carcinoma, Pancreatic cysts, Abnormality of the pancreas)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: This patient was also published in a later paper by Wang et al., 2018 (PMID: 29330336).
SupplementalData: Patient and family genotype-phenotype information is listed in Supplementary Table 1.
Variant: p.N90I (c.269A>T)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 223172; https://www.ncbi.nlm.nih.gov/clinvar/variation/223172/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: N90I (c.269A>T)
MultipleGeneVariants: N/A
PMID: 10862095
ArticleReferenceSequence: Not specified – Assumption: variants assumed to have been documented by the author under reference sequence NM_000551.3
GenotypingMethod: Direct-sequence; SSCP (detection conditions: Primers: Forward, CCGAGGAGGAGATGGAGGCC; Reverse, GCTATCGTCCCTGCTGGGTC).
SamplingMethod: N/A - not specified
Usefulness of Succinate dehydrogenase B (SDHB) immunohistochemistry in guiding mutational screening among patients with pheochromocytoma-paraganglioma syndromes Rekha Pai, Corresponding Author Rekha Pai Department of Pathology, Christian Medical College, Vellore, Tamil Nadu, IndiaRekha Pai, PhD, Molecular Pathology Laboratory, Department of Pathology, Christian Medical College, Vellore, Tamil Nadu 632004, India. e-mail: rekhapai@cmcvellore.ac.inSearch for more papers by this authorMarie Therese Manipadam, Marie Therese Manipadam Department of Pathology, Christian Medical College, Vellore, Tamil Nadu, IndiaSearch for more papers by this authorPradyumn Singh, Pradyumn Singh Department of Pathology, Christian Medical College, Vellore, Tamil Nadu, IndiaSearch for more papers by this authorAndrew Ebenazer, Andrew Ebenazer Department of Pathology, Christian Medical College, Vellore, Tamil Nadu, IndiaSearch for more papers by this authorPrasanna Samuel, Prasanna Samuel Department of Biostatistics, Christian Medical College, Vellore, Tamil Nadu, IndiaSearch for more papers by this authorSimon Rajaratnam, Simon Rajaratnam Department of Endocrinology and Metabolism, Christian Medical College, Vellore, Tamil Nadu, IndiaSearch for more papers by this author
PMID: 24735130
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
1aCerebellum446 A/GN78SMissenseLOHNegative1bCerebellum446 A/GN78SMissenseLOHNegative1cCerebellum446 A/GN78SMissenseLOHNegative
PatientID: 1 (tumour samples 1a, 1b, 1c)
KindredID: 1
Case: Sex Unknown, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CohortInfo: A total of 42 CNS haemangioblastoma samples were obtained from 31 patients, who were consecutively treated between 1993 and 1997 at the Department of Neurosurgery of the Freiburg University Medical Centre.
CasePresentingHPOs: HP:0006880 (cerebellar hemangioblastoma)
CaseHPOFreeText: Patient presented with 3 VHL-related tumors in the cerebellum (a,b,c). All three presented with LOH positive somatic information but negative methylation.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.N78S (c.233A>G)
CaseProblemVariantFreeText: N/A
LegacyVariant: p.N78S (c.446A>G)
ClinVarID: 93326 https://www.ncbi.nlm.nih.gov/clinvar/variation/93326/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: N78S (c.233A>G)
MultipleGeneVariants: N/A
PatientID: None
KindredID: 1
Case: M, 46Y0M, Spanish
DiseaseAssertion: VHL
FamilyInfo: No familial antecedents and no known familial tumors.
CohortInfo: Probands belonging to 18 unrelated Spanish VHL families carrying germline VHL deletions.
CasePresentingHPOs: HP:0000107; HP:0006880; HP:0006770; HP:0010797 (Renal cyst, Cerebellar hemangioblastoma, Clear cell renal cell carcinoma, Hemangioblastoma)
CaseHPOFreeText: Medullar hemangioblastoma.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: Exon 2-3 Deletion (c.341-?_642+?del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: Germline HSPC300 retention. Study provides evidence to show that loss of HSPC300 highly correlates with the absence of ccRCC in VHL patients.
MutationType: exon_loss_variant
CivicName: Exon 2-3 Deletion
MultipleGeneVariants: N/A
PatientID: None
KindredID: 1
Case: M, Age Unknown, Ethnicity Unknown
DiseaseAssertion: Assumed VHL
FamilyInfo: His brother and grandfather had the same VHL mutation. His mother also had this mutation and presented with pancreatic cysts, pheochromocytoma, endolymphatic sac tumor, and spinal hemangioblastoma.
CohortInfo:Three patients with endolymphatic sac tumors were studied.
CasePresentingHPOs: N/A
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: c.464-1G>A
LegacyVariant: N/A
CaseProblemVariantFreeText: The paper describes the mutation as "C-to-A transversion at position −1 on the exon 3 splice acceptor sequence in the VHL gene"
ClinVar: 43603 https://www.ncbi.nlm.nih.gov/clinvar/variation/43603/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: splice_site_variant
CivicName: Splice Site (c.464-1G>A)
MultipleGeneVariants: N/A
A study investigated paraganglioma/pheochromocytoma tumors in a retrospective cohort and a prospective cohort. Some of these tumors were found with germline VHL mutations. Tumour ID 84 was PCC and a germline c.320G>A mutation in the VHL gene. Other phenotypic and demographic information was not available.
Case 2. A 33-year-old male patient (who is the first cousin of Case 1) was referred to the retina department. He was operated on because of a CNS hemangioblastoma 3 years earlier (Figure 4). The patient stated that he had vision loss in his left eye after the CNS operation. About 2 weeks earlier, a partial right nephrectomy operation was performed due to RCC (Figure 5).Open in a separate windowFigure 4Preoperative and postoperative magnetic resonance images of the CNS haemangioblastoma (Case 2).Open in a separate windowFigure 5Abdominal computerized tomography image of Case 2. Renal cell carcinoma in the right kidney (preoperatively).Best-corrected visual acuity was 1.0 on the Snellen acuity chart in the right eye and no light perception in the left eye. Biomicroscopic examination was normal in both eyes. The fundus examination revealed optic nerve atrophy and two RH at the equator in the left eye, and was normal in the right eye. Fundus fluorescein angiography showed that hyperfluorescence and fluorescein leakage was caused by the lesions. Hyper reflectance was observed under the cross-section of the RH, and the macular section was normal in OCT (Figure 6). The same mutation as in Case 1 was also detected in the genetic analysis (c.202T>C, p.Ser
PatientID: None
KindredID: 1
Case: M, 33Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: First cousin (male, 29Y, proband) presented with renal cell carcinoma, vitritis, retinal capillary hemangioma and retinal detachment. The proband also had the germline mutation found in his cousin.
CasePresentingHPOs: HP:0005584; HP:0010797; HP:0009711; HP:0000648; HP:0000572 (Renal cell carcinoma, Hemangioblastoma, Retinal capillary hemangioma, Optic atrophy, Visual loss)
CaseHPOFreeText: He was operated on because of a CNS hemangioblastoma 3 years earlier. The patient stated that he had vision loss in his left eye after the CNS operation. About 2 weeks earlier, a partial right nephrectomy operation was performed due to RCC. The fundus examination revealed optic nerve atrophy and two RH (determined to be the cause of vision loss) at the equator in the left eye, and was normal in the right eye.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.S68P (c.202T>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA16621912, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/by_canonicalid?canonicalid=CA16621912
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: S68P (c.202T>C)
MultipleGeneVariants: N/A
3 large gene rearrangements.
PatientID: 3
KindredID: 76
Case: Sex unknown, Age unknown, French
DiseaseAssertion: VHL
FamilyInfo: N/A
CasePresentingHPOs: HP:0002666; HP:0030405; HP:0005584 (pheochromocytoma, pancreatic endocrine tumour, renal cell carcinoma)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: NONE (unspecified large rearrangement)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVar: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence:N/A
MutationType: rearrangement_region
CivicName: rearrangement
MultipleGeneVariants: N/A
Twelve (75%) of 16 gene carriers were found to have ocular hemangioblastomas(Figure 1 and Figure 2), and 7 of these had bilateral disease (Table 1). The mean number of angiomas was 3.3. However, 1 individual had 22 angiomas, most of which were in an area of previous exudative retinal detachment (see the "Comment" section) (Table 2). Exclusion of this individual resulted in a mean number of angiomas of 2.1. Six eyes had optic disc angiomas (Figure 2). Six of the 19 eyes with ocular hemangioblastomas had visual acuity less than 20/40. Two patients had no light perception in one or both eyes. The average age at diagnosis of ocular angiomatosis was 37 years.
PatientID: 11
KindredID: 1
Case: Sex Unknown, 55Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Significant family history. Pedigree follows 8 generations (see Figure 3). Family immigrated to Iowa, US, from Baden-Baden, Germany, in 1832; Likely sharing a common ancestor to the traced lineage of the Black Forest region of Germany.
CasePresentingHPOs: HP:0002666; HP:0009711 (pheochromocytoma; retinal capillary hemangioma)
CaseHPOFreeText: 45Y at first pheochromocytoma and ocular angioma (retinal capillary hemangioma).
CaseNotHPOs: HP:0010797; HP:0005584 (hemangioblastoma, renal cell carcinoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.Y98H (c.292T>C)
LegacyVariant: p.Y98H (c.505T>C)
CaseProblemVariantFreeText: N/A
ClinVar: 2223 https://www.ncbi.nlm.nih.gov/clinvar/variation/2223/
CAID: N/A
gnomAD: 0.00001343 https://gnomad.broadinstitute.org/variant/3-10183823-T-C
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: Y98H (c.292T>C)
MultipleGeneVariants: N/A
Von Hippel-Lindau Disease with Multi-Organ Involvement: A Case Report and 8-Year Clinical Course with Follow-Up
PMID: 29146893
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
Improved Detection of Germline Mutations in Korean VHL Patients by Multiple Ligation-dependent Probe Amplification Analysis
PMID: 19270817
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
14PExon 3Missensec.499C>Tp. Arg167TrpPheo, HBA CNS, PanNET
PatientID: 14
KindredID: 9
Case: Sex Unknown, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CasePresentingHPOs: HP:0002666; HP:0010797; HP:0030405 (pheochromocytoma, hemangioblastoma, pancreatic endocrine tumor)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: MEN1/ RET
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167W (c.499C>T)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2218, https://www.ncbi.nlm.nih.gov/clinvar/variation/2218/
CAID: N/A
gnomAD: 0.000007954, https://gnomad.broadinstitute.org/variant/3-10191506-C-T?dataset=gnomad_r2_1
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: R167W (c.499C>T)
MultipleGeneVariants: N/A
PatientID: 2
KindredID: 21
Case: Sex, Age, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Familial VHL. One other family member mentioned (PatientID: 1)
CasePresentingHPOs: HP:0005584 (Renal cell carcinoma)
CaseHPOFreeText: N/A
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.Q195* (c.583C>T)
CaseProblemVariantFreeText: N/A
LegacyVariant: p.Q195* (c.796C>T)
ClinVarID: 428794 https://www.ncbi.nlm.nih.gov/clinvar/variation/428794/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: stop_gained
CivicName: p.Q195* (c.583C>T)
MultipleGeneVariants: N/A
583FemaleIYesAGND* AGLOH (G)
PatientID: 5
KindredID: 5
Case: F, 83Y0M, Taiwanese (East-Asian)
DiseaseAssertion: renal cell carcinoma
FamilyInfo: N/A
CohortInfo: 8 of 19 patients presenting with clear cell renal cell carcinoma were found to be heterozygous for the germline variant rs1642742 in VHL (c.*294G>A). All but one of these patients (7/8) also presented with the germline variant rs779805 (c.-195G>A) in VHL.
CasePresentingHPOs: HP:0006770 (clear cell renal cell carcinoma)
CaseHPOFreeText: She had stage I clear cell renal cell carcinoma
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 21982469
SupplementalData: Yes - Additional file 1: Figure S1
Variant: c.*294G>A
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 342407 https://www.ncbi.nlm.nih.gov/clinvar/variation/342407/
CAID: N/A
gnomAD: 0.5911 https://gnomad.broadinstitute.org/variant/3-10191943-G-A
VariantEvidence: Heterozygous for both, she also presented with the germline variant c.-195G>A in VHL. LOH (G) of this mutation was found in the tumor tissue as well
MutationType: 3_prime_UTR_variant
CivicName: c.-195G>A AND c.*294G>A
MultipleGeneVariants: Germline, VHL, c.-195G>A
17 (22%) had frameshift variants
A cohort of VHL patients from the Greater Toronto Area in Canada were retrospectively reviewed. Patient ID 66 was found with this germline mutation (c.408delT) and no manifestations. Authors were contacted and other patients with this mutation (Patients 46, 50, 71, and 72) were reported previously in Aronoff et al, 2018 (PMID: 29437867) as family 5. Patients' age and sex were not reported. ACMG PP4
VHL
PatientID: 52
KindredID: 2
Case: Sex Unknown, 23Y0M, Norwegian
DiseaseAssertion: pheochromocytoma
FamilyInfo: Yes, a family history of neuroendocrine tumor (NET). They have another family member with the same mutation and pheochromocytoma.
CasePresentingHPOs: HP:0002666 (pheochromocytoma)
CaseHPOFreeText: Preoperatively presented with hypertension; surgery at 23Y.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: NF1, RET, SDHB, SDHC, SDHD
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.F119S (c.356T>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351753715 https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.356T%3EC
gnomAD: N/A
VariantEvidence: This mutation was found in DNA from the adjacent normal tissue, and this finding was found to be reproducible. The same VHL variant was later on observed in a family member with PHEO.
MutationType: missense_variant;transition
CivicName: F119S (c.356T>C)
MultipleGeneVariants: N/A
PatientID: 53
KindredID: 53
Case: M, 36Y0M, Korean
DiseaseAssertion: VHL
FamilyInfo: Family history positive for VHL. No further details provided.
CohortInfo: 26 Korean patients with more than one HAB in the CNS or eye, a single HAB in the CNS or retina plus a visceral manifestation (multiple renal, pancreatic or hepatic cysts, pheochromocytoma and RCC) and positive family history plus any one of the above manifestations.
CasePresentingHPOs: HP:0010797; HP:0005584 (Hemangioblastoma, Renal cell carcinoma)
CaseHPOFreeText: CNS hemangioblastoma. Other phenotypes presented but not specified (one or more of: pancreatic cyst or tumor, renal or hepatic cyst). Diagnosed with VHL Type 1.
CaseNotHPOs: HP:0002666; HP:0009711 (Pheochromocytoma, Retinal capillary hemangioma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 19270817
SupplementalData: N/A
Variant: Exon 2-3 Deletion (c.341-?_642+?del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: exon_loss_variant
CivicName: Exon 2-3 Deletion
MultipleGeneVariants: N/A
PatientID: 44
KindredID: 44
Case: M, 30Y0M, Korean
DiseaseAssertion: VHL
FamilyInfo: Family history positive for VHL. No further details provided.
CohortInfo: 26 Korean patients with more than one HAB in the CNS or eye, a single HAB in the CNS or retina plus a visceral manifestation (multiple renal, pancreatic or hepatic cysts, pheochromocytoma and RCC) and positive family history plus any one of the above manifestations.
CasePresentingHPOs: HP:0002666; HP:0010797 (Pheochromocytoma, Hemangioblastoma)
CaseHPOFreeText: Multiple or bilateral pheochromocytoma. CNS hemangioblastoma. Diagnosed with VHL Type 2A.
CaseNotHPOs: HP:0005584; HP:0009711 (Renal cell carcinoma, Retinal capillary hemangioma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 16142346; “Kim, J. W., Choi, S. J., Kim, Y. K., Ahn, S. M., Song, K. E., Jung, S. H. et al. A case report of von Hippel–Lindau disease manifested in a monozygous twin. J. Korean Soc. Endocrinol. 20, 395–400 (2005)” (Reference 15 in current publication).
SupplementalData: N/A
Variant: p.R167W (c.499C>T)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2218, https://www.ncbi.nlm.nih.gov/clinvar/variation/2218/
CAID: N/A
gnomAD: 0.000007954, https://gnomad.broadinstitute.org/variant/3-10191506-C-T
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: R167W (c.499C>T)
MultipleGeneVariants: N/A
We identified deletions ranging from 0.5 kb to 250 kb affecting part of or the entire VHL and flanking genes in 54 families.
GroupID: 33
DiseaseAssertion: VHL
GroupSize: N/A GroupNumberMales: N/A GroupNumberFemales: N/A GroupEthnicity: N/A GroupAgeRange: N/A
GroupInfo: 54 VHL deletion families from the Freiburg registry were selected in order to assist in the correlation of VHL deletions to clinical phenotypes.
GroupPresentingHPOs: HP:0005584; HP:0000107; HP:0009711; HP:0010797; HP:0009713; HP:0030424 (Renal cell carcinoma, Renal cyst, Retinal capillary hemangioma, Hemangioblastoma, Spinal hemangioblastoma, Epididymal cyst)
GroupHPOFreeText: # of affected individuals: Renal cell carcinoma (1), Renal cyst (3), Retinal capillary hemangioma (3), Hemangioblastoma/brain/cerebellum (4), Spinal hemangioblastoma (1), Epididymal cyst (1)
GroupNotHPOs: N/A
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Supplemental Table 2, Table 1, Table 3
Variant: Exon 3 Deletion (c.464-?_642+?del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: exon_loss_variant
CivicName: Exon 3 Deletion
MultipleGeneVariants: N/A
We identified deletions ranging from 0.5 kb to 250 kb affecting part of or the entire VHL and flanking genes in 54 families
GroupID: 17
DiseaseAssertion: VHL
GroupSize: N/A GroupNumberMales: N/A GroupNumberFemales: N/A GroupEthnicity: N/A GroupAgeRange: N/A
GroupInfo: 54 VHL deletion families from the Freiburg registry were selected in order to assist in the correlation of VHL deletions to clinical phenotypes.
GroupPresentingHPOs: HP:0005584; HP:0009711; HP:0009713; HP:0030393; HP:0001737 (Renal cell carcinoma, Retinal capillary hemangioma, Spinal hemangioblastoma, Endolymphatic sac tumor, Pancreatic cysts)
GroupHPOFreeText: # of affected individuals: Renal cell carcinoma (1), Retinal capillary hemangioma (1), Spinal hemangioblastoma (1), Endolymphatic sac tumor (1), Pancreatic cysts (1)
GroupNotHPOs: N/A
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Supplemental Table 2, Table 1, Table 3
Variant: Exon 2 Deletion (c.341-?-463+?del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: exon_loss_variant
CivicName: Exon 2 Deletion
MultipleGeneVariants: N/A
VHL_6Frozenc.491A>Gp.Gln164ArgF31AdrenalPCCB
PatientID: VHL_6 (tumor ID)
KindredID: 6
Case: F, 31Y0M, Ethnicity Unknown
DiseaseAssertion: Adrenal pheochromocytoma
FamilyInfo: N/A
CasePresentingHPOs: HP:0006748 (Adrenal pheochromocytoma)
CaseHPOFreeText: The patient had a benign adrenal pheochromocytoma at 31Y.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.Q164R (c.491A>G)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2238, https://www.ncbi.nlm.nih.gov/clinvar/variation/2238/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: Q164R (c.491A>G)
MultipleGeneVariants: N/A
A germline VHL mutation was detected in a 44 year old woman with a solitary cerebellar HAB
Two groups were analyzed for germline VHL mutation where Group 1 (84 individuals) presented with only one hemangioblastoma and no other clinical VHL features and those in Group 2 (4 individuals) presented with multiple hemangioblastomas and no other VHL clinical features. Peripheral blood analysis was conducted of all exons and flanking regions (90 nucleotides upstream and 45 downstream) of the VHL gene (numbered using Genbank accession number L15409). Southern blot, PCR and SSCP were performed. The c.241C>T (P81S) mutation - referred to in the paper by c.454C>T due to a difference in transcript sequence - was found in 1 patient (D24) from Group 1. She was 47 years of age and had four clinically unaffected first and second degree relatives (father (77Y0M), son (17Y0M), step-sister (43Y0M) and paternal aunt (64Y0M)) carrying this mutation. She presented with a solitary cerebellar hemangioblastoma. All other members were asymptomatic.
VHL: c.602T>C, p.Leu201Pro
A cohort of 64 pheochromocytoma and paragangliomas were screened for a BRAF mutation using direct Sanger sequencing and QRT-PCR. Genomic DNA was extracted from fresh or frozen peripheral blood. Germline mutations of VHL, SDHB, SDHD, and RET genes were also observed. The VHL mutation c.602T>C (p.L201P) was reported in patient #3, a 12Y female with bilateral pheochromocytoma. No family history was reported here.
4
PatientID: Unknown
KindredID: 4
Case: M, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: 3 members of this family were found to have the mutation and pheochromocytoma. Other declared diseases in this family are: hemangioblastoma, parathyroid nodule, and esophageal carcinoma but the presenting patient is unclear. Relationship between these family members is unclear.
CohortInfo: Patients with the diagnosis of familial or sporadic PHEO and their relatives.
CasePresentingHPOs: HP:0002666; HP:0002668 (Pheochromocytoma)
CaseHPOFreeText: Follow-up 25 years later but it is unclear if this pertained to all affected family members. VHL type 2C.
CaseNotHPOs: HP:0005584 (Renal cell carcinoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Table 1
Variant: p.P138= (c.414A>G)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 223206, https://www.ncbi.nlm.nih.gov/clinvar/variation/223206/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: P138= (c.414A>G)
MultipleGeneVariants: N/A
c.293A > G (p.Tyr98Cys)
37 Danish patients diagnosed with VHL before 18 years from a prospective cohort study from Denmark's National vHL Research Database (Binderup et al., 2013) were assessed. One family with 1 patient (Family ID11) was found with a germline missense mutation in the VHL gene (Y98C; c.293A>G). The patient was diagnosed at 0Y and had 1 retinal hemangioblastoma at 12Y and 1 CNS hemangioblastoma at 6Y. Patient 1 was 13 by the end of the study.
48EP 2.0PheoVHL({"type":"entrez-nucleotide","attrs":{"text":"NM_000551.4","term_id":"1779521775","term_text":"NM_000551.4"}}NM_000551.4):c.576delA (p.Asn193MetfsTer9)
This study investigated the effectiveness of whole exome sequencing (WES) and an in-house hybridization based gene panel (ENDOGENE Panel v2.0) at detecting mutations in pheochromocytoma/paraganglioma (PPGL) related genes. The ENDOGENE panel included EGLN1, EPAS1, FH, KIF1B, MAX, MEN1, NF1, RET, SDHA, SDHB, SDHC, SDHD, SDHAF2, TMEM127, VHL, GOT2, MDH2 and SLC25A11. WES and the ENDOGENE panel were tested on 37 samples with known variants. After optimization of the bioinformatic pipeline, 61 additional samples were tested prospectively. VHL mutations were identified in 3 patients and all were confirmed by Sanger sequencing. Patient 48 was found to have an frameshift N193Mfs*9(c.576delA) deletion and diagnosed with adrenal pheochromocytoma which was said to be hormonally active. Genetic screening was performed in his parents and the same variant was detected in her clinically healthy mother (45 years old). Her screening for VHL-associated manifestation showed no VHL-related manifestations.
14729Y29Y29NNNNNc.374A>CExon 2p.His125ProMissense
PatientID: 14
KindredID: 7
Case: Sex Unknown, 29Y0M, Brazilian (Latino/Admixed American)
DiseaseAssertion: VHL
FamilyInfo: None
CasePresentingHPOs: HP:0002668, HP:0002666; HP:0030405 (paraganglioma, pheochromocytoma, pancreatic endocrine tumor)
CaseHPOFreeText: The patient developed PPGL at 29Y of age, and a PNET at 29Y.
CaseNotHPOs: HP:0005584; HP:0001737; HP:0010797; HP:0009711; HP:0000107 (renal cell carcinoma, pancreatic cyst, hemangioblastoma, retinal capillary hemangioma, renal cyst)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.H125P (c.374A>C)
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: 223201 https://www.ncbi.nlm.nih.gov/clinvar/variation/223201/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: H125P (c.374A>C)
MultipleGeneVariants: N/A
c.371C>T
Of 31 Brazilian patients, two were found to harbour the c.371C>T (p.Thr124Ile) mutation of the VHL gene. Genomic DNA was extracted and all VHL coding regions were analyzed by Sanger sequencing. MLPA was performed to investigate large deletions using SALSA® MLPA® P016 VHL probe mix. Data analysis was performed with Genescan 3.7. These individuals were two males of the same family although their relation is not specified. Individual 26 presented with pheochromocytoma at age 13Y and pancreatic endocrine tumor at 47Y, along with renal cyst and retinal hemangioblastoma. Individual 27 presented with pheochromocytoma at 10Y with recurrence 48Y later.
PMID: 7977367
Tissue analysis from 61 VHL patients, 30 sporadic renal cell carcinoma (RCC) tumor samples, and 6 sporadic RCC cell lines revealed 22 variants within VHL patients, 10 variants in tumor samples and variants in all cell lines. All mutations cluster to the 3’ end of the VHL gene open reading frame, implicating this region as important for the tumor-suppressor function of the VHL protein. SSCP analysis found a p.R167W (c.499C>T) mutation, stated in the paper as c.712C>T due to an older transcript. It was seen in family 3, with one member affected with pheochromocytoma which was said to detect loss of heterozygosity for a PstI polymorphism within the gene. Family 3 consisted of 3 VHL-affected members: a mother and her two daughters.
p.Glu70Lys (c.208G > A)
A 74 year old man was confirmed to have the germline mutation (p.Glu70Lys (c.208G > A)). He had a history of arterial hypertension and retinitis causing loss of vision and amblyopia in the right eye. It was presumed that he might have had retinal hemangioblastoma in the past. MRI found a spinal hemangioblastoma and whole body PET scan lead to a diagnosis of renal cell carcinoma. Colonoscopy lead to the diagnosis of colorectal adenocarcinoma. Brain MRI showed cerebellar hemangioblastomas. Histologic examination of liver revealed a metastatic adenocarcinoma. The patient's mother was diagnosed with a brain tumour of unconfirmed pathology. Both his brothers (ages 70 and 79) were confirmed to have the mutation and presented with renal cell carcinoma. The patient's 44 year old son was confirmed with the mutation but was asymptomatic. His daughter was noted as having a brain hemorrhage and his niece a hematologic malignancy.
In December 2008, a 16-year-old female patient came for the first genetic consultation because of the predisposition to VHL genetic mutation.
ArticleReferenceSequence: Not specified – Assumption: variants assumed to have been documented by the author under reference sequence NM_000551.3
GenotypingMethod: N/A
SamplingMethod: N/A
large/complete deletions
PatientID: 145
KindredID: None
Case: Age and Sex unknown, Chinese
DiseaseAssertion: VHL
FamilyInfo: None
CasePresentingHPOs: HP:0001737; HP:0000107; HP:0005584; HP:0030405 (pancreatic cysts, renal cyst, Renal cell carcinoma, Pancreatic endocrine tumour)
CaseHPOFreeText: N/A
CaseNotHPOs: HP:0010797; HP:0009711; HP:0002666; HP:0030393 (hemangioblastoma, Retinal capillary haemangioblastoma, Pheochromocytoma, Endolymphatic sac tumour)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Yes; See Suppl 1 (Supporting table)
Variant: c.464-?_642+?del
CaseProblemVariantFreeText: N/A
LegacyVariant: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: exon_loss_variant
CivicName: Exon 3 Deletion
MultipleGeneVariants: N/A
Genomic DNA was extracted from the peripheral blood of 2 affected individuals and 3 unaffected individuals using the QIAamp® DNA Blood Mini kit (Germany) (Fig. 3A). Mutation detection in the VHL gene was completed by sequencing the polymerase chain reaction (PCR)
ArticleReferenceSequence: NM_000551 (version not specified, assumed to be NM_000551.3)
GenotypingMethod: polymerase chain reaction (PCR)
SamplingMethod: peripheral blood using using the QIAamp DNA Blood Mini kit (Germany)
Screening of 92 unrelated patients with VHL disease revealed 61 DNA variants. Blood samples were isolated and sequenced by direct sequencing using prism-ready reaction dye primer cycle sequencing kits (Applied Biosystem Roissy CDG France) and an ABI 373A automated sequencer (AppliedBiosystem Roissy CDG France). No variants were found in 96 control cases. This missense mutation, c.482G>A, was found in four unrelated VHL type 2A patients (patients V32, V60, V97). Patient V32's family member also had this mutation. These four patients presented with pheochromocytoma. Type 2A VHL families were described as having pheochromocytomas.
All samples demonstrating aberrant patterns in the DGGE or SSCP analysis were sequenced. PCR was performed in a final volume of 50 μl under identical conditions as the previous PCR, except that this mix contained 0.2 mM dNTPs instead of 0.02 mM dATPs and 0.8 μCi α32P-dATP. The PCR products were purified using nucleospin Extract II (Macherey-Nagel, Düren, Germany) according to manufacturers’ instructions. The purification was followed by a sequence reaction using the Bigdye Terminator V3.1 cycle sequencing kit (Applied Biosystems, Foster City, CA, USA). To 1 μl purified PCR product, 2 μl Termination Ready Reaction mix, 2 μl of 5 × sequencing buffer, 1 μl forward or reverse primer (13.2 pM), and 14 μl deionized water were added. The cycle Sequencing program was performed for 25 cycles at 96 °C for 10 s, 50 °C for 5 s and 60 °C for 4 min. This was followed by a precipitation step, adding 13 μl deionized water, 3 μl of 3 M NaAc (pH 5.2), and 64 μl ethanol (100%) to the sequence reaction product and incubating overnight at room temperature before centrifuging for 20 min at 14 000 r.p.m. After washing the samples with 70% ethanol and centrifuging them for 10 min at 14 000 g, the pellets were resuspended in 20 μl formamide (Applied Biosystems, Warrington, UK). Products were analyzed on the ABI Prism 3100 genetic analyzer (Applied Biosystems).
ArticleReferenceSequence: Not specified- Assumption: Nucleotide change is not specified in the paper, only protein coding change is. cDNA variant was inferred based on protein coding change, and reported based on VHL reference sequence NM_000551.3
GenotypingMethod: Sequenced using Bigdye Terminator V3.1 cycle sequencing kit (Applied Biosystems, Foster City, CA, USA). Products were analyzed on the ABI Prism 3100 genetic analyzer (Applied Biosystems).
SamplingMethod: tumour tissue
Frequent Mutations of VHL Gene and the Clinical Phenotypes in the Largest Chinese Cohort With Von Hippel-Lindau Disease
PMID: 31620170
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
In our study, group 5 represented the c.262T > C p.Trp88Arg mutation that included 21 patients from 2 families (Figure 4 and Table 3). Variability was observed in the mean age at onset for CHB and RCC, which were 41.1 ± 9.1 (range = 29–62) and 37.4 ± 12.9 (range = 23–65), respectively.
PatientID: 2
KindredID: 2 (group ID 5)
Case: F, 45Y0M (deceased), Chinese
DiseaseAssertion: assumed VHL
CohortInfo: Clinical characteristics of 258 patients from 80 unrelated Chinese families were reported in this study. Grouped by the 21 mutations found, 2 families with 21 members total were described, and phenotypic information was given for this group.
FamilyInfo: In family 2, 4 members were described in a 3 generation family. The patient’s father, brother, and daughter were also present with the VHL mutation. See Fig 4 for family pedigree; Table 3 for details.
CasePresentingHPOs: HP:0002894 (neoplasm of the pancreas)
CaseHPOFreeText: She had passed away with pancreatic cancer
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.W88R (c.262T>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 496053 https://www.ncbi.nlm.nih.gov/clinvar/variation/496053/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: W88R (c.262T>C)
MultipleGeneVariants: N/A
PatientID: 15
KindredID: N/A
Case: Sex Unknown, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CohortInfo: The authors evaluated 64 VHL patients (32 women and 32 men) with renal involvement of whom 54/64 had undergone renal surgery or a radiofrequency thermal ablation procedure for RCC. In 10/64 VHL patients, at least one or more RCC were diagnosed, however at the time of diagnosis an indication for treatment was not yet present. For all patients several CT/MRI scans existed for retrospective description of tumour growth kinetics.
CasePresentingHPOs: HP:0005584 (Renal cell carcinoma)
CaseHPOFreeText: This is a tumor resolution study (VHL patients were investigated based on the presence of renal tumors.) No other phenotypic information is available.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Supplementary Table S5 describes 8 patients with small deletions, including this patient.
Variant: p.L129Wfs*30 (c.384del)
LegacyVariant: c.597delT (p.128fs)
CaseProblemVariantFreeText: Submitted revision on CIViC for correct CIViC name: L129Wfs*30 (c.384del).
ClinVarID: N/A
CAID: CA70049452
gnomAD: N/A
VariantEvidence: N/A
MutationType: minus_1_frameshift_variant; deletion
CivicName: L129Wfs*?(c.383delT)
MultipleGeneVariants: N/A
The authors described the growth kinetics of 96 renal tumours in 64 VHL patients (32 males, 32 females). All patients had VHL disease with renal involvement. 54/64 had undergone renal surgery or a radiofrequency thermal ablation procedure for RCC. In 10/64 patients, at least one or more RCC was diagnosed. However, at the time of diagnosis, an indication for treatment was not yet present. For all patients, several CT/MRI scans existed for retrospective description of tumour growth kinetics. 10-ml EDTA anticoagulated blood samples were available from each patient for mutation screening of all exons of the VHL gene. Genomic DNA from blood samples was extracted using standard methods. Small deletions/insertions or point mutations were identified by DNA sequencing followed by complete mutation screening using PCR/single-strand conformation polymorphism and denaturing high-performance liquid chromatography. A germline deletion p.R177Dfs*25 (c.528del) was identified in patient #49. This mutation was noted as c.740delG in the paper due to a difference in reference transcript used (see Table S5). No family information is available for this patient.
a duplication of 11 bp in the promoter region (c.-65_-55dup11)
PatientID: 2
KindredID: 2
Case: M, 40Y0M, Ethnicity Unknown
DiseaseAssertion: assumed VHL
FamilyInfo: N/A - family history was unremarkable. The paper states however that this patient inherited the duplication from a nonsymptomatic parent. Two siblings of patient 2, aged over 40 and also carriers of the same variant, underwent a thorough clinical evaluation, which was judged as negative.
CasePresentingHPOs: HP:0006880; HP:0011798 (cerebellar hemangioblastoma, renal oncocytoma)
CaseHPOFreeText: a 40-year-old male affected by cerebellar hemangioblastoma and renal oncocytoma
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 21463266
SupplementalData: N/A
Variant: c.–65_–55dup11
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 517152 https://www.ncbi.nlm.nih.gov/clinvar/variation/517152/
CAID: N/A
gnomAD: 0.00009581 https://gnomad.broadinstitute.org/variant/3-10183466-C-CTCCGCCCCGCG
VariantEvidence: Quantitative Southern blot/real-time quantitative PCR analyses was normal in this patient. The 11 bp duplication is located within the promoter region of the VHL gene, in the vicinity of the main transcription initiation site, and within the binding site of several transcription factors. There is a possibility that the variant could alter transcription of the gene from the affected allele.
MutationType: 5_prime_UTR_variant
CivicName: c.–65_–55dup11
MultipleGeneVariants: N/A
Germline mutations were found in 20 Brazilian, VHL probands and their families. The V130F (c.388G>T) germline missense mutation was found in a VHL type 1 family of 14 affected individuals (VHL family 11). Seven patients had hemangioblastomas of the central nervous system, 2 with retinal angiomas, and one with renal carcinoma and pancreatic cystadenoma. This variant was not found in 120 alleles from normal subjects in the Brazilian population.
PatientID: None
KindredID: 231
Case: Age unknown, Sex unknown, Ethnicity unknown
DiseaseAssertion: assumed VHL
FamilyInfo: Paper states familial VHL
CasePresentingHPOs: HP:0010797; HP:0001737; HP:0005584 (hemangioblastoma; pancreatic cysts; renal cell carcinoma)
CaseHPOFreeText: Patient had CNS HB, pancreatic cysts, and a Grawitz tumor
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: Yes (Specifically Supp. Table S2)
Variant: Exon 1-3 Deletion (c.1-?_642+?del)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: exon_loss_variant
CivicName: Exon 1-3 Deletion
MultipleGeneVariants: N/A
PatientID: 5
KindredID: 6
Case: F, 40Y0M, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: N/A
CohortInfo: Thirteen patients with a supratentorial hemangioblastoma.
CasePresentingHPOs: HP:0010797 (hemangioblastoma)
CaseHPOFreeText: The patient had a hemangioblastoma localized to the corpus callosum at age 31. After surgery the patient was alive with disease. The patient was followed up 108 months later.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: Exon 3 Deletion
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType:exon_loss_variant
CivicName: Exon 3 Deletion
MultipleGeneVariants: N/A
Molecular genetic analysis of the von Hippel-Lindau disease tumor suppressor gene in familial and sporadic cerebellar hemangioblastomas
PMID: 9124215
Gene: VHL
StandardizedReferenceSequence: NM_000551.3
PatientID: Proband 3
KindredID: 1
Case: M, 17Y0M, Chinese
DiseaseAssertion: VHL
FamilyInfo: The family with PCCs includes 56 members of 4 generations, and is from Gansu Province. Among them, 7 extended over 3 generations were diagnosed as PCCs. One died before admission and another died due to a cardiovascular incident. Five were initially evaluated; evaluation included medical history, physical examination, abdominal ultrasonography, CT or MRI and laboratory tests. All 5 probands of this family underwent surgical resection. The tumors were benign under pathological examinations. There were no recurrence and malignant transformation over the period of up to 23-year follow-up. Twenty members, including 5 live patients and 15 direct relatives, accepted genetic examination.
CasePresentingHPOs: HP:0002666 (Pheochromocytoma)
CaseHPOFreeText: Bilateral PCC diagnosed at 17Y and did not have any other clinical presentations. Stated as having VHL type IIC.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.H125P (c.374A>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 223201, https://www.ncbi.nlm.nih.gov/clinvar/variation/223201/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: H125P (c.374A>C)
MultipleGeneVariants: N/A
PatientID: Proband 6
KindredID: 2
Case: F, 28Y0M, Chinese
DiseaseAssertion: VHL
FamilyInfo: Mother, aunt and aunt’s cousin (all relative to proband 6) had this variant. Mother and proband presented with unilateral pheochromocytoma and aunt and aunt’s cousin were asymptomatic. Proband also presented with a renal cyst and hypertension.
CasePresentingHPOs: HP:0002666; HP:0000107; HP:0000822 (Pheochromocytoma, Renal cyst, Hypertension)
CaseHPOFreeText: Unilateral PCC diagnosed at 28Y and unilateral renal cyst and hypertension. Stated as having VHL type IIC.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R120T (c.359G>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351753738, https://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.359G%3EC
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: R120T (c.359G>C)
MultipleGeneVariants: N/A
PatientID: 7
KindredID: 3
Case: F, 18Y0M, Indian
DiseaseAssertion: VHL
FamilyInfo: Another member of this family (Gen 1) presented with the same mutation and bilateral pheochromocytoma, pancreatic cysts, RCC and neural hemangioblastoma.
CohortInfo: This retrospective study was conducted at Department of Endocrinology of a tertiary care health centre in Western India. Patients presented to our institute between 2008 and 2016 were included in the study. During the study period a total of 33 patients were suspected to have VHL syndrome based on clinical features among whom 31 patients were found to have mutation in VHL gene. All patients are of Asian Indian descent.
CasePresentingHPOs: HP:0002666; HP:0010797; HP:0002668; HP:0030405; HP:0001737 (Pheochromocytoma, Hemangioblastoma, Paraganglioma, Pancreatic endocrine tumor, Pancreatic cysts)
CaseHPOFreeText: Bilateral pheochromocytoma and sympathetic paraganglioma. Cause of death: adrenal crisis.
CaseNotHPOs: HP:0009711; HP:0005584 (Retinal capillary hemangioma, Renal cell carcinoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167W (c.499C>T)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2218, https://www.ncbi.nlm.nih.gov/clinvar/variation/2218/
CAID: N/A
gnomAD: 0.000007954, https://gnomad.broadinstitute.org/variant/3-10191506-C-T
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: R167W (c.499C>T)
MultipleGeneVariants: N/A
GroupID: 146
DiseaseAssertion: VHL
GroupSize: N/A
GroupNumberMales: N/A
GroupNumberFemales: N/A
GroupEthnicity: N/A
GroupAgeRange: N/A
GroupInfo: VHL family found to have a germline rearrangement of the VHL gene. The number of family members included in this study is not specified.
GroupPresentingHPOs: N/A
GroupHPOFreeText: Patients within this family were found to have a clinical diagnosis of VHL disease, however, the presenting phenotypes were not specified.
GroupNotHPOs: HP:0002666 (Pheochromocytoma)
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: Stated as being previously reported in PMID 7728151 and/or 8956040. Both these reports include a family presenting with this variant and it is unclear if one or both coincide with the current family.
SupplementalData: N/A
Variant: p.W117C (c.351G>T)
LegacyVariant: c.564G>T
CaseProblemVariantFreeText: N/A
ClinVarID: 167827, https://www.ncbi.nlm.nih.gov/clinvar/variation/167827/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: W117C (c.351G>T)
MultipleGeneVariants: N/A
PatientID: V-11
KindredID: 1
Case: M, Age Unknown, Ethnicity Unknown
DiseaseAssertion: VHL
FamilyInfo: Family’s roots were traced to the German town of Leipzig in Saxony, from whence the original 11 siblings had immigrated to America around 1670. The following report is a 2011 updated pedigree on the previously reported Tisherman kindred. At the time of this study, 43/49 patients have undergone mutational analysis revealing the VHL familial mutation (Y112H) and 35/49 patients have clinical VHL manifestations. Phenotypic cumulative lifetime risk was 71% for Pheo/PGL, 15% for hemangioblastoma, 33% for retinal angioma, 3% for renal cell carcinoma, and 3% for pancreatic cysts. 6 members of the family (all deceased; 4 males, 2 females) had suspected VHL and 2 (males) of these were suspected to have had Pheo/PGL.
CasePresentingHPOs: HP:0002666; HP:0002668 (Pheochromocytoma, Paraganglioma)
CaseHPOFreeText: Phenotype noted as: Pheo/PGL (unclear which of the two or if both apply to this patient).
CaseNotHPOs: HP:0005584; HP:0009711 (Renal cell carcinoma, Retinal capillary hemangioma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 9201016; 8239848 (no genetic information; only phenotypes)
SupplementalData: N/A
Variant: p.Y112H (c.334T>C)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2222, https://www.ncbi.nlm.nih.gov/clinvar/variation/2222/
CAID: N/A
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: Y112H (c.334T>C)
MultipleGeneVariants: N/A
KindredID: 103
GroupID: 14
GroupSize: Unknown
GroupNumberMales: Unknown
GroupNumberFemales: Unknown
GroupEthnicity: Unknown
GroupAgeRange: Unknown
DiseaseAssertion: VHL
GroupInfo: Kindred no.103 describes a family where at least one member (unspecified how many) had this mutation in the VHL gene. Family history indicates that pheochromocytoma is not present in this kindred.
GroupPresentingHPOs: N/A
GroupHPOFreeText: No other phenotypic information is listed for this kindred.
GroupNotHPOs: N/A
GroupNotHPOFreeText: N/A
GroupPreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.S80R (c.240T>G)
LegacyVariant: p.S151R (c.453T>G)
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351750515
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_variant;transversion
CivicName: S80R (c.240T>G)
MultipleGeneVariants: N/A
(S80G)
A 12Y male African-American patient presented with hypertension and intermittent headaches and was found with multiple bilateral pheochromocytoma, a systolic heart murmur, left ventricular hypertrophy and heart block. He had a history of congenital microcephaly, severe hearing loss, developmental delay, and cryptorchidism. Genetic analysis confirmed a c.238A>G (p.Ser80Gly) germline mutation in the VHL gene, but this mutation was not found in the parents suggesting a de novo mutation. He had no other notable family history. There was no history of polyuria, polydipsia, tachycardia, or sweating. Exams showed normal head morphology and no neurological abnormalities, normal sinus rhythm, no evidence of coarctation of the aorta or other structural anomalies, no evidence of papilledema, hemorrhages, exudates, retinal angiomas, or focal neurological signs. He was also negative for abdominal organomegaly, abdominal bruits, renal parenchyma abnormalities, hydronephrosis and cystic lesions or tumors of the pancreas.
PatientID: 2
KindredID: 2
Case: Sex Unknown, Age Unknown, Japanese
DiseaseAssertion: VHL
FamilyInfo: N/A
CasePresentingHPOs: HP:0010797; HP:0005584 (Hemangioblastoma, Renal cell carcinoma)
CaseHPOFreeText: CNS hemangioblastoma and RCC.
CaseNotHPOs: HP:0009711; HP:0002666 (Retinal capillary hemangioma, Pheochromocytoma)
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: 10761708
SupplementalData: N/A
Variant: p.F76del (c.227_229del)
LegacyVariant: codon 147 (c.440delTCT)
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA357012, http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.226_228delTTC
gnomAD: N/A
VariantEvidence: Nucleotide deletion (i.e. 440delTCT) coincides with legacy variant nomenclature (i.e. AF010238.1) and was mapped to c.227_229del (NM_000551.3).
MutationType: inframe_deletion
CivicName: F76del (c.227_229del)
MultipleGeneVariants: N/A
c.533T>Ap.(Leu178Gln)
150 index patients with pheochromocytoma/paraganglioma were evaluated. Phenotypic data were collected and germline mutations in five susceptibility genes (RET, VHL, SDHB, SDHD and SDHC) were tested. Out of 30 patients with familial presentation, 13 were clinically diagnosed as VHL syndrome. Using PCR and Sanger sequencing through peripheral blood, genetic testing confirmed a non-familial missense mutation at c.533T>A of the VHL gene in two unrelated patients. The first was a 21 year old Asian Indian male who presented with unilateral pheochromocytoma. Family history is unknown, it was apparently sporadic. The second was a 14 year old Asian Indian male who presented with bilateral pheochromocytoma. He had a positive family history.
Case III:1 (the proband’s son)
PatientID: III:1
KindredID: 1
Case: M, 6Y0M, Chinese
DiseaseAssertion: VHL
FamilyInfo: Case III:1 (this patients mother) was a 32 year old female who complained of blurred vision for the past 2 years in her left eye. Fundus examinations showed several retinal hemangioblastomas in the temporal area of the left eye. They had previously undergone the operation for cerebellar hemangioblastoma 3 years prior. Case III:2 (this patient’s sister) was a 12 year old female who complained of a curtain coming across the vision in her left eye during the screening examination. Fundus examinations revealed a small hemangioblastoma in the infratemporal region of the peripheral retina in her right eye. A sizeable hemangioblastoma with 2.5 papilla diameters and prominant feeder vessels were detected in the inferior peripheral retina of her left eye. Case I:2 (this patient’s grandmother) had blindness in one eye and died of renal carcinoma, genetic testing was not preformed on this patient. Pedigree: see Figure 1.
CasePresentingHPOs: HP:0009711 (retinal capillary hemangioma)
CaseHPOFreeText: Fundus examination revealed a very small hemangioblastoma in the distant peripheral retina of his right eye, while his left eye was normal.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.W117R (c.349T>A)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: N/A
CAID: CA351753664 http://reg.clinicalgenome.org/redmine/projects/registry/genboree_registry/allele?hgvsOrDescriptor=NM_000551.3%3Ac.349T%3EA
gnomAD: N/A
VariantEvidence: N/A
MutationType: missense_transversion
CivicName: W117R (c.349T>A)
MultipleGeneVariants: N/A
ProbandMale
PatientID: 3
KindredID: 3
Case: M, 24Y0M, Chinese
DiseaseAssertion: VHL
FamilyInfo: (See figure 3C for pedigree). Family history of VHL. The proband (Patient 3) of family 3 was a 24-year-old male who presented with adrenal pheochromocytomas and a cyst in his left kidney. The proband's family history of VHL included a mother and aunt who died from brain hemangiomas, a sister with pheochromocytomas in her bilateral adrenals and a female cousin with pheochromocytomas in her right adrenal.
CasePresentingHPOs: HP:0006748, HP:0000107 (Adrenal pheochromocytoma, Renal cyst)
CaseHPOFreeText: Masses in his bilateral adrenals (pheochromocytomas). In February 2013, he underwent an abdominal CT scan that revealed masses in his bilateral adrenals (Fig. 1C, upper image) and a cyst in his left kidney.
CaseNotHPOs: N/A
CaseNotHPOFreeText: N/A
CasePreviousTesting: N/A
PreviouslyPublished: N/A
SupplementalData: N/A
Variant: p.R167Q (c.500G>A)
LegacyVariant: N/A
CaseProblemVariantFreeText: N/A
ClinVarID: 2216, https://www.ncbi.nlm.nih.gov/clinvar/variation/2216/
CAID: N/A
gnomAD: 0.000003977, https://gnomad.broadinstitute.org/variant/3-10191507-G-A?dataset=gnomad_r2_1
VariantEvidence: N/A
MutationType: missense_variant;transition
CivicName: R167Q (c.500G>A)
MultipleGeneVariants: N/A
41 non-related patients with retinal capillary hemangioma presenting in the Benjamin Franklin University Eye Clinic between 1988 to 1999 Germany were evaluated for the presence of other VHL lesions. VHL disease was diagnosed in 33 patients based on the presence of other severe VHL lesions (spinal hemangioblastoma, cerebellar hemangioblastoma, renal cysts, pancreatic cyst, renal carcinoma, and pheochromocytoma), molecular genetic testing, and/or family history. VHL germline mutations were identified in 27 out of 29 VHL families screened with molecular genetics. Blood samples were genetically tested using PCR-SSCP sequencing. Two patients with VHL-related retinal angiomatosis were found to have germline missense (c.548C>A) mutation in the VHL gene. This variant was reported as c.761C>A (AF010238.1) and mapped to p.S183* (c.548C>A) (NM_000551.3).